Safety behaviors, sometimes called safety-seeking behaviors, are actions people take to reduce anxiety or prevent a feared outcome in situations they expect to go badly.
People see them as preventive (Salkovskis, 1991). They believe the behavior is what stops disaster.
They’re not usually harmful on their face, but it’s how and why we use them that matters.
For instance, someone might wear headphones on public transport, not because they are anxious about speaking to others, but simply to enjoy music.
The key question is: Would you feel anxious if you couldn’t do this? If yes, it’s likely a safety behavior.
Disclaimer: This article is for informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are concerned that you may have an anxiety disorder or another mental health condition, please consult a qualified healthcare provider.

These behaviors can offer a sense of control and relief in the short term. But they are a double-edged sword.
While they might make a scenario feel more bearable, they also block opportunities to test whether feared outcomes might not happen.
Over time, this prevents us from learning that these situations might be less threatening than we think.
It might be helpful to imagine safety behaviors as emotional crutches.
Examples of Safety Behaviors in Anxiety
Here are some common safety behaviors seen across different types of anxiety:
Social Anxiety
- Avoiding eye contact to reduce perceived judgment
- Rehearsing sentences or “scripts” before speaking
- Using a phone or drink as a prop to avoid interaction
- Sitting at the edge of a group or near the door for quick escape
Panic Disorder
- Carrying water or medication “just in case”
- Staying close to exits or familiar routes
- Avoiding exercise or caffeine to prevent bodily sensations that mimic panic
- Leaning against walls or sitting to feel more stable
Phobias
- Avoiding feared objects or animals but taking precautions (e.g., crossing the street if a dog is nearby)
- Carrying a “safety object” like pepper spray or sanitizer
- Keeping excessive distance from the feared stimulus
- Only facing the phobia with someone else present
Health Anxiety and Reassurance Seeking
Reassurance seeking and checking are prominent safety behaviors in health anxiety, OCD, and generalized anxiety.
Reassurance seeking means repeatedly asking others, or searching online, for confirmation that a feared outcome will not happen. It is easy to mistake for sensible caution.
Each reassurance buys a short drop in distress, which trains the person to ask again.
A 2012 comparison of 56 patients with generalized anxiety disorder and 33 healthy participants found that patients used significantly more avoidance, safety behavior, and reassurance seeking to control worry.
Higher avoidance and safety behavior at the end of treatment also predicted worse long-term outcome (Beesdo-Baum et al., 2012).
Interviews show how this feels from the inside. In a qualitative study of 37 adults with illness anxiety disorder, one participant sometimes requested medical care “for peace of mind as well and reassurance” (Kikas et al., 2026). The same people also avoided care, fearing what might be found.
Obsessive-Compulsive Disorder (OCD)
- Repeatedly checking locks, appliances, or personal items
- Excessive handwashing or cleaning rituals
- Seeking reassurance from others to confirm safety (“Did I lock the door?”)
- Mentally repeating phrases or prayers to ward off harm
Types of Safety Behaviors
Researchers sort safety behaviors along several overlapping lines. None is a settled taxonomy, but each helps predict what a behavior does.
- Overt vs covert: Overt behaviors can be seen, such as leaving or asking for reassurance. Covert ones happen in the head, such as rehearsing or replaying a conversation.
- Preventive vs restorative: Preventive behaviors aim to stop the feared event, such as standing beside the exit. Restorative ones help you cope once distress has begun, such as sipping water.
- Avoidance vs impression management: In social anxiety, avoidance means avoiding eye contact or saying little. Impression management means rehearsing and monitoring how you come across (Gray et al., 2019).
- Subtle vs obvious: Subtle behaviors, such as gripping a pen or holding a drink to hide shaking hands, go unnoticed. They let you stay in a situation while quietly protected.
The distinctions matter because they may change what a behavior does to treatment.
A systematic review judged that restorative behaviors do not seem to interfere with exposure when they still allow full confrontation with the threat (Goetz et al., 2016). Preventive ones that hinder engagement may weaken it.
The avoidance and impression-management split also appears in adolescents. Older adolescents used impression management more than younger ones (Evans et al., 2021).
Why Do People Use Safety Behaviors?
Reduce anxiety temporarily
Safety behaviors are used because they offer short-term relief from emotional discomfort.
Engaging in them can make a stressful situation feel more manageable immediately, which is why they’re so tempting in the moment.
For example, disguising anxious feelings by rehearsing what to say can tamp down panic, for now. Relief strengthens the habit. That is negative reinforcement: removing an unpleasant state makes the action more likely next time.
Provide a sense of control or escape
People use safety behaviors to gain a sense of control or create a quick escape from perceived threats.
Whether it’s planning ahead, taking small precautions, or using a “safety signal,” the goal is to feel safer in the face of anxiety.
That sense of command is valuable in itself. For people who feel threatened by uncertainty, much checking, planning, and reassurance seeking is an attempt to remove uncertainty. The link is explored in intolerance of uncertainty.
Tied to fear of judgment, harm, or losing control
These behaviors often reflect underlying fears: of being judged, getting hurt, or losing control.
People perform safety behaviors to protect themselves from embarrassment or perceived danger, even when the situation is not actually harmful. The habit is often learned.
It starts as a sensible response to a bad experience. Someone humiliated in front of a class learns that preparing every sentence can prevent a repeat. The trouble is overgeneralization. The behavior spreads to situations where the threat is small or absent.
The Link to Avoidance
Safety behaviors are a form of partial avoidance, a middle ground between total avoidance and full exposure.
Avoidance runs along a spectrum with three points:
- Complete avoidance: not facing the feared situation at all.
- Partial avoidance: going, but with subtle “crutches” that look like engagement.
- Full exposure: facing the situation unprotected.
Only the last point lets a person test the fear.
For example, someone might go to a social event but avoid eye contact or rehearse lines in advance.
Though it may seem less extreme than outright avoidance, these behaviors still block full exposure to the feared scenario.
Using safety behaviors means never fully testing the fear. The person never learns that the feared outcome might not happen, so anxiety stays entrenched.
How Safety Behaviors Keep Anxiety Going
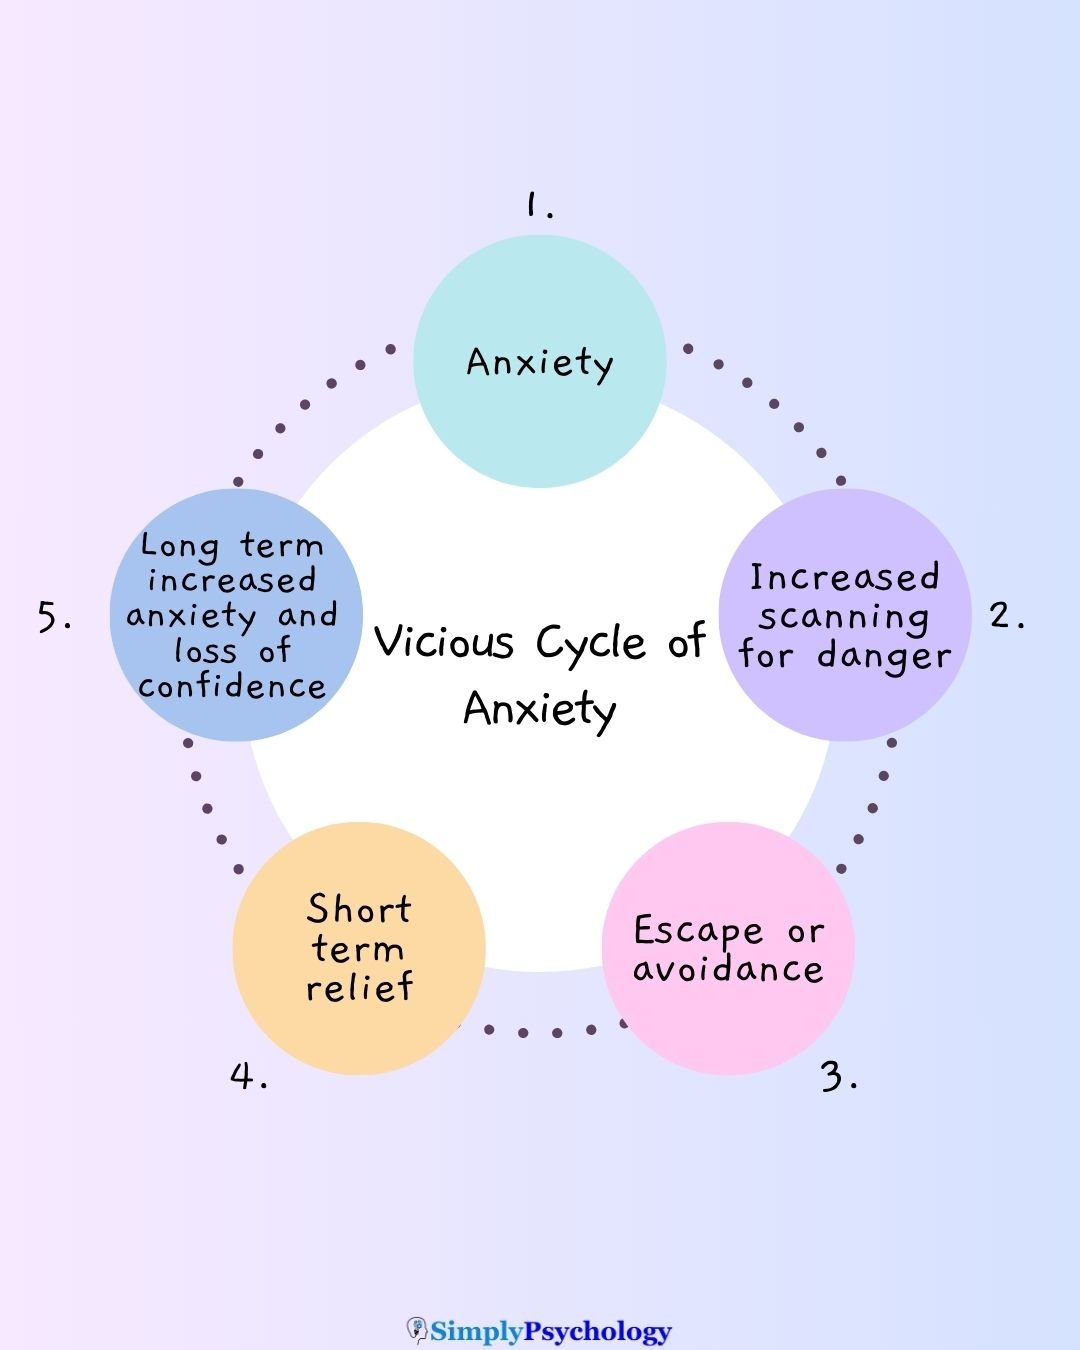
Safety behaviors play a key role in maintaining the anxiety cycle.
When someone feels anxious, a safety behavior offers quick relief. The relief is real. But it removes the chance to discover that the feared outcome may never happen.
In effect, it prevents disconfirmation, the discovery through experience that a feared outcome does not happen. The belief that the world is dangerous goes untested.
Over time, this confirms and cements the belief that the safety behaviors themselves are necessary to stay okay.
In that sense, safety behaviors keep anxiety alive instead of letting it fade naturally. Salkovskis (1991) formulated this cognitive account of how behavior maintains anxiety.
Researchers have proposed five routes. They overlap, and the evidence for each differs in strength.
- Preventing disconfirmation: After using the behavior, nothing bad happens, so the person credits the behavior, not the situation (Salkovskis, 1991).
- Blocking extinction: In laboratory conditioning, people who could make an avoidance response while their fear faded stayed afraid when it was taken away (Lovibond et al., 2009).
- Creating the feared outcome: Rehearsing can make speech stilted, and avoiding eye contact can seem cold. Experiments found safety behaviors unhelpful in several ways (McManus et al., 2008).
- Raising symptoms through use alone: Even in people without a disorder, a week of daily safety behaviors modestly raised contamination fear (Deacon & Maack, 2008) and health anxiety (Olatunji et al., 2011).
- Costs to confidence: Safety behaviors may limit how far safety learning generalizes and prevent distress tolerance from developing (Blakey & Abramowitz, 2016).
How Safety Behaviors Interfere With Exposure Therapy
Safety behaviors can undermine the effectiveness of exposure therapy, a core component of CBT for anxiety.
When used during exposure, they are thought to reduce the chance to learn that the situation may not be harmful, an essential part of therapeutic progress. But the evidence is less tidy than the theory.
A meta-analysis of 20 studies found no statistically significant benefit or harm from removing or adding safety-seeking behavior during exposure (Meulders et al., 2016). The Evidence Check below weighs this debate.
One experiment in real patients tested the idea directly.
- Aim: To test whether safety-seeking behaviors used within a situation keep anxiety going by blocking disconfirming experience.
- Method: Patients with panic disorder and agoraphobia walked into a feared situation, then spent 15 minutes in exposure either stopping or keeping their usual safety behaviors. The walk was repeated within two days.
- Results: Patients who stopped safety behaviors showed significantly greater falls in catastrophic beliefs and anxiety at retest than those who kept them.
- Conclusion: Removing safety-seeking behaviors during exposure improved belief change, as the cognitive hypothesis predicts.
This is a rare experiment in patients with a repeat behavioral test. Its limits are a two-day follow-up, unreported group sizes, and authors who had developed the theory being tested (Salkovskis et al., 1999).
Evidence Check: Do Safety Behaviors Really Maintain Anxiety?
Verdict: Supported with qualifications.
Safety behaviors do appear to contribute to keeping anxiety going. The best-quality evidence, a preregistered meta-analysis, agrees.
But the studies behind the causal claim are short and mostly in healthy student samples. Whether to remove safety behaviors during exposure is unresolved. Removal as a stand-alone intervention has a small-to-moderate effect that is probably over-estimated.
Raising Safety Behaviors Raises Symptoms, but the Evidence Is Thin
Level of evidence: Meta-analysis or systematic review; partly replicated.
The claim is simple. Using more safety behaviors increases anxiety symptoms, so they help maintain anxiety.
A 2026 meta-analysis pooled five studies that asked people to increase safety behaviors outside treatment. It found a moderate rise in symptoms (d = 0.65, 95% CI 0.46 to 0.83, seven effects) with no heterogeneity (Goodson et al., 2026).
The studies behind it are short experiments. Participants performed safety behaviors for days or a week. They include a single-group design in 56 students (Deacon & Maack, 2008) and a randomized comparison with a monitoring control in 60 participants (Olatunji et al., 2011).
Laboratory conditioning experiments agree. Safety behavior keeps threat expectancy high after extinction (Lovibond et al., 2009; van Uijen et al., 2018).
How far can this be trusted? The top rung of the evidence hierarchy is reached, but the rung is narrow. Five studies is a small base, and publication bias could not be tested formally.
All of them used young, mostly healthy volunteers told to do something unusual for a short period, so demand and expectancy remain plausible. No large, independent replication of the symptom experiments is reported. The studies come from overlapping research groups.
The most trustworthy single piece is the randomized health-anxiety experiment with a monitoring control (Olatunji et al., 2011). It still had only 60 participants and a one-week manipulation.
In short, experiments in mostly young, non-clinical samples find that deliberately increasing safety behaviors raises symptoms by a moderate amount. That supports their role as a maintaining factor.
It does not show that safety behaviors are the main cause of any disorder. It does not show that the effect lasts beyond a week or holds in patients.
Dropping Safety Behaviors Alone Helps a Little, but the Size Is Uncertain
Level of evidence: Meta-analysis or systematic review; replications conflict.
The claim is that reducing safety behaviors without other treatment lowers symptoms.
The 2026 meta-analysis found d = 0.43 (95% CI 0.27 to 0.59, k = 16) for symptoms after safety-behavior reduction. The funnel plot was asymmetric (Egger p = .012). Trim-and-fill imputed four missing studies, giving d = 0.31 (Goodson et al., 2026).
Individual trials split. A 94-participant trial found lower social anxiety at one-month follow-up than a present-focused control (Cougle et al., 2020). A 203-woman trial found lower appearance concerns than a control (Patel & Cougle, 2024).
Others disagreed. A preregistered 130-student trial found no advantage over an academic-skills control (Gorman et al., 2023).
A 201-participant trial found both arms improved comparably (Zech et al., 2025). A 106-participant health-anxiety trial found no advantage (Jakes et al., 2025).
The meta-analysis outranks any single trial. But its estimate shrinks with bias correction.
Its 16 symptom effects come from small-to-moderate samples, so each trial had limited power to detect a small effect.
Many included trials came from the Cougle lab, whose members also wrote the review. Expectancy is a further concern. Every treatment trial gave a rationale that may raise it.
The 201-participant trial found benefit only in participants who found the rationale credible (Zech et al., 2025). The most trustworthy single study is the preregistered 130-participant prevention trial (Gorman et al., 2023). Its sample was non-clinical. It says little about patients.
So stand-alone safety-behavior reduction produces small-to-moderate improvements in controlled trials, with a bias-adjusted estimate near d = 0.3. Trials with active controls often find no advantage. It is best described as promising and unproven.
Whether Safety Behaviors Spoil Exposure Is Unsettled
Level of evidence: Meta-analysis or systematic review; replications conflict.
The claim is that safety behaviors used during exposure reduce its benefit.
A meta-analysis of 20 studies found that exposure without safety-seeking behavior was not significantly better than baseline behavior (SMD 0.31, 95% CI −0.04 to 0.66).
Adding safety-seeking behavior was not significantly worse (SMD −0.13, −0.37 to 0.11) (Meulders et al., 2016). Both intervals include zero.
Experiments in specific phobia found safety gear harmless to treatment gains (Milosevic & Radomsky, 2008; Hood et al., 2010).
A contamination-fear experiment in 80 undergraduates (Rachman et al., 2011) was reproduced with 44 volunteers by an independent laboratory (van den Hout et al., 2011). Replication supports this.
The patient evidence leans the other way. A 268-patient trial in panic disorder found in-session safety behavior associated with worse outcome (Helbig-Lang et al., 2014).
Stopping safety behaviors also improved belief change in panic disorder with agoraphobia (Salkovskis et al., 1999).
The meta-analysis is the highest rung, but its authors state it could not support either conclusion.
It pooled self-reported fear at post-test. Harm may show up in other pathways, such as expectancy violation and generalization (Blakey & Abramowitz, 2016).
The single-session experiments had 43 to 80 participants, mostly non-clinical or specific-phobia samples. The 268-patient trial is large and clinical. But safety behavior was observed, not randomly assigned, so it cannot show cause.
The right reading is not that the effect is unreal. It is smaller or more conditional than the theory states.
It probably depends on which behavior is used, at which stage of treatment, and for which disorder.
The best meta-analysis found no significant harm or benefit either way.
Current thinking separates two kinds of behavior. Preventive behaviors aim to stop the feared event and probably hinder. Restorative ones help you cope once distress has begun, and may not.
Are Safety Behaviors Always Harmful?
Safety behaviors are not inherently harmful. Some serve essential, adaptive roles in everyday life.
For example, carrying an inhaler if you have asthma is a protective action grounded in real health needs, not anxiety.
The key lies in motivation and context. Adaptive behaviors address genuine risks, such as checking water temperature before getting in the bath or looking both ways before crossing the road.
In contrast, anxiety-driven safety behaviors respond to exaggerated or imagined threats and can reinforce fear over time.
Telling the two apart depends on function, not appearance.
A review of anxiety in chronic physical illness, where real dangers exist, proposes separating safety behaviors from safety precautions on that basis (Sharpe et al., 2022).
In plain terms, ask what the behavior is for, how well it fits the real risk, and whether it costs you the life you want.
A safe route home after a threat is a precaution. Rehearsing a script for casual chat because you fear judgment is a safety behavior.
Safety behaviors are also common in people without anxiety disorders. In interviews, people with low social anxiety used them and found them helpful too. The difference lay in how many they used, how often, and in how many situations (McManus et al., 2008).
Safety Behaviors, Masking, and Neurodivergent People
Anxiety is common among autistic people. Applying the safety-behavior idea to them needs care.
Spain et al. (2020) ran a qualitative study of six autistic men with social anxiety disorder.
They identified seven types of coping strategy, including avoidance, planning, impression management, and stimming. The authors saw many as safety behaviors like those in non-autistic samples. They saw camouflaging and stimming as autism-specific.
One participant described “literally, physically wearing a mask”, consciously suppressing stimming during social interaction.
Three cautions follow. They are reasoning from the evidence, not findings of the study.
- Function, not form: Reduced eye contact, sensory avoidance, or stimming can be a comfort for one person and an anxiety-driven act for another.
- Environment: Camouflaging is shaped by social settings, so a response to a hostile environment should not be treated as a personal habit to drop.
- Sample: All six participants were men and mostly white, so the findings may not apply to autistic women or other groups.
The study did not test whether reducing these behaviors helps autistic people. That question needs trials designed with autistic people.
How to Reduce Safety Behaviors
Reducing safety behaviors begins with education. The goal is not to eliminate every protective habit overnight, but to gradually challenge anxiety in manageable steps.
Experts in cognitive-behavioral therapy (CBT) emphasize that identifying and tapering safety behaviors can help build sustainable confidence, rather than reliance on temporary “coping tricks”.
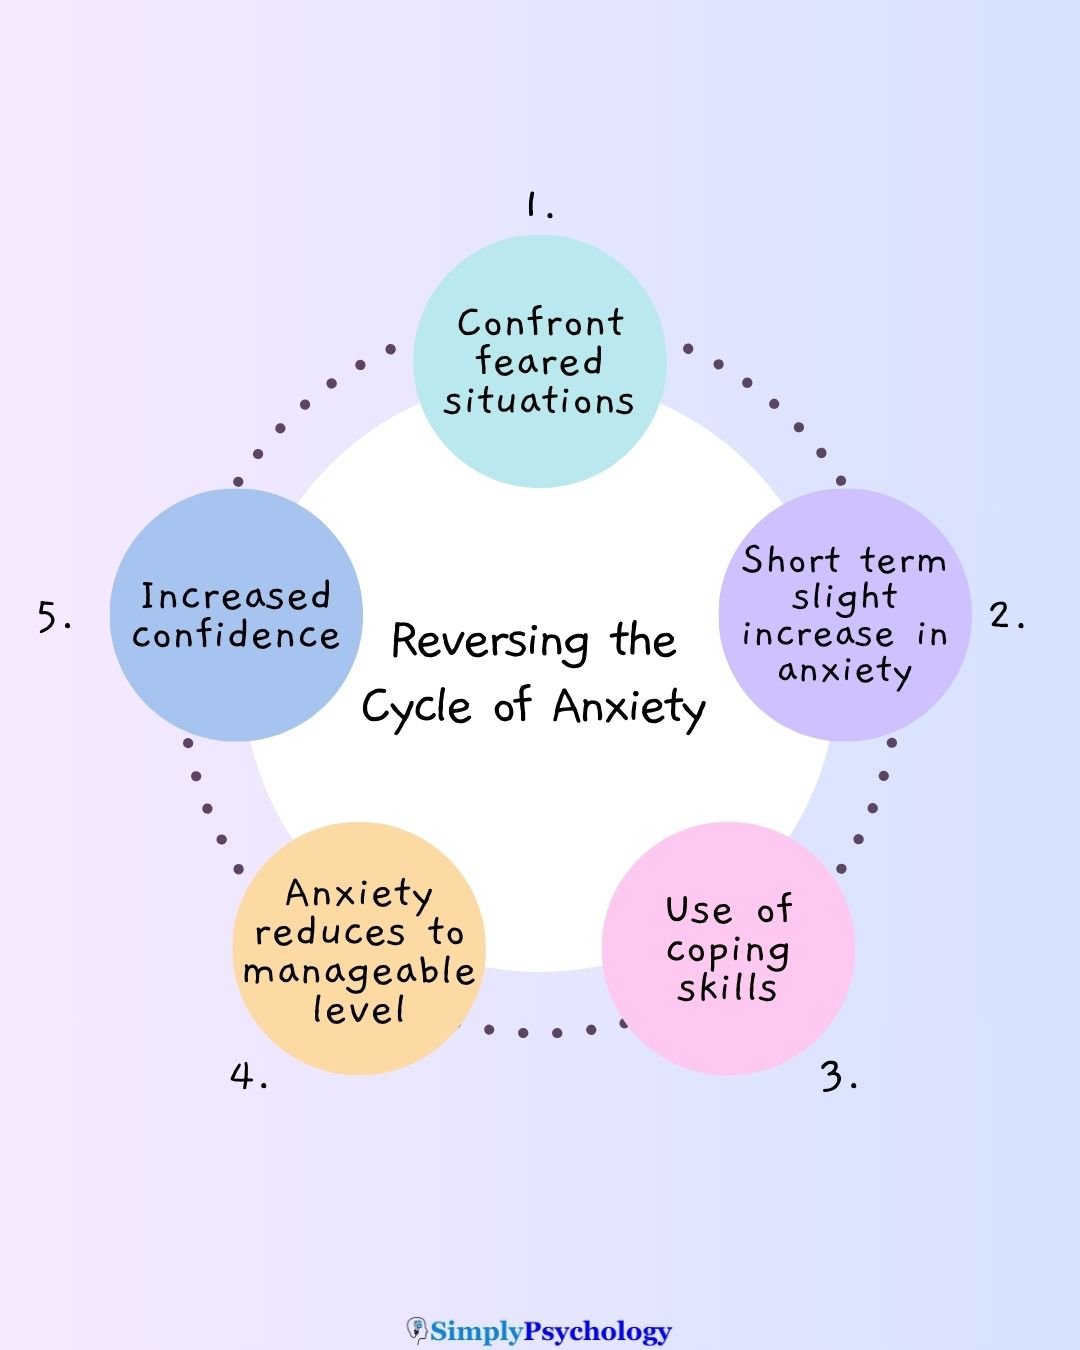
From a CBT perspective, the focus is on facing fears without crutches.
Exposure therapy plays a key role here.
By encouraging repeated, controlled contact with feared stimuli, it helps people form new associations and learn that discomfort does not equate to danger.
Therapists often set this up as a behavioral experiment. It is a planned test of a specific prediction.
For example, “If I do not rehearse, I will freeze and people will think I’m stupid.”
However, CBT practice does not usually remove safety behaviors all at once. Instead, a graded reduction phases them out step by step.
The aim is to keep anxiety manageable and preserve engagement, especially early on.
No study reviewed here compares graded with abrupt reduction. So this advice rests on clinical practice, not trial evidence.
Remember to seek advice from a healthcare professional if you need support with managing your safety behaviors.
Practical Tips for Awareness
- Identify personal safety behaviors: Notice patterns, like rehearsing lines or checking your phone. Include subtle avoidance: staying in a situation while quietly protecting yourself.
- Journaling or self-reflection: Keep a small log of moments when anxiety arises and what action you take. This builds insight into habitual safety strategies.
- Track frequency: Over time, note how often you lean on these behaviors. Seeing the patterns helps you choose a starting point for gradual reduction.
- Choose a graded order: Start with the behavior that is least reassuring to lose, then work upwards, as in an anxiety hierarchy.
These practices help readers observe and understand their own safety behaviors. They are critical steps toward mindful change.
Working With a Therapist
While this article remains educational, professionals can tailor strategies to your situation. Graded exposure and anxiety hierarchies are two examples. The aim is to keep any reduction in safety behaviors realistic and supportive.
Professional help matters most in some cases. These include severe anxiety, behaviors that are also real precautions, and situations where the usual rules may not fit.
Collaborating with a therapist can make the process more structured, safe, and personally relevant.
Remember: this article isn’t a therapy guide, but a complement—encouraging readers to seek professional support for personalized care.
Does Reducing Safety Behaviors on Its Own Work?
Researchers now test dropping safety behaviors as a stand-alone intervention, often with daily text-message reminders over a month. The 2026 meta-analysis by Goodson et al. is the best summary so far.
- Aim: To test whether stand-alone manipulations that increase or decrease safety behaviors change how often they are used and clinical symptoms.
- Method: The authors searched three databases and included 26 studies with 2,048 participants (mean age 24.9). Nineteen were randomized controlled trials, and the review protocol was registered.
- Results: Reduction beat control on symptoms (d = 0.43, k = 16), but bias correction lowered this to d = 0.31. Increasing safety behaviors raised symptoms (d = 0.65).
- Conclusion: The results support a role for safety behaviors in anxiety. Stand-alone reduction may lower symptoms, but the authors urge caution because few studies exist.
This is the highest-quality evidence on the question. Its protocol was registered, and two reviewers screened studies independently. But several of its authors also wrote included trials, so it is not an independent appraisal. The samples were mostly young, white, and from the United States (Goodson et al., 2026).
The Evidence Check above weighs how far these trials can be trusted.
Key Takeaways
- Definition: Safety behaviors are actions, visible or mental, used to prevent a feared outcome or manage anxiety in the moment.
- Why Used: They bring quick relief and a sense of control, so the habit is reinforced.
- Maintenance: They block disconfirmation. When nothing bad happens, the person credits the behavior, not the situation.
- Exposure: Whether they spoil exposure therapy is contested, and some safety aids appear harmless.
- Not Always Harmful: Proportionate precautions against real danger, such as an inhaler for asthma, are not the problem.
- Reduction: Graded reduction, ideally with a clinician, is the usual approach when anxiety is severe.
- Verdict: Supported with qualifications — the best meta-analysis agrees that safety behaviors help maintain anxiety, but the studies are short and mostly in healthy students.
References and Further Reading
Centre for Clinical Interventions (CCI) What are safety behaviours?
Centre for Clinical Interventions (CCI) Stepping out of Social Anxiety
Beesdo-Baum, K., Jenjahn, E., Höfler, M., Lueken, U., Becker, E. S., & Hoyer, J. (2012). Avoidance, safety behavior, and reassurance seeking in generalized anxiety disorder. Depression and Anxiety, 29(11), 948–957. https://doi.org/10.1002/da.21955
Blakey, S. M., & Abramowitz, J. S. (2016). The effects of safety behaviors during exposure therapy for anxiety: Critical analysis from an inhibitory learning perspective. Clinical Psychology Review, 49, 1–15. https://doi.org/10.1016/j.cpr.2016.07.002
Deacon, B., & Maack, D. J. (2008). The effects of safety behaviors on the fear of contamination: An experimental investigation. Behaviour Research and Therapy, 46(4), 537–547. https://doi.org/10.1016/j.brat.2008.01.010
Evans, R., Chiu, K., Clark, D. M., Waite, P., & Leigh, E. (2021). Safety behaviours in social anxiety: An examination across adolescence. Behaviour research and therapy, 144, 103931. https://doi.org/10.1016/j.brat.2021.103931
Goetz, A. R., Davine, T. P., Siwiec, S. G., & Lee, H. J. (2016). The functional value of preventive and restorative safety behaviors: A systematic review of the literature. Clinical Psychology Review, 44, 112–124. https://doi.org/10.1016/j.cpr.2015.12.005
Goodson, J. T., Patel, T. A., Zech, J. M., Sala, M. C., & Cougle, J. R. (2026). The standalone effect of safety behavior manipulations: A systematic review and meta-analysis. Clinical Psychology Review, 124, 102703. https://doi.org/10.1016/j.cpr.2026.102703
Gorman, E. L., Goodson, J. T., & Haeffel, G. J. (2023). Reducing safety behaviors to prevent anxious symptoms: A pre-registered prevention intervention study. Cognitive Behaviour Therapy, 52(6), 641–653. https://doi.org/10.1080/16506073.2023.2237671
Gray, E., Beierl, E. T., & Clark, D. M. (2019). Sub-types of safety behaviours and their effects on social anxiety disorder. PLOS ONE, 14(10), e0223165. https://doi.org/10.1371/journal.pone.0223165
Helbig-Lang, S., Richter, J., Lang, T., Gerlach, A. L., Fehm, L., Alpers, G. W., Ströhle, A., Kircher, T., Deckert, J., Wittchen, H.-U., & Gloster, A. T. (2014). The role of safety behaviors in exposure-based treatment for panic disorder and agoraphobia: Associations to symptom severity, treatment course, and outcome. Journal of Anxiety Disorders, 28(8), 836–844. https://doi.org/10.1016/j.janxdis.2014.09.010
Hood, H. K., Antony, M. M., Koerner, N., & Monson, C. M. (2010). Effects of safety behaviors on fear reduction during exposure. Behaviour Research and Therapy, 48(12), 1161–1169. https://doi.org/10.1016/j.brat.2010.08.006
Jakes, K. S., Jessup, S. C., Rosenfield, D., & Olatunji, B. O. (2025). Effects of text message reminders of safety behavior reduction on health anxiety: A randomized control trial. Behaviour Research and Therapy, 192, 104790. https://doi.org/10.1016/j.brat.2025.104790
Kikas, K., Werner-Seidler, A., Corkish, B., Upton, E., Holden, M., & Newby, J. M. (2026). Illness anxiety disorder: A qualitative study of people with health anxiety and their experiences seeking and avoiding medical care. British Journal of Clinical Psychology, 65, 68–85. https://doi.org/10.1111/bjc.70005
Lovibond, P. F., Mitchell, C. J., Minard, E., Brady, A., & Menzies, R. G. (2009). Safety behaviours preserve threat beliefs: Protection from extinction of human fear conditioning by an avoidance response. Behaviour Research and Therapy, 47(8), 716–720. https://doi.org/10.1016/j.brat.2009.04.013
McManus, F., Sacadura, C., & Clark, D. M. (2008). Why social anxiety persists: An experimental investigation of the role of safety behaviours as a maintaining factor. Journal of Behavior Therapy and Experimental Psychiatry, 39(2), 147–161. https://doi.org/10.1016/j.jbtep.2006.12.002
Meulders, A., Van Daele, T., Volders, S., & Vlaeyen, J. W. S. (2016). The use of safety-seeking behavior in exposure-based treatments for fear and anxiety: Benefit or burden? A meta-analytic review. Clinical Psychology Review, 45, 144–156. https://doi.org/10.1016/j.cpr.2016.02.002
Milosevic, I., & Radomsky, A. S. (2008). Safety behaviour does not necessarily interfere with exposure therapy. Behaviour Research and Therapy, 46(10), 1111–1118. https://doi.org/10.1016/j.brat.2008.05.011
Olatunji, B. O., Etzel, E. N., Tomarken, A. J., Ciesielski, B. G., & Deacon, B. (2011). The effects of safety behaviors on health anxiety: An experimental investigation. Behaviour Research and Therapy, 49(11), 719–728. https://doi.org/10.1016/j.brat.2011.07.008
Patel, T. A., & Cougle, J. R. (2024). Safety behavior reduction for appearance concerns: A randomized controlled trial of a smartphone-based intervention. Journal of Consulting and Clinical Psychology, 92(12), 788–799. https://doi.org/10.1037/ccp0000920
Rachman, S., Shafran, R., Radomsky, A. S., & Zysk, E. (2011). Reducing contamination by exposure plus safety behaviour. Journal of Behavior Therapy and Experimental Psychiatry, 42(3), 397–404. https://doi.org/10.1016/j.jbtep.2011.02.010
Salkovskis, P. M. (1991). The importance of behaviour in the maintenance of anxiety and panic: A cognitive account. Behavioural Psychotherapy, 19(1), 6–19. https://doi.org/10.1017/S0141347300011472
Salkovskis, P. M., Clark, D. M., Hackmann, A., Wells, A., & Gelder, M. G. (1999). An experimental investigation of the role of safety-seeking behaviours in the maintenance of panic disorder with agoraphobia. Behaviour Research and Therapy, 37(6), 559–574. https://doi.org/10.1016/S0005-7967(98)00153-3
Sharpe, L., Todd, J., Scott, A., Gatzounis, R., Menzies, R. E., & Meulders, A. (2022). Safety behaviours or safety precautions? The role of subtle avoidance in anxiety disorders in the context of chronic physical illness. Clinical psychology review, 92, 102126. https://doi.org/10.1016/j.cpr.2022.102126
Spain, D., Zıvralı Yarar, E., & Happé, F. (2020). Social anxiety in adults with autism: A qualitative study. International Journal of Qualitative Studies on Health and Well-being, 15(1), 1803669. https://doi.org/10.1080/17482631.2020.1803669
van den Hout, M. A., Engelhard, I. M., Toffolo, M. B. J., & van Uijen, S. L. (2011). Exposure plus response prevention versus exposure plus safety behaviours in reducing feelings of contamination, fear, danger and disgust: An extended replication of Rachman, Shafran, Radomsky & Zysk (2011). Journal of Behavior Therapy and Experimental Psychiatry, 42(3), 364–370. https://doi.org/10.1016/j.jbtep.2011.02.009
van Uijen, S. L., Leer, A., & Engelhard, I. M. (2018). Safety behavior after extinction triggers a return of threat expectancy. Behavior Therapy, 49(3), 450–458. https://doi.org/10.1016/j.beth.2017.08.005
Zech, J. M., Patel, T. A., & Cougle, J. R. (2025). Safety behavior fading for social anxiety: A randomized controlled trial of a self-monitoring intervention. Journal of Anxiety Disorders, 115, 103068. https://doi.org/10.1016/j.janxdis.2025.103068

