The ADHD hyperactive-impulsive type is marked by restless, fidgety behavior and impulsive thoughts, decisions and actions.
The absence of significant inattentive symptoms distinguishes it from the inattentive type of ADHD and the combined types of ADHD.
This type is thought to be the rarest subtype in adults. Only 23 of 691 adults (3%) in one large clinical sample received that diagnosis (Gibbins et al., 2010).
It is more common in young children, though. It is often diagnosed early because the signs are so visible.
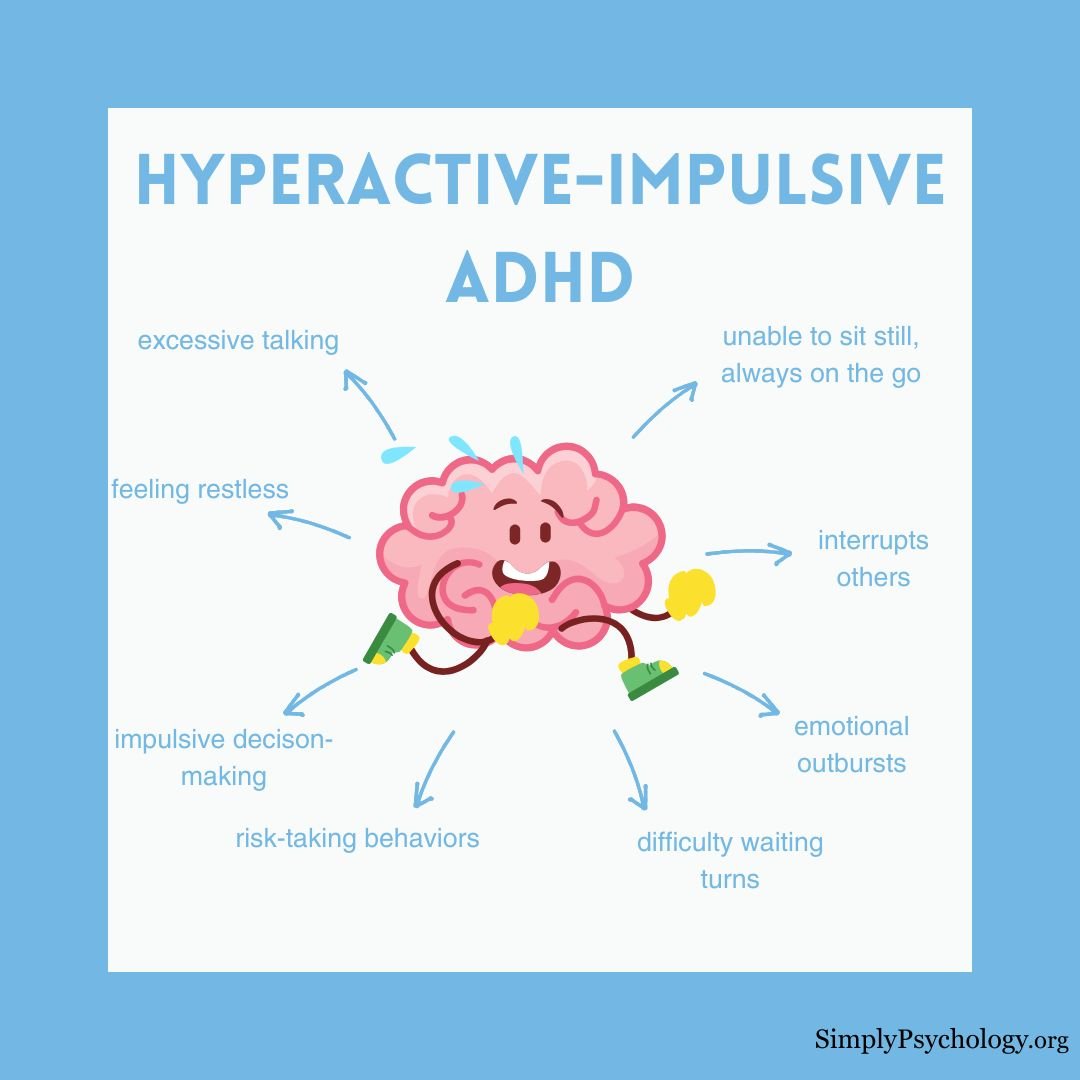
Signs of ADHD Hyperactive-Impulsive Type
Below are some of the signs associated with the hyperactive-impulsive type of ADHD:
Hyperactivity:
- Constantly fidgeting or being unable to sit still
- Children may run about or climb at ‘inappropriate’ times
- Always ‘on the go’ and full of energy
- Talking a lot and jumping around topics
- Difficulty engaging in quiet activities
- Racing/hyperactive thoughts
Impulsivity:
- Making decisions without thinking through the consequences
- Interrupting others or answering before hearing the full question
- Intruding on others’ activities without intending to be rude
- Difficulty waiting turns or waiting in lines
- Risky behaviors without consideration
- Emotional outbursts in conversation
The combined subtype shares these signs. It includes both inattentive and hyperactive/impulsive symptoms.
The DSM-5-TR calls these presentations, not subtypes. Everyone is assessed against the same 18 symptoms, and the label records only which cluster dominates (American Psychiatric Association, 2022). By adolescence, a hyperactive child may look mainly inattentive.
Studies have shown that the frequency of hyperactive-impulsive signs tends to diminish with age in individuals with ADHD.
Those diagnosed with hyperactive-impulsive ADHD in childhood are likely to be later diagnosed with the combined subtype as demands for attention increase with age.
It could be that hyperactivity and impulsivity are managed better or are better masked (or camouflaged) in adulthood.
What fades is the visible part. Franke et al. (2018) describe hyperactivity receding through adolescence. Inattention (trouble sustaining focus), inner restlessness and emotional dysregulation (feelings that arrive fast and settle slowly) often persist.
Prevalence tracks that shift: around 5% of children meet criteria for ADHD, against roughly 2.5% of adults (Polanczyk et al., 2007; Demontis et al., 2019). What predicts persistence rather than remission is still poorly understood.
How does this compare with the inattentive type?
The two types look different from the outside. Hyperactive-impulsive ADHD shows up as restlessness, interrupting, and difficulty waiting turns.
This contrasts with the inattentive type of ADHD, which is characterized by persistent inattention, difficulty sustaining focus, and forgetfulness.
One influential account (Barkley, 1997) puts impaired response inhibition, the ability to stop an action once it has started, at the centre of ADHD. That gap can create social friction. Impulsive interruptions and blurted comments are easy to read as rudeness, even when no offence is meant.
A rival account (Sonuga-Barke, 2003) adds a second route called delay aversion. Here, waiting itself feels aversive, so behaviour is organised to cut the wait short. Neither model has been superseded. Researchers now treat them as describing partly separate groups within ADHD.
While the inattentive type is often underdiagnosed, especially in girls, the hyperactive/impulsive type is easier to spot and more often prompts early referral.
Treatment for the inattentive type focuses on improving organization and attention to detail, while hyperactive/impulsive interventions target impulse control and self-regulation.
Symptoms overlap between the two subtypes. Only a qualified professional can tell them apart.

Click here for a full breakdown of the general signs of ADHD.
What Causes Hyperactive-Impulsive ADHD?
There is no single cause.
Hyperactive-impulsive ADHD arises from many inherited genetic differences, each of small effect. These work alongside early-life factors that shape how attention and self-regulation develop.
Genetics and heritability
ADHD is one of the most heritable conditions in psychiatry.
Reviewing decades of family, twin and adoption research, Faraone and Larsson (2019) put its heritability at around 74%. Heritability is the share of variation between people that genetic differences explain. That places it alongside height.
No single “ADHD gene” exists. Instead, many common variants each add a little liability. That is what polygenic means: many genes acting together, none decisive on its own.
The largest genome-wide study to date (Demontis et al., 2023) compared 38,691 people with ADHD against 186,843 controls. It identified 27 risk loci and 76 candidate genes, concentrated in early brain development and in midbrain dopamine neurons.
High heritability does not mean genes are destiny. It describes a whole population, not any one person, and leaves room for environment to shape how ADHD unfolds.
Twin-based figures carry a caveat too. They assume identical and fraternal twins are treated equally alike. If identical twins are treated more alike, the estimate runs high.
Genetic work also suggests that a diagnosis marks the extreme end of a continuum of heritable traits (Demontis et al., 2019). Where the line falls is partly a pragmatic choice.
Brain circuits and dopamine
Inherited liability shows up in how certain brain networks develop. The fronto-striatal circuits, the loops linking the frontal cortex to deeper structures, support attention, motivation and the ability to hold back an action.
Dopamine matters here too. Volkow et al. (2009) scanned 53 non-medicated adults with ADHD and 44 controls using PET imaging. They found lower availability of dopamine markers in the brain’s reward pathway.
That pattern fits the everyday experience of ADHD: effort is hard to sustain for a distant reward, while something immediately interesting grips completely.
Dopamine is not simply low. An earlier scan study (Dougherty et al., 1999) found 70% higher dopamine transporter density in the striatum, a deep brain region, in adults with ADHD.
Transporters clear dopamine back out of the synapse, and scan measures shift with imaging method, brain region and prior medication. The picture is one of atypical regulation, not one dial turned down.
Dopamine and noradrenaline both modulate these circuits. They are also what stimulant medication acts on.
These findings are correlational, though. They compare groups at one moment and cannot show what causes what.
Early-life risk factors
Environment shapes whether inherited liability is expressed.
The best-supported early risks are:
- Birth: premature birth and low birth weight.
- Prenatal exposure: smoking, alcohol or severe stress.
- Early exposure: lead or pesticides.
- Injury: acquired brain injury is a further route.
Some familiar suspects are not causes at all. Sugar, screen time, family stress and parenting style do not cause ADHD.
A chaotic or high-conflict home can still make traits harder to live with. That is a reason to support families. It is not a reason to blame them.
Psychologists call this shape diathesis-stress. An inherited vulnerability meets environmental pressure. Genes load the dice; circumstances influence how the roll plays out.
Because hyperactive-impulsive traits are the most visible, this presentation is often noticed early in childhood. That visibility is about how the traits look to other people, not about how severe they are.
Impact of ADHD hyperactive-impulsive type
Below are some of the potential impacts of having hyperactive-impulsive ADHD:
Social difficulties
Frequent interruptions and impulsive comments can cause misunderstandings and may seem disrespectful.
‘Eric’ who has ADHD describes how he is not able to control his impulses and is not aware of them:
“It’s a person shouting behind thick glass in the back of my head.”
He explains how he may impulsively respond to someone and then regret it later on:
“Reflection comes later and it’s very painful.”
Many people with hyperactive-impulsive ADHD find friendships hard to make, which can lead to loneliness.
Work and school challenges
During school, a child with hyperactive-impulsive ADHD may find it difficult to sit still and focus in class.
They may struggle to stay seated. Restlessness can look like disruption, which often means trouble with the teacher.
Adults may find it difficult to concentrate at work during meetings or with completing tasks.
Projects may start with enthusiasm, but impulsivity makes following through and finishing them a struggle.
Emotional challenges
People with ADHD can notice their emotional reactions yet struggle to control them in the moment, because the responses are impulsive.
“I can feel it come over me, I am then in my head telling myself to stop yet unable to. It is like the controls of my body have been hijacked by someone else… I know it’s going to hurt, there is going to be catastrophic damage but all I can do is sit by and pray I survive.”
‘Margot’
This reduced ability to self-regulate strong emotions can lead to breakdowns in relationships and could diminish self-worth:
“I feel like a monster… I’m so tired of being this helpless mess.” (‘Cleo’)
Financial difficulties
Impulsivity can transfer to impulsive spending, as ‘Nik’ explains:
“It’s like I don’t have that thought process of no you can’t afford this you have more important thing to pay for! It’s so impulsive by the time I’m home from being out I’m filled with regret and dread!”
Difficulty controlling impulses can lead to financial stress and shame. Many people end up in debt, with piles of unused purchases and ongoing anxiety about money.
“I decided I wanted to try yoga whilst I was out shopping then went on to buy a yoga outfit a yoga matt and a matching water bottle! I’ve not even tried yoga yet so why of earth have I done this?!”
‘Maria’
Note that because the hyperactive-impulsive type of ADHD is less common in adults, these personal experiences describe hyperactivity and impulsivity in ADHD in general.
How Hyperactive-Impulsive ADHD Is Diagnosed
There is no blood test or brain scan for ADHD. Diagnosis is a clinical judgement made by a qualified professional against explicit written criteria.
The DSM-5-TR criteria
The DSM-5-TR (American Psychiatric Association, 2022) lists 18 symptoms, split into two groups of nine. One group covers inattention, the other hyperactivity and impulsivity.
A predominantly hyperactive-impulsive diagnosis needs enough symptoms from the second group alone. Children up to age 16 must show at least six; from age 17 the threshold drops to five, because visible restlessness usually fades with age.
Four further conditions apply:
- Early onset: several symptoms were present before age 12.
- Pervasiveness: they show up in two or more settings, such as home and school.
- Impairment: they genuinely interfere with daily life or development.
- Differential diagnosis: the pattern is not better explained by another condition.
The DSM-5-TR also rates severity: mild, moderate or severe. Since DSM-5, it explicitly allows an autism diagnosis alongside ADHD, which the previous edition prohibited.
The ICD-11 (code 6A05) describes the same three presentations and sits closely alongside the DSM. It replaced ICD-10’s narrower “hyperkinetic disorders”, which required both severe inattention and hyperactivity and so captured a smaller group.
What an assessment involves
Assessment gathers several strands of evidence:
- Rating scales: Standardised checklists map a person’s traits onto the diagnostic criteria. The individual completes them, and so do people who know them well.
- Developmental history: This establishes when the traits began and how they play out at home, at school and at work.
- Adult assessment: For adults, that history must be reconstructed after the fact. Childhood onset is required, so the assessment reaches back decades.
- Medical review: This rules out look-alikes such as thyroid problems, sleep disorders and sensory difficulties.
- Co-occurring conditions: Anxiety, depression, autism, tic disorders and learning difficulties are common alongside ADHD. Each can mask ADHD, or be masked by it.
- Symptom validity: Diagnosis rests largely on self-report and can unlock medication and accommodations, so clinicians confirm the account is credible. That is not an accusation.
How common is ADHD?
Pooling 102 studies of 171,756 young people worldwide, Polanczyk et al. (2007) found that about 5% of under-18s meet criteria for ADHD. Around 2.5% of adults do (Demontis et al., 2019).
Published estimates had varied wildly before that. The review used metaregression, a technique that tests which features of the studies themselves explain why their results differ.
Method, not geography, drove the variation. What mattered was the diagnostic criteria used, who reported the symptoms, and whether impairment was required for a diagnosis.
That finding undercut the old claim that ADHD is an American invention.
Boys are diagnosed roughly three times as often as girls. But the true gap is probably narrower. A UK expert consensus (Young et al., 2020) puts much of it down to referral bias and masking.
Girls more often show quieter, inattentive presentations, which are referred to services less readily. They also develop strategies that hide their difficulties, and are often treated for anxiety or depression first.
Adults are widely under-recognised as well (Kooij et al., 2019). That is why late diagnosis has become so common.
Managing hyperactive-impulsive ADHD
Mindfulness techniques
Mindfulness means paying attention to the present moment without judgment. Building that awareness creates a pause between an impulse and acting on it.
That sounds like an odd fit for a restless brain. But adapted for ADHD, short and frequent practice can help center focus and manage impulsivity.
It works best alongside other structures. Consistent routines, protected sleep and regular exercise all help, and exercise acutely improves focus.
Foster self-compassion
ADHD coach Dr. Doug emphasizes the importance of self-compassion. This involves treating oneself with kindness and understanding and recognizing ADHD as a neurological difference rather than a personal failing.
Cultivating self-compassion can help you overcome the self-criticism and shame often associated with ADHD, promoting a more positive and accepting self-image.
Seek professional guidance
Therapists, coaches and psychiatrists can offer strategies tailored to your own pattern of hyperactivity and impulsivity.
The talking therapies target different things. Cognitive behavioral therapy works on the disorganization, procrastination and low self-esteem that build up after years of difficulty. It also treats any anxiety or depression alongside them.
For children, the best-evidenced psychological route is behavioral therapy. Parent training and classroom behavior management teach structured routines and consistent responses, and are first-line for pre-schoolers.
Channel energy and focus
Find activities that give hyperactive energy somewhere useful and enjoyable to go.
Michael Phelps found that outlet in swimming. Dr. Edward (Ned) Hallowell, a well-known ADHD expert, channels his into an energetic lecturing style and has managed his ADHD without medication.
Research backs the wider idea. As Jane Ann Sedgwick and colleagues at King’s College London found, successful adults with ADHD describe real strengths. Their interviews picked out:
- Cognitive dynamism
- Energy and courage
- Resilience and self-acceptance
- Divergent thinking and adventurousness
- Hyper-focus: intense absorption in a task that genuinely grips you
Participants described working with these attributes, not only against their difficulties.
This is a way to manage impulsivity while still embracing the energy that comes with hyperactive-impulsive ADHD.
Seek accommodations
In workplaces or educational settings, accommodations such as extended deadlines or quiet workspaces can make a significant difference.
Much of the day-to-day difficulty lies in organisation, time and self-regulation. Structure helps. External memory aids such as lists, calendars and reminders take pressure off recall. Breaking large tasks into small steps with regular breaks is another common strategy.
Availability and acceptance vary widely. You may have to advocate for your needs and seek supportive environments.
Increasingly, the question is what environment lets this brain work well, not only what is going wrong.
Hobbies as a form of fidgeting
Try engaging in detail-oriented hobbies like knitting, crochet, or drawing to manage the restlessness associated with hyperactivity.
These hobbies offer a socially acceptable way to fidget, providing an outlet for excess energy while also producing tangible results.
Use medication when appropriate
Dr. Thomas Brown, a clinical psychologist, stresses finding the right medication and dosage for each person, because stimulant responses vary significantly.
The evidence backs that caution. Cortese et al. (2018) pooled 133 double-blind trials covering more than 18,000 children, adolescents and adults, and ranked every oral ADHD medication at once.
Tolerability matters here. It means how well people can stay on a drug despite its side effects.
Weighing that against benefit, methylphenidate came out as the preferred first choice for children and adolescents, and amphetamines for adults. The strong evidence covers only about the first 12 weeks.
Long-term benefit is far less well studied. So working closely with a qualified medical professional matters: to decide whether medication suits you, to monitor side effects, and to adjust dosage over time.
Key Takeaways
- Core Traits: Restlessness, fidgeting, interrupting and acting before thinking. Inattention is not a prominent feature.
- How Common: In adults it is the least commonly diagnosed presentation, but it is often spotted early in childhood because the traits are so visible.
- Course: Visible hyperactivity usually fades with age. Inner restlessness and emotional dysregulation often persist (Franke et al., 2018).
- Causes: Heritability is around 74% (Faraone & Larsson, 2019). It acts through fronto-striatal brain circuits and dopamine signalling.
- Diagnosis: There is no single test. A professional checks the DSM-5-TR criteria across two or more settings.
- Support: Medication, therapy, accommodations and self-management all help. Methylphenidate is first-line for children (Cortese et al., 2018).
References
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). https://doi.org/10.1176/appi.books.9780890425787
Barkley, R. A. (1997). Behavioral inhibition, sustained attention, and executive functions: Constructing a unifying theory of ADHD. Psychological Bulletin, 121(1), 65–94. https://doi.org/10.1037/0033-2909.121.1.65
Cortese, S., Adamo, N., Del Giovane, C., Mohr-Jensen, C., Hayes, A. J., Carucci, S., Atkinson, L. Z., Tessari, L., Banaschewski, T., Coghill, D., Hollis, C., Simonoff, E., Zuddas, A., Barbui, C., Purgato, M., Steinhausen, H.-C., Shokraneh, F., Xia, J., & Cipriani, A. (2018). Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: A systematic review and network meta-analysis. The Lancet Psychiatry, 5(9), 727–738. https://doi.org/10.1016/S2215-0366(18)30269-4
Demontis, D., Walters, G. B., Athanasiadis, G., Walters, R., Therrien, K., Nielsen, T. T., Farajzadeh, L., Voloudakis, G., Bendl, J., Zeng, B., Zhang, W., Grove, J., Als, T. D., Duan, J., Satterstrom, F. K., Bybjerg-Grauholm, J., Bækved-Hansen, M., Gudmundsson, O. O., Magnusson, S. H., … Børglum, A. D. (2023). Genome-wide analyses of ADHD identify 27 risk loci, refine the genetic architecture and implicate several cognitive domains. Nature Genetics, 55(2), 198–208. https://doi.org/10.1038/s41588-022-01285-8
Demontis, D., Walters, R. K., Martin, J., Mattheisen, M., Als, T. D., Agerbo, E., Baldursson, G., Belliveau, R., Bybjerg-Grauholm, J., Bækvad-Hansen, M., Cerrato, F., Chambert, K., Churchhouse, C., Dumont, A., Eriksson, N., Gandal, M., Goldstein, J. I., Grasby, K. L., Grove, J., … Neale, B. M. (2019). Discovery of the first genome-wide significant risk loci for attention deficit/hyperactivity disorder. Nature Genetics, 51(1), 63–75. https://doi.org/10.1038/s41588-018-0269-7
Dougherty, D. D., Bonab, A. A., Spencer, T. J., Rauch, S. L., Madras, B. K., & Fischman, A. J. (1999). Dopamine transporter density in patients with attention deficit hyperactivity disorder. The Lancet, 354(9196), 2132–2133. https://doi.org/10.1016/S0140-6736(99)04030-1
Faraone, S. V., & Larsson, H. (2019). Genetics of attention deficit hyperactivity disorder. Molecular Psychiatry, 24(4), 562–575. https://doi.org/10.1038/s41380-018-0070-0
Franke, B., Michelini, G., Asherson, P., Banaschewski, T., Bilbow, A., Buitelaar, J. K., Cormand, B., Faraone, S. V., Ginsberg, Y., Haavik, J., Kuntsi, J., Larsson, H., Lesch, K.-P., Ramos-Quiroga, J. A., Réthelyi, J. M., Ribasés, M., & Reif, A. (2018). Live fast, die young? A review on the developmental trajectories of ADHD across the lifespan. European Neuropsychopharmacology, 28(10), 1059–1088. https://doi.org/10.1016/j.euroneuro.2018.08.001
Gallagher, R., & Rosenblatt, J. L. (2013). Attention-deficit/hyperactivity disorder predominantly inattentive type. In L. A. Reddy, A. S. Weissman, & J. B. Hale (Eds.), Neuropsychological assessment and intervention for youth: An evidence-based approach to emotional and behavioral disorders (pp. 155–176). American Psychological Association. https://doi.org/10.1037/14091-007
Gibbins, C., Weiss, M. D., Goodman, D. W., Hodgkins, P. S., Landgraf, J. M., & Faraone, S. V. (2010). ADHD-hyperactive/impulsive subtype in adults. Mental Illness, 2(1), 41-45. https://doi.org/10.4081/mi.2010.e9
Kooij, J. J. S., Bijlenga, D., Salerno, L., Jaeschke, R., Bitter, I., Balázs, J., Thome, J., Dom, G., Kasper, S., Nunes Filipe, C., Stes, S., Mohr, P., Leppämäki, S., Casas, M., Bobes, J., McCarthy, J. M., Richarte, V., Kjems Philipsen, A., Pehlivanidis, A., … Asherson, P. (2019). Updated European Consensus Statement on diagnosis and treatment of adult ADHD. European Psychiatry, 56(1), 14–34. https://doi.org/10.1016/j.eurpsy.2018.11.001
Limberg, B., Peña, R. M., Davidson, B., & Yeagley, C. B. (2018). F90.0 Attention-deficit hyperactivity disorder. In J. B. Schaffer & E. Rodolfa (Eds.), An ICD–10–CM casebook and workbook for students: Psychological and behavioral conditions (pp. 203–215). American Psychological Association. https://doi.org/10.1037/0000069-017
Polanczyk, G., de Lima, M. S., Horta, B. L., Biederman, J., & Rohde, L. A. (2007). The worldwide prevalence of ADHD: A systematic review and metaregression analysis. American Journal of Psychiatry, 164(6), 942–948. https://doi.org/10.1176/ajp.2007.164.6.942
Sedgwick, J. A., Merwood, A., & Asherson, P. (2019). The positive aspects of attention deficit hyperactivity disorder: A qualitative investigation of successful adults with ADHD. Attention Deficit and Hyperactivity Disorders, 11(3), 241–253. https://doi.org/10.1007/s12402-018-0277-6
Sonuga-Barke, E. J. S. (2003). The dual pathway model of AD/HD: An elaboration of neuro-developmental characteristics. Neuroscience & Biobehavioral Reviews, 27(7), 593–604. https://doi.org/10.1016/j.neubiorev.2003.08.005
Soto, E. F., Black, K., & Kofler, M. J. (2024). Is hyperactivity in children with attention deficit/hyperactivity disorder (ADHD) a functional response to demands on specific executive functions or cognitive demands in general? Neuropsychology, 38(8), 699–713.
Stanton, K., Forbes, M. K., & Zimmerman, M. (2018). Distinct dimensions defining the Adult ADHD Self-Report Scale: Implications for assessing inattentive and hyperactive/impulsive symptoms. Psychological Assessment, 30(12), 1549. https://doi.org/10.1037/pas0000604
Volkow, N. D., Wang, G.-J., Kollins, S. H., Wigal, T. L., Newcorn, J. H., Telang, F., Fowler, J. S., Zhu, W., Logan, J., Ma, Y., Pradhan, K., Wong, C., & Swanson, J. M. (2009). Evaluating dopamine reward pathway in ADHD: Clinical implications. JAMA, 302(10), 1084–1091. https://doi.org/10.1001/jama.2009.1308
Young, S., Adamo, N., Ásgeirsdóttir, B. B., Branney, P., Beckett, M., Colley, W., Cubbin, S., Deeley, Q., Farrag, E., Gudjonsson, G., Hill, P., Hollingdale, J., Kilic, O., Lloyd, T., Mason, P., Paliokosta, E., Perecherla, S., Sedgwick, J., Skirrow, C., … Woodhouse, E. (2020). Females with ADHD: An expert consensus statement taking a lifespan approach providing guidance for the identification and treatment of attention-deficit/hyperactivity disorder in girls and women. BMC Psychiatry, 20(1), 404. https://doi.org/10.1186/s12888-020-02707-9

