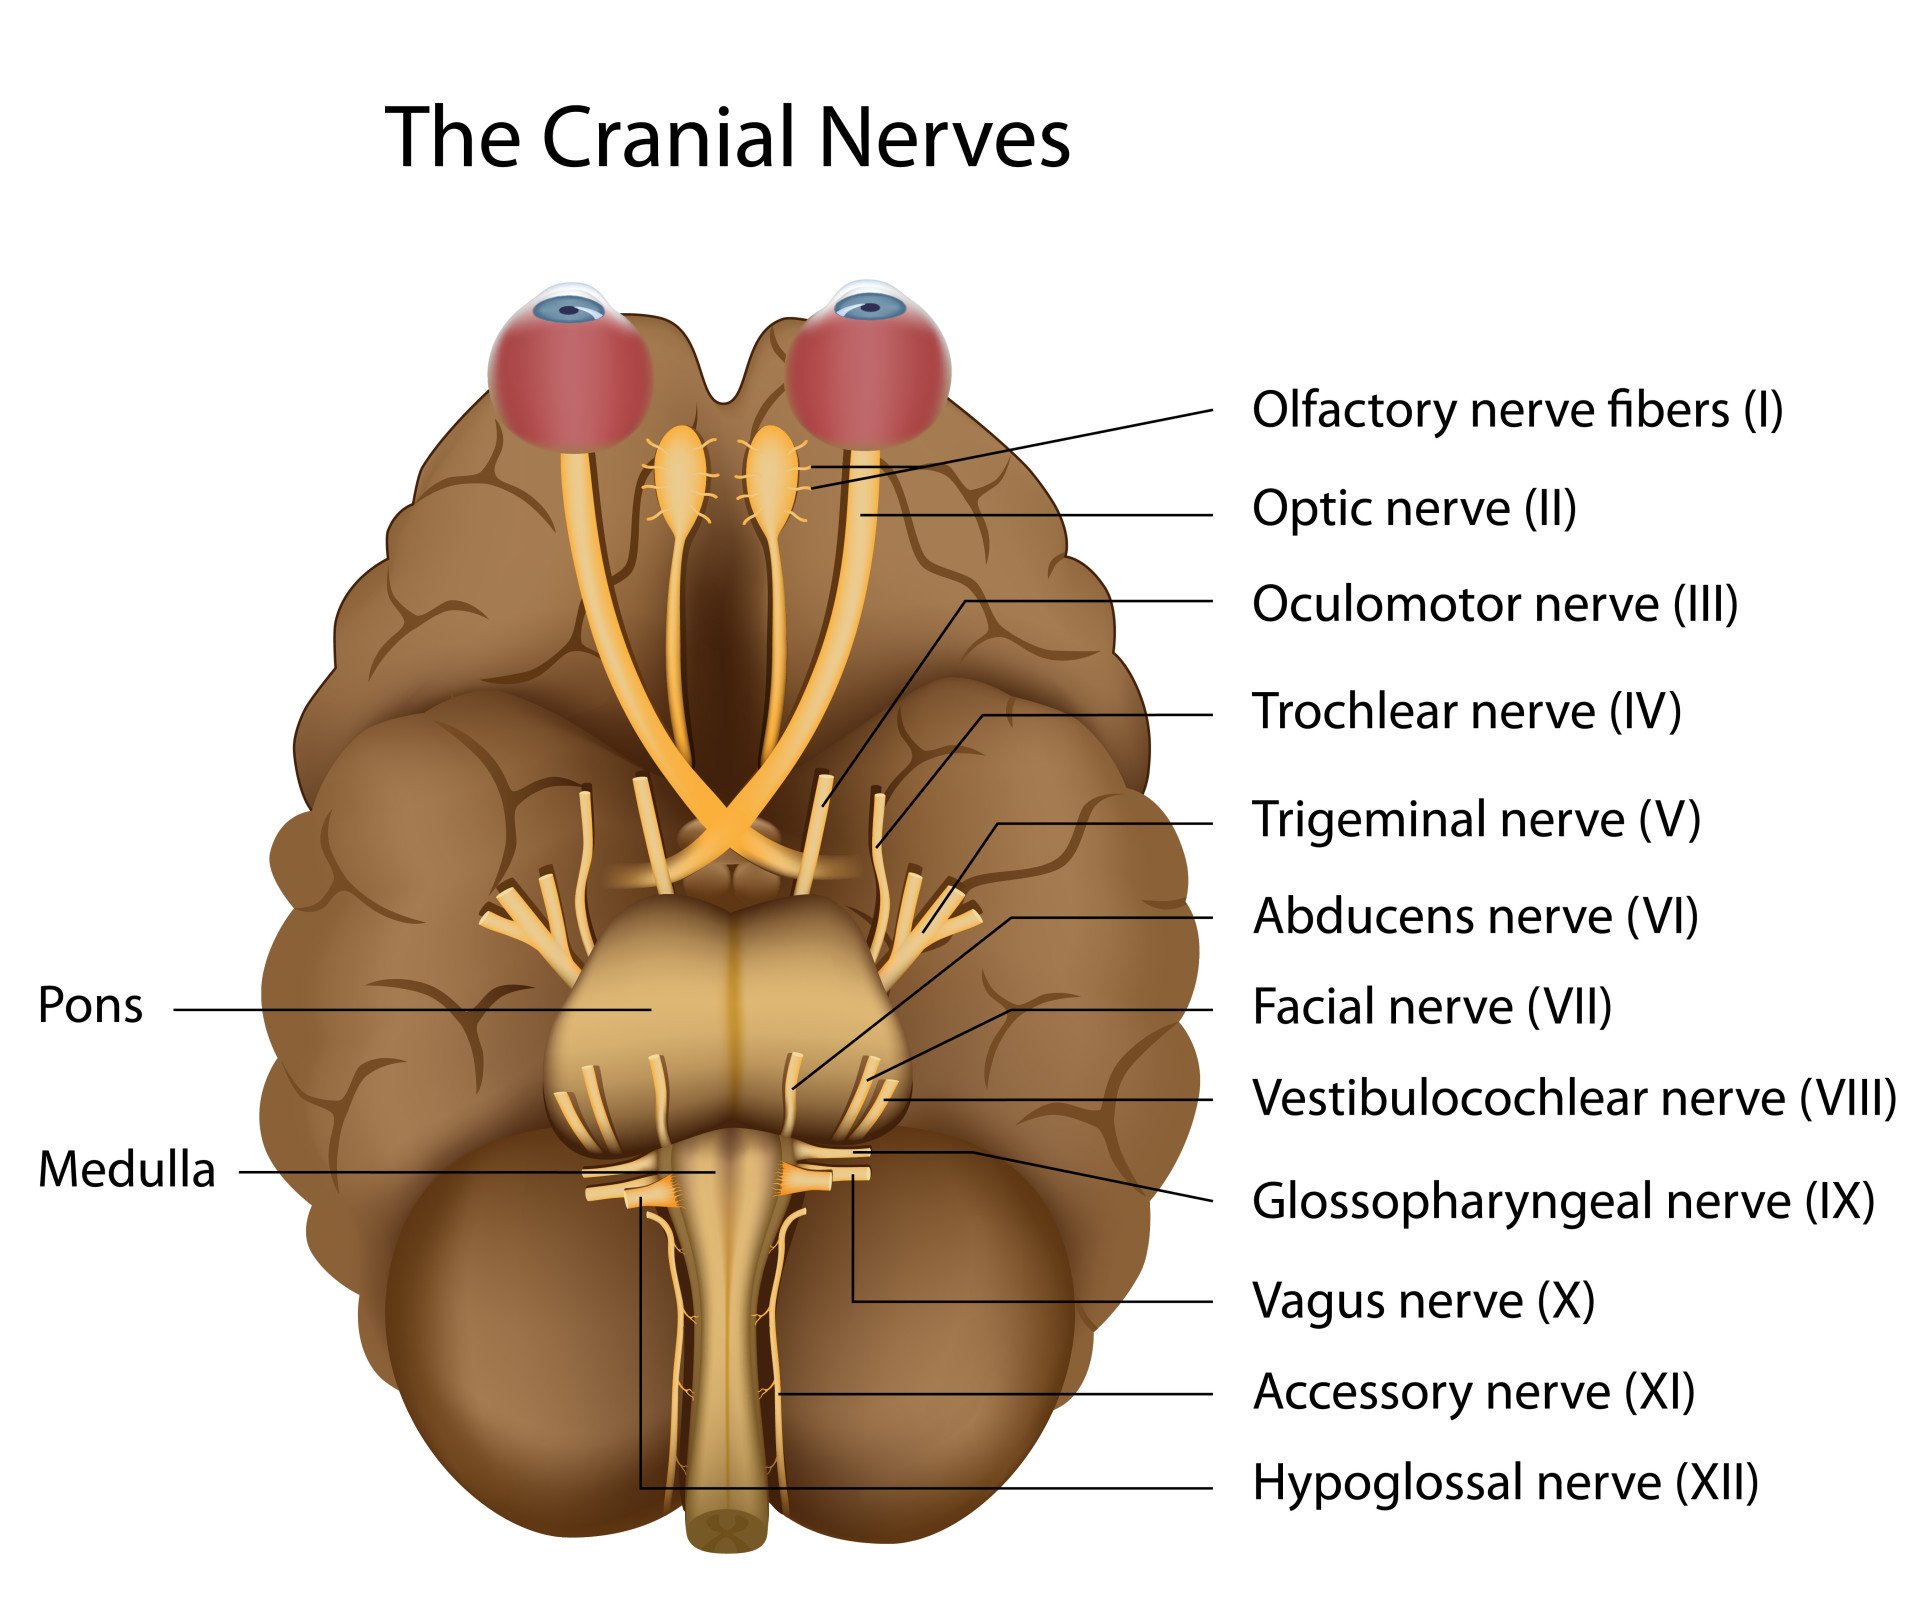
The 12 pairs of cranial nerves are specialized bundles of axons that connect the brain directly to the head, neck, and trunk. Unlike most nerves, they bypass the spinal cord entirely, allowing for rapid transmission of sensory and motor data.
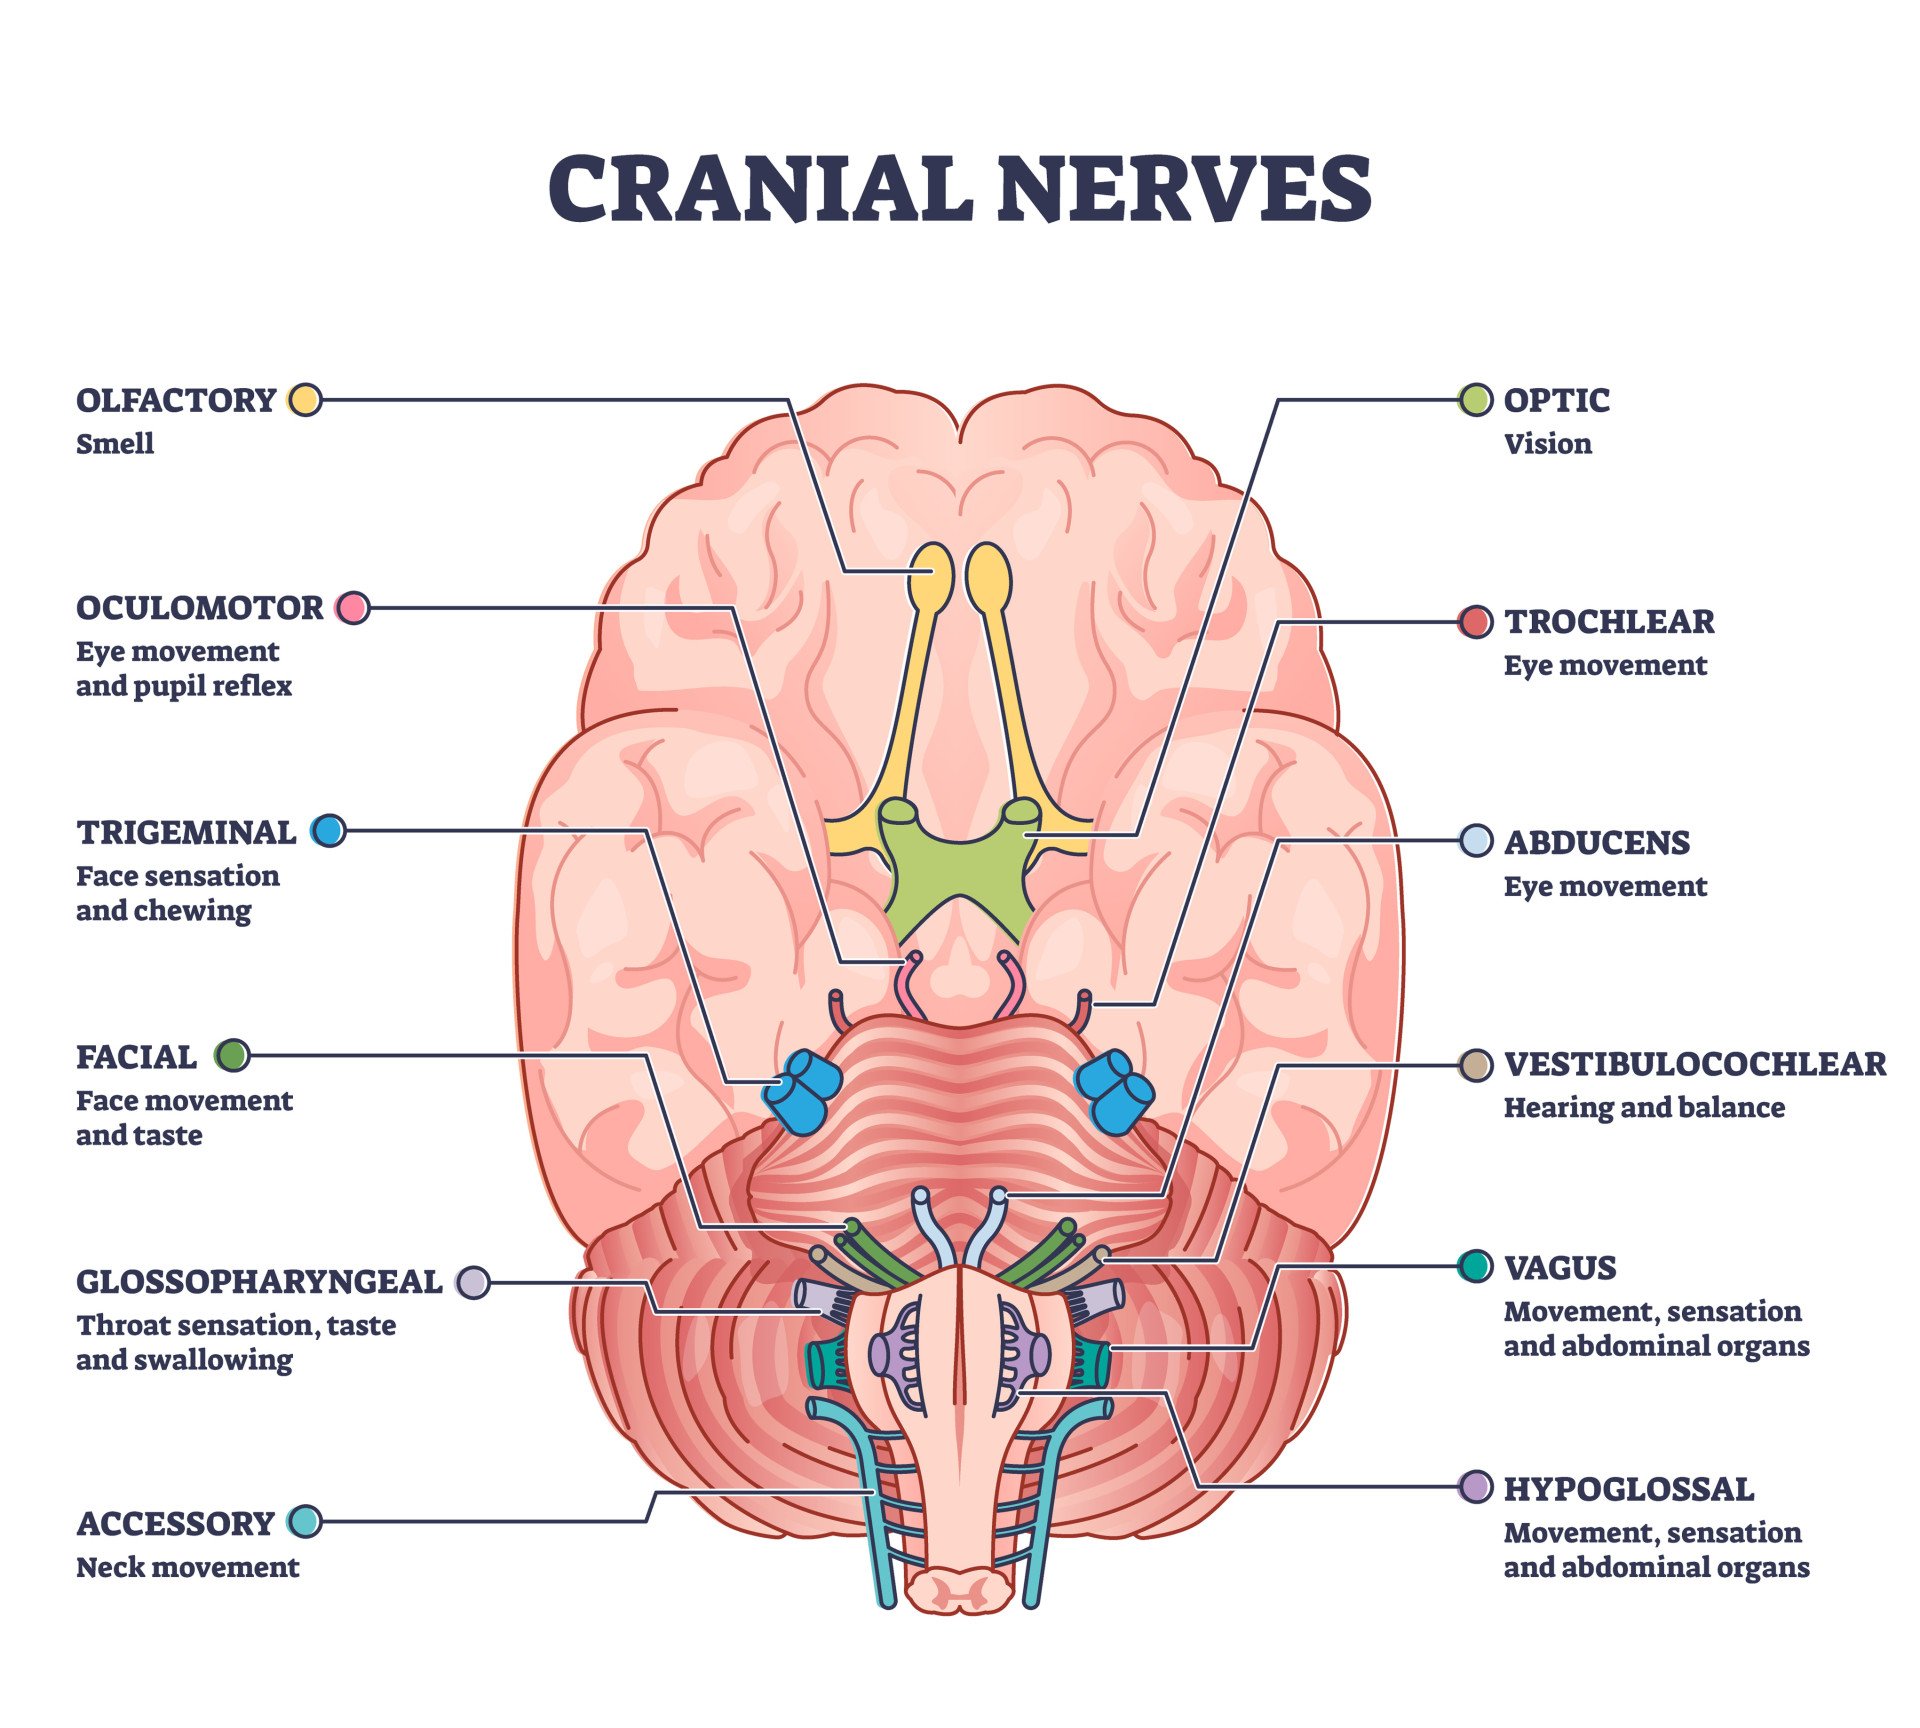
Anatomical Origins
While these nerves are part of the Peripheral Nervous System (PNS), they originate from specific nuclei (clusters of cell bodies) within the brain.
Their exit points are used to categorize them:
-
The Cerebrum (Forebrain): The Olfactory (I) and Optic (II) nerves originate here.
-
The Brainstem: The remaining ten nerves originate from this region, which is the “control center” for life-sustaining functions.
-
Midbrain: Oculomotor (III) and Trochlear (IV).
-
Pons: Trigeminal (V), Abducens (VI), Facial (VII), and Vestibulocochlear (VIII).
-
Medulla Oblongata: Glossopharyngeal (IX), Vagus (X), and Hypoglossal (XII).
-
-
The Spinal Cord: Uniquely, the Accessory (XI) nerve has nuclei located in the upper cervical spinal cord.
Functional Roles
Each nerve is categorized by its modality, the type of information it carries, whether sensory, motor, or both:
-
Sensory: Relays information like sight, smell, and balance to the brain.
-
Motor: Sends commands to muscles (e.g., eye movement) or glands (e.g., saliva production).
-
Mixed: Contains both sensory and motor fibers.
Reach and Range
Most cranial nerves stay within the head and neck.
However, the Vagus Nerve (X) is the notable exception. It “wanders” (hence the name Vagus) down into the thorax (chest) and abdomen, regulating the heart, lungs, and digestive system.
Cranial Nerve Modalities
Each type of cranial nerve has either sensory functions, motor functions, or both, known as modalities.
We categorize these based on the direction of the impulse:
-
Sensory (Afferent): Carry impulses from receptors to the CNS.
-
Motor (Efferent): Carry impulses from the CNS to effectors (muscles/glands).
-
Mixed: Contain both sensory and motor neurons.
To remember whether a nerve is Sensory, Motor, or Both (Mixed), use this classic sentence:
Some Say Marry Money But My Brother Says Big Brains Matter More.
| Nerve | I | II | III | IV | V | VI | VII | VIII | IX | X | XI | XII |
| Type | S | S | M | M | B | M | B | S | B | B | M | M |

Sensory modalities
1. Visual Modality (Vision)
-
Stimulus: Light waves.
-
Pathway: Photoreceptors in the retina convert light into electrical signals.
-
Cranial Nerve: Optic Nerve (CN II).
-
Psychology Link: This is the foundation for studying top-down vs. bottom-up processing and visual perception.
2. Auditory Modality (Hearing)
-
Stimulus: Sound waves (vibrations in the air).
-
Pathway: Hair cells in the cochlea (inner ear) detect vibrations.
-
Cranial Nerve: Vestibulocochlear Nerve (CN VIII).
-
Psychology Link: Essential for understanding language acquisition and the phonological loop in working memory.
3. Olfactory Modality (Smell)
-
Stimulus: Chemical molecules in the air.
-
Pathway: Odor molecules bind to receptors in the nasal cavity.
-
Cranial Nerve: Olfactory Nerve (CN I).
-
Psychology Link: This is the only sense that bypasses the thalamus and goes straight to the limbic system, which explains why smells are so strongly linked to emotion and memory.
4. Gustatory Modality (Taste)
-
Stimulus: Chemical molecules in food/liquid.
-
Pathway: Taste buds on the tongue detect sweet, sour, salty, bitter, and umami.
-
Cranial Nerves: Facial (CN VII), Glossopharyngeal (CN IX), and Vagus (CN X).
-
Psychology Link: Often studied alongside disgust, an evolutionary adaptation to avoid toxins.
5. Somatosensory Modality (Touch)
-
Stimulus: Pressure, temperature, and pain.
-
Pathway: Receptors in the skin and muscles.
-
Cranial Nerve: For the face, this is the Trigeminal Nerve (CN V). (Touch for the rest of the body travels through spinal nerves).
6. Vestibular Modality (Balance)
-
Stimulus: Gravity and head movement.
-
Pathway: Semicircular canals in the inner ear.
-
Cranial Nerve: Vestibulocochlear Nerve (CN VIII).
-
Psychology Link: This “hidden sense” is vital for spatial awareness and coordinating movement.
Motor modalities
1. Somatic Motor Modality (Voluntary)
This is the system you use when you choose to move.
These nerves control the skeletal muscles. These are responsible for things like facial expressions, speaking, and eye movement.
-
Eye Movement: Controlled by CN III (Oculomotor), CN IV (Trochlear), and CN VI (Abducens).
-
Facial Expressions: Managed by CN VII (Facial). This is huge in psychology for studying Ekman’s Universal Emotions.
-
Speech and Swallowing: Handled by CN IX (Glossopharyngeal), CN XI (Accessory), and CN XII (Hypoglossal).
-
Chewing: Controlled by the motor branch of CN V (Trigeminal).
2. Visceral Motor Modality (Involuntary/Autonomic)
This is part of the Autonomic Nervous System (ANS). You don’t consciously control these; your brain does it automatically to keep you alive.
-
The Parasympathetic System: Often called the “Rest and Digest” system.
-
The Main Player: CN X (The Vagus Nerve). It sends motor signals to the heart (to slow it down), the lungs (to constrict airways), and the digestive tract (to speed up digestion).
-
Pupil Constriction: CN III (Oculomotor) also has a visceral motor component that shrinks your pupils in bright light.
3. Special Branchial Motor Modality
This is a fancy term often used in higher-level biology for muscles that evolved from the “gills” (arch structures) in embryos.
-
Psychological Relevance: These nerves control the muscles involved in social communication—smiling, frowning, and vocalizing.
-
Nerves involved: CN V, VII, IX, and X.
12 Cranial Nerves
There are 12 pairs of cranial nerves attached to the brain. The cranial nerves are named after the body parts that they serve, and are also assigned Roman numerals, based off their location from front to back.

Mnemonic for Order of Cranial Nerves:
Oh, Oh, Oh, To Touch And Feel Very Good Velvet, such- A Heaven
Another mnemoic is as follows:
- Old: Olfactory
- Operators: Optic
- Occasionally: Oculomotor
- Troubleshoot: Trochlear
- Tricky: Trigeminal
- Abducted: Abducens
- Family: Facial
- Veterans: Vestibulocochlear
- Galloping: Glossopharyngeal
- Valiantly: Vagus
- Across: Accessory
- History: Hypoglossal
I. Olfactory Nerve
-
Location: Connects the nasal cavity to the forebrain.
-
Function: Carries smell information. Molecules trigger impulses that travel through the olfactory bulb to the limbic system (emotional center).
-
Modality: Sensory (Special Visceral).
-
Clinical Note: Damage leads to Anosmia (loss of smell).

II. Optic Nerve
-
Location: Connects the retina to the forebrain.
-
Function: Carries visual data. The nerves meet at the optic chiasm, where signals cross so each side of the brain processes a full field of vision.
-
Modality: Sensory (Special Somatic).
-
Clinical Note: Damage causes vision loss or blurring.
III. Oculomotor Nerve
-
Location: Originates in the midbrain.
-
Function: Controls most eye muscles for movement and focus. It handles Pupillary Constriction (constricting the pupil in bright light) and Lens Accommodation (thickening the lens to see near objects).
-
Modality: Motor (Somatic & Visceral).
-
Clinical Note: Damage causes droopy eyelids (ptosis) and double vision.
IV. Trochlear Nerve
-
Location: Emerges from the back of the midbrain.
-
Function: Stimulates the superior oblique muscle for specific eye movements (downward and inward).
-
Modality: Motor (Somatic).
-
Clinical Note: Damage makes it difficult to look down (e.g., when reading or walking downstairs). Patients often tilt their head to compensate for the double vision caused by this nerve’s dysfunction.
V. Trigeminal Nerve
-
Location: Emerges from the pons; the largest cranial nerve.
-
Structure: Has three distinct branches:
-
Ophthalmic (V1): Sensory for the forehead and upper eyelid.
-
Maxillary (V2): Sensory for the cheeks, upper lip, and nasal cavity.
-
Mandibular (V3): Mixed; sensory for the lower jaw and motor for the muscles of mastication (chewing).
-
-
Modality: Mixed (Somatic Sensory & Visceral Motor).
-
Clinical Note: Damage causes severe facial (“electric shock”) pain or numbness.
VI. Abducens Nerve
-
Location: Originates in the pons.
-
Function: Controls the lateral rectus muscle, which pulls the eye outward (away from the nose).
-
Modality: Motor (Somatic).
-
Clinical Note: Damage causes the eye to turn inward and results in double vision.
VII. Facial Nerve
-
Location: Originates in the pons.
-
Function: Controls all muscles used for facial expression (smiling, blinking, frowning).
-
Modality: Mixed (Sensory & Motor).
-
Clinical Note: Damage causes facial paralysis (e.g., Bell’s Palsy).
VIII. Vestibulocochlear Nerve
-
Location: Junction of the pons and medulla.
-
Function: Two specialized branches:
-
Vestibular: Balance and head orientation.
-
Cochlear: Hearing (sound volume and pitch).
-
-
Modality: Sensory (Special Somatic).
-
Clinical Note: Damage causes vertigo (spinning sensation), tinnitus (ringing), or deafness.
IX. Glossopharyngeal Nerve
-
Location: Originates in the medulla oblongata.
-
Function: Carries taste from the back 1/3 of the tongue, monitors blood pressure in the sinuses, and controls muscles used for swallowing.
-
Modality: Mixed (Sensory & Motor).
-
Clinical Note: Damage causes difficulty swallowing (dysphagia) and loss of taste.
X. Vagus Nerve
-
Location: Originates in the medulla; the longest cranial nerve.
-
Function: The “wandering” nerve. It controls the throat (larynx/pharynx) and carries parasympathetic signals to the heart and digestive organs.
-
Modality: Mixed (Sensory, Motor, and Autonomic).
-
Clinical Note: Damage causes hoarseness, swallowing issues, and digestive problems.
XI. Spinal Accessory Nerve
-
Location: Roots in the medulla and upper spinal cord. Formed by nerve roots in the upper spinal cord (C1–C5) that travel into the skull and back out.
-
Function: Controls the muscles of the neck and shoulders (shrugging and head turning) and aids in swallowing.
-
Modality: Motor (Somatic & Visceral).
-
Clinical Note: Damage makes it difficult to shrug the shoulders or turn the head.
XII. Hypoglossal Nerve
-
Location: Originates in the medulla.
-
Function: Provides motor control for almost all tongue movements used in speech and swallowing. Crucial for food manipulation, swallowing, and clear articulation (speech)
-
Modality: Motor (Somatic).
-
Clinical Note: Damage causes difficulty speaking and moving food in the mouth.
Common Disorders Affecting Cranial Nerves
Because cranial nerves are the “primary cables” for your senses and facial movements, any damage (a lesion) can significantly disrupt your daily life.
1. Why are they so vulnerable?
Unlike the spinal cord, which is encased in a heavy “suit of armor” (the vertebral column), many cranial nerves travel long, exposed paths along the skull surface.
They are often protected only by thin facial muscles and skin, making them highly susceptible to:
-
Physical Trauma: Head injuries or fractures to the base of the skull.
-
Vascular Issues: Strokes (loss of blood flow to the brainstem) or high blood pressure.
-
Metabolic Disorders: Diabetes can cause neuropathy (nerve damage), where high blood sugar damages the small blood vessels supplying the nerves.
-
Compression: Brain tumors or infections (like meningitis) can press against the nerves.
2. Specific Symptoms (The Clinical Link)
In biology, we link structure to function. When the structure is damaged, the specific function fails:
-
Olfactory (I): Causes Anosmia. Interestingly, because smell and taste are linked in the brain, patients often report that food has “lost its flavor.”
-
Optic (II): Leads to visual field defects. Severe damage can result in total blindness in one or both eyes.
-
Facial (VII): Causes Bell’s Palsy. This is specific—it usually affects only one side of the face, preventing the patient from blinking or smiling on that side.
3. General Red Flags
When multiple nerves are affected, patients often experience:
-
Sensory Loss: Numbness, tingling, or “electric shock” pains (common in Trigeminal nerve damage).
-
Motor Loss: Muscle weakness, drooping (like a droopy eyelid, known as ptosis), or total paralysis.
-
Coordination Issues: Double vision (nerves III, IV, or VI) or balance problems (nerve VIII).
4. Prevention and Recovery
The nervous system has limited regenerative abilities.
While some “neuropathies” (nerve disorders) recover with physical therapy or medication, others are permanent.
Real-World Applications
The nerve-by-nerve anatomy above is not just textbook detail. Clinicians, therapists, and researchers use knowledge of the cranial nerves every day, in settings from the sports sideline to the psychiatrist’s office.
Clinical Neurology and Psychiatry
The bedside cranial nerve exam remains one of the fastest ways to localise a neurological problem before any brain scan is available. It tests each nerve in turn: smell, vision, eye movement, facial sensation, hearing, the gag reflex, shoulder shrug, and tongue movement.
This can narrow things down fast, before any scan.
Because each nerve’s control centre sits at a known point in the brainstem, a specific pattern of symptoms can point to the exact site of damage. A droopy eyelid with a dilated pupil points to the oculomotor nerve and the midbrain (Sonne & Lopez-Ojeda, 2020).
This is called clinico-anatomical correlation.
The vagus nerve’s reach into mood-regulating brain regions has made it a target for psychiatric treatment too. Vagus nerve stimulation (VNS) is now an FDA-approved add-on therapy for depression that has not responded to other treatments.
Full details sit in Critical Evaluation above.
Public Health and Sports Medicine
The COVID-19 pandemic turned the sense of smell into an unlikely public-health screening tool. The virus damages the supporting cells of the olfactory epithelium and often causes a sudden, complete loss of smell.
Testing smell became a cheap screening shortcut.
The study behind this approach, and how well it held up, is examined in the Critical Evaluation section above.
Standardised sideline concussion tools build in rapid checks of cranial-nerve function: pupil symmetry, smooth eye tracking, and balance. These signs are fast and need no equipment.
They are sensitive markers of brainstem and cerebellar disturbance after a head impact, because these functions map onto specific cranial-nerve pathways. A player who cannot track a moving finger smoothly, or who shows abnormal eye reflexes, is pulled from play.
Speech-Language Therapy and Audiology
Speech and language therapists work directly with the motor cranial nerves. After a stroke, dysphagia, difficulty swallowing, is treated by retraining the nerves that control the throat and tongue.
Slurred speech, or dysarthria, needs the same nerves. It also needs the facial nerve’s control of the lips to shape clear sounds.
Facial nerve palsy, most often Bell’s palsy, responds best to corticosteroids started within 72 hours, combined with structured facial exercises. Early movement retraining improves the odds of full recovery.
Cochlear implants put the same cranial-nerve anatomy to direct engineering use. When the hair cells of the cochlea are destroyed but the nerve itself survives, an implant bypasses the damaged cells entirely.
It sends signals straight to the hearing nerve. This restores a usable, if not entirely natural-sounding, hearing signal.
Critical Evaluation
The nerve-by-nerve map above is a useful teaching simplification, but three lines of modern evidence, and one live theoretical dispute, show its limits.
A Simplified Model of Sensory Integration
Textbook lists like the one above (Optic nerve to vision, Vestibulocochlear nerve to hearing) are useful. But they understate how much perception depends on combining several nerves’ input at once.
The McGurk effect shows this clearly. Watching a face mouth “ga” while hearing “ba” makes most listeners perceive an entirely different sound, “da” (McGurk & MacDonald, 1976).
A single-nerve account cannot explain this. Real perception needs cross-modal integration in the brain’s cortex, combining signals in a way the nerve-by-nerve breakdown, by design, does not cover.
This is not a flaw in the breakdown above. Describing the wiring at the periphery is necessary, but it is not sufficient to explain integrated perception.
It is a reductionism-versus-holism trade-off common across biopsychology: explaining the parts is not the same as explaining the whole.
Contemporary Research
Three recent, well-designed studies update the classical picture above, and each tests how far a single nerve’s signal can be trusted on its own.
- Aim: Moein et al. (2020) tested whether smell loss could signal COVID-19 infection.
- Method: 60 hospitalised COVID-19 patients and 60 matched controls completed a validated 40-item smell test.
- Results: 98% of patients showed measurable smell loss, a quarter of them completely, regardless of how ill they otherwise felt.
- Conclusion: Smell testing could work as a cheap, early screening tool for the virus.
A larger meta-analysis of 27,492 patients later put the true rate closer to 48%. It varied sharply by country and by whether smell was tested objectively or just self-reported (Saniasiaya et al., 2021).
- Aim: Strack et al. (1988) tested whether facial-muscle activity alone can shape how funny something feels.
- Method: Participants rated cartoons while holding a pen between their teeth, forcing a smile, or between their lips, blocking one.
- Results: The “smiling” group rated the cartoons about 0.82 points funnier on a 10-point scale.
- Conclusion: Facial nerve activity was said to shape emotion directly, not just express it.
This became one of psychology’s most cited studies. A pre-registered replication across 17 labs and 1,894 participants then found an effect of just 0.03 points, statistically no different from zero (Wagenmakers et al., 2016).
Being video-recorded may explain part of the gap: feeling observed seems to switch the effect off (Noah et al., 2018).
- Aim: Aaronson et al. (2017) compared long-term outcomes for treatment-resistant depression with and without vagus nerve stimulation.
- Method: The study followed 795 patients across 61 US sites for five years in an open, non-randomised registry.
- Results: VNS patients showed a 67.6% five-year response rate, versus 40.9% for usual treatment.
- Conclusion: Adjunctive VNS produced a durable antidepressant benefit in a hard-to-treat population.
Because patients were not randomly assigned or blind to their treatment, this open-label result sits below a controlled trial in the evidence hierarchy. Earlier short-term, sham-controlled trials found smaller effects.
VNS’s popularity in trauma therapy also rests partly on Porges’s (2007) polyvagal theory, whose central physiological claims Grossman (2023) has since directly disputed.
Alternative Perspectives
The sensory/motor scheme used throughout this article is a teaching simplification. It is not the whole story.
Clinical neuroanatomy more often classifies nerve fibres by their embryological origin instead. This explains why the facial, glossopharyngeal, and vagus nerves share a “special visceral” fibre type: they control muscles that develop from the same embryonic gill-like arches.
A similar simplification applies to emotion theory too.
The weak, easily-switched-off facial-feedback effect fits a “constructionist” view of emotion better than the older idea that facial-muscle signals alone cause a feeling.
On this newer view, facial feedback only nudges judgement under the right conditions, rather than triggering emotion on its own.
A parallel dispute concerns the vagus nerve itself. Polyvagal theory treats one specific, newer branch of vagal control as uniquely responsible for feelings of safety and social connection. This specific evolutionary claim is exactly what Grossman (2023) disputes.
Key Takeaways
- Direct Connection: The 12 cranial nerves connect the brain directly to the head, neck, and trunk, without routing through the spinal cord.
- Brainstem Origin: Ten of the twelve nerves originate in the brainstem; only the Olfactory and Optic nerves start in the cerebrum.
- Modality Types: Each nerve is classified by its modality: carrying signals to the brain (sensory), from the brain (motor), or both (mixed).
- The Vagus Wanders: Unlike the others, the Vagus nerve (X) travels down into the chest and abdomen to regulate the heart, lungs, and digestion.
- A Diagnostic Tool: Testing each nerve at the bedside helps clinicians localise brain damage before any scan is available.
- Facial Feedback: A famous study claimed smiling alone boosts mood, but a large modern replication found almost no effect.
- Highly Exposed: Many cranial nerves travel exposed, unprotected paths near the skull surface, making them vulnerable to injury, infection, and disease.
References
Aaronson, S. C., Sears, P., Ruvuna, F., Bunker, M., Conway, C. R., Dougherty, D. D., Reimherr, F. W., Schwartz, T. L., & Zajecka, J. M. (2017). A 5-year observational study of patients with treatment-resistant depression treated with vagus nerve stimulation or treatment as usual: Comparison of response, remission, and suicidality. American Journal of Psychiatry, 174(7), 640–648. https://doi.org/10.1176/appi.ajp.2017.16010034
Cedars Sinai (n.d.). Cranial Neuropathies. Retrieved July 21, 2021, from: https://www.cedars-sinai.org/health-library/diseases-and-conditions/c/cranial-neuropathies.html
Grossman, P. (2023). Fundamental challenges and likely refutations of the five basic premises of the polyvagal theory. Biological Psychology, 180, Article 108589. https://doi.org/10.1016/j.biopsycho.2023.108589
McGurk, H., & MacDonald, J. (1976). Hearing lips and seeing voices. Nature, 264, 746–748. https://doi.org/10.1038/264746a0
Moein, S. T., Hashemian, S. M., Mansourafshar, B., Khorram-Tousi, A., Tabarsi, P., & Doty, R. L. (2020). Smell dysfunction: A biomarker for COVID-19. International Forum of Allergy & Rhinology, 10(8), 944–950. https://doi.org/10.1002/alr.22587
Noah, T., Schul, Y., & Mayo, R. (2018). When both the original study and its failed replication are correct: Feeling observed eliminates the facial-feedback effect. Journal of Personality and Social Psychology, 114(5), 657–664. https://doi.org/10.1037/pspa0000121
Porges, S. W. (2007). The polyvagal perspective. Biological Psychology, 74(2), 116–143. https://doi.org/10.1016/j.biopsycho.2006.06.009
Saniasiaya, J., Islam, Q. U., & Abdullah, B. (2021). Prevalence of olfactory dysfunction in coronavirus disease 2019 (COVID-19): A meta-analysis of 27,492 patients. The Laryngoscope, 131(4), 865–878. https://doi.org/10.1002/lary.29286
Seladi-Schulman, J. (2019, March 14). The 12 Cranial Nerves. Healthline. https://www.healthline.com/health/12-cranial-nerves#x-vagus-nerve
Sonne, J., & Lopez-Ojeda, W. (2020). Neuroanatomy, cranial nerve. StatPearls [Internet].
Strack, F., Martin, L. L., & Stepper, S. (1988). Inhibiting and facilitating conditions of the human smile: A nonobtrusive test of the facial feedback hypothesis. Journal of Personality and Social Psychology, 54(5), 768–777. https://doi.org/10.1037/0022-3514.54.5.768
Teach Me Anatomy (n.d). Summary of the Cranial Nerves. Retrieved July 21, 2021, from: https://teachmeanatomy.info/head/cranial-nerves/summary/
Wagenmakers, E.-J., Beek, T., Dijkhoff, L., Gronau, Q. F., Acosta, A., Adams, R. B., Jr., Albohn, D. N., Allard, E. S., Benning, S. D., Blouin-Hudon, E.-M., Bulnes, L. C., Caldwell, T. L., Calin-Jageman, R. J., Capaldi, C. A., Carfagno, N. S., Chasten, K. T., Cleeremans, A., Connell, L., DeCicco, J. M., … Zwaan, R. A. (2016). Registered replication report: Strack, Martin, & Stepper (1988). Perspectives on Psychological Science, 11(6), 917–928. https://doi.org/10.1177/1745691616674458
Further Information