Adrenaline (epinephrine) is a powerful chemical messenger that acts primarily as a hormone released into the bloodstream by the adrenal glands. Although it shares structural similarities with neurotransmitters and may act in that role in rare cases, its central nervous system activity is largely mediated by norepinephrine.
Adrenaline is produced and released by the adrenal glands, especially the adrenal medulla, in response to sympathetic nervous system activity. Its job: prepare the body for “fight or flight.”
This involves increasing heart rate, blood pressure, respiration, and releasing energy reserves to muscles. These widespread effects are sustained as it circulates through the bloodstream.
Key Takeaways
- Dual Role: Adrenaline works mainly as a hormone in the bloodstream; its close relative noradrenaline does most of the brain’s neurotransmitter work.
- Fight-or-Flight: It triggers the body’s rapid stress response, raising heart rate, blood pressure and blood sugar to prepare for action.
- Limited Brain Access: Adrenaline barely crosses the blood-brain barrier, so most of its “mental” effects come from noradrenaline instead.
- Emotion Theories: Classic experiments injecting adrenaline showed that bodily arousal alone rarely creates a specific emotion; interpretation matters too.
- Memory Boost: Adrenaline released during arousing events strengthens memory via the amygdala, an effect blocked by beta-blocker drugs like propranolol.
- Modern Evidence: A 2018 meta-analysis found no reliable “fingerprint” linking specific emotions to specific patterns of bodily arousal.
Adrenaline: Hormone vs. Neurotransmitter
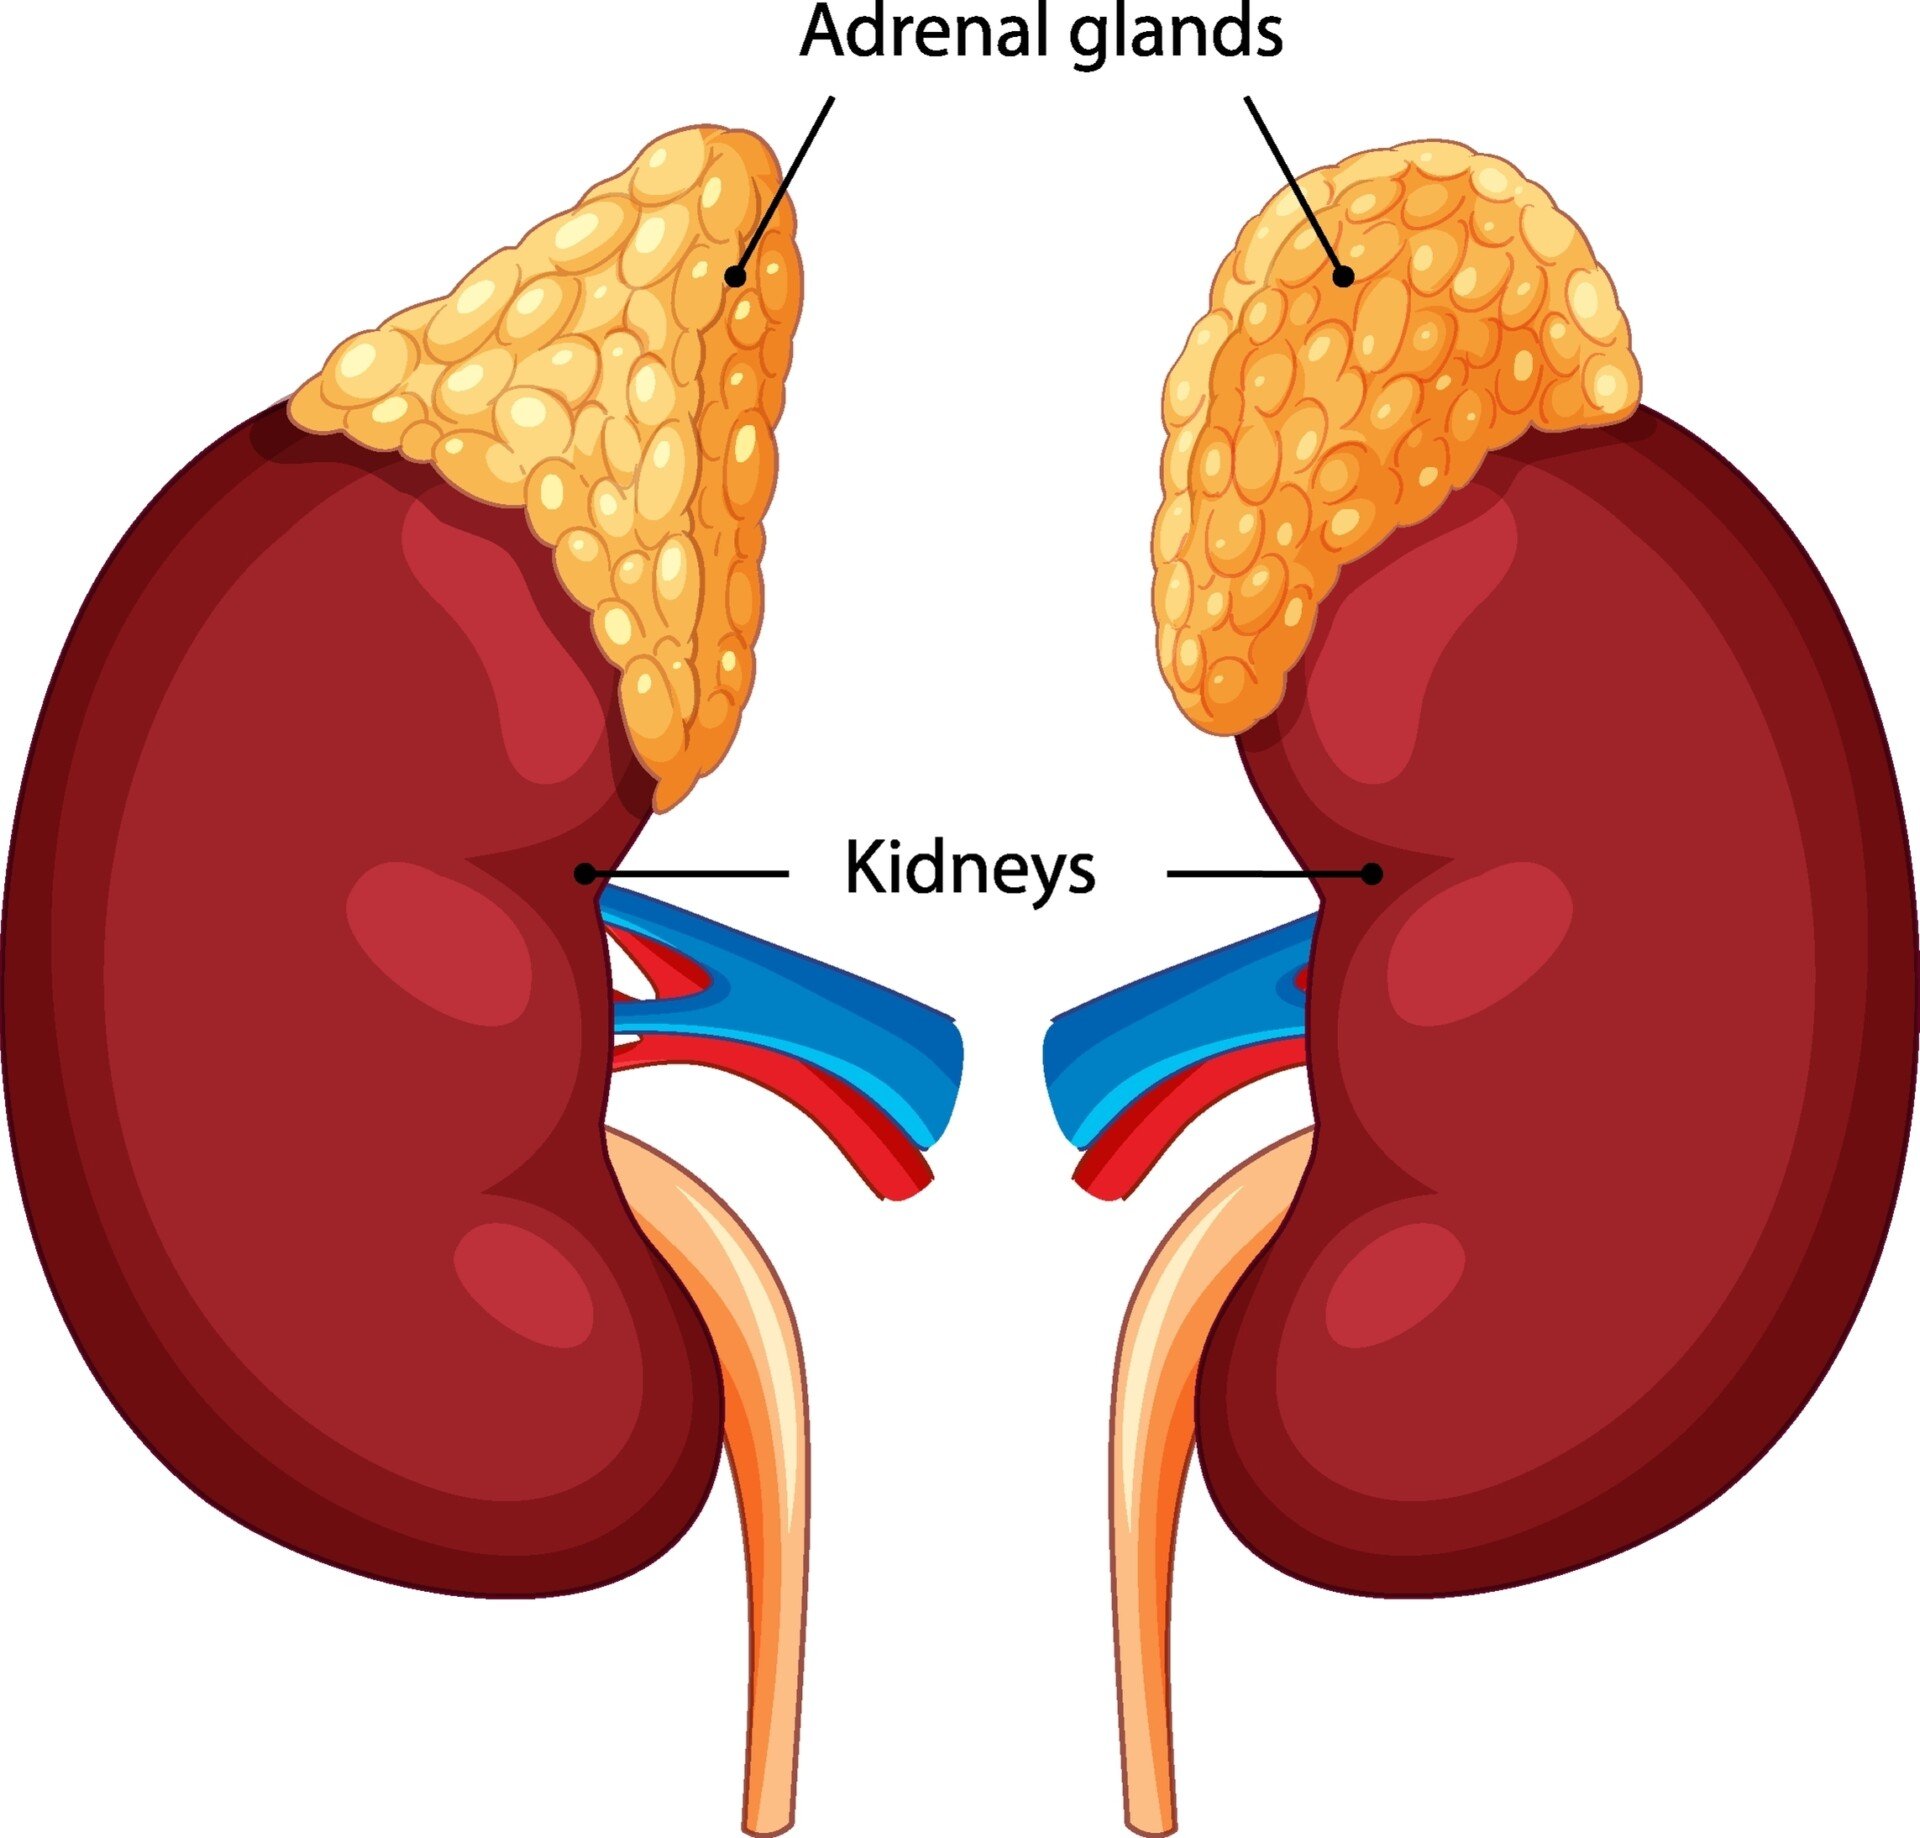
Adrenaline can act in two different ways, and mixing them up is a common mistake. As a hormone, it is produced by the adrenal glands, located atop the kidneys, and secreted directly into the bloodstream.
This lets it travel throughout the entire body. Hormonal responses are generally slower, often taking minutes to influence target cells, but their effects reach every organ and last longer.
As a neurotransmitter, adrenaline is released by specific neurons directly into the tiny gap between one neuron and the next, called a synapse. This is almost instantaneous, working on a millisecond timescale, but it only affects the one cell being signalled to.
In practice, adrenaline itself rarely takes this second route. Its close relative noradrenaline is the neurotransmitter the nervous system uses far more often. Most of adrenaline’s own contribution to arousal therefore comes through the bloodstream, not the synapse.
Adrenaline vs noradrenaline
- Adrenaline (Epinephrine): Released by adrenal glands into the bloodstream, it primarily triggers widespread physical responses like increased heart rate, blood pressure, and energy supply to muscles.
- Noradrenaline (Norepinephrine), adrenaline’s close chemical cousin: primarily functions as a neurotransmitter released at synapses by specific neurons in the brain and spinal cord, and is more involved in cognitive alertness.
Adrenaline’s role as a hormone
Below describes adrenaline’s role as a hormone in the body:
Release and Circulation
As a hormone, adrenaline is primarily produced and secreted by the adrenal glands, which are located on top of the kidneys.
Unlike neurotransmitters that act locally at synapses, hormones like adrenaline are released directly into the bloodstream. This allows it to travel throughout the entire body to reach its target cells and organs.
This release does not happen randomly. It follows a specific route called the sympathetic-adrenal-medullary (SAM) pathway.
When the brain judges a situation as threatening, the hypothalamus activates the sympathetic nervous system. Nerve fibres run directly from the spinal cord to the adrenal medulla.
There, the gland acts almost like a nerve cell itself. Instead of passing the signal on to another neuron, it releases its messenger straight into the blood. That messenger acts as a hormone.
About 80% of what the adrenal medulla releases is adrenaline, with most of the rest noradrenaline. This hormonal route builds slightly more slowly than a direct nerve signal, because it must diffuse through the blood.
It also fades more slowly, so a surge of arousal can linger for several minutes after a scare has passed.
Role in “Fight-or-Flight” Response
Adrenaline’s main function as a hormone is to prepare the body for the “fight-or-flight” response during stressful or emergency situations. This involves a cascade of widespread physiological changes including:
- Increased heart rate and blood pressure.
- Dilated pupils.
- Increased respiration and sweating.
- Release of energy reserves (like glucose from the liver) to muscles.
- Reduction of non-vital functions, such as gastrointestinal activity and urinary requirements.
These effects are slower to take hold than neurotransmitter actions, but they are more widespread. They also tend to last longer, sustaining the body’s readiness for action after the initial neural response fades.

The Wider Stress Response: SAM and HPA Together
Adrenaline is only half of the body’s stress response. The fast SAM pathway described above kicks in within seconds and fades within minutes. It drives the opening alarm.
Running alongside it, but building and fading more slowly over minutes to hours, is the hypothalamic-pituitary-adrenal (HPA) axis, shown above. In the HPA axis, the hypothalamus releases a hormone that triggers the pituitary gland.
This signals the adrenal cortex, not the medulla, to release the steroid hormone cortisol. Cortisol takes over from here.
It keeps the body alert and energised for far longer than adrenaline can, though prolonged release comes at the cost of a weakened immune system. Hans Selye’s general adaptation syndrome describes how the two systems combine over time.
An initial alarm stage, driven by the fast adrenaline surge, gives way to a resistance stage in which the slower cortisol response takes over. Exhaustion can follow if the stressor persists.
Adrenaline’s Role in the Brain
While adrenaline (epinephrine) and noradrenaline (norepinephrine) are chemically similar, it is norepinephrine that primarily functions as a neurotransmitter in the brain.
Adrenaline’s activity within the brain is limited, as it does not readily cross the blood-brain barrier.
Most of the central effects commonly attributed to “adrenaline” are actually mediated by norepinephrine, which plays a key role in the brain’s response to stress and arousal.
Increases Alertness, Arousal and Reaction Time
Norepinephrine enhances physiological arousal by increasing heart rate, blood pressure, and alertness. It comes from the locus coeruleus, a brainstem region. This region governs wakefulness, attention, and vigilance.
This noradrenergic activity prepares the body and brain for quick responses to potential threats. Activation of the sympathetic nervous system boosts norepinephrine levels at the same time, heightening sensory processing, sharpening reaction time, and freeing up energy reserves.
The two systems sit far apart in the body. The locus coeruleus is a brainstem nucleus, while adrenaline itself comes from the adrenal glands. Even so, the two normally rise and fall together, which is why “adrenaline” and “noradrenaline” are so often used as if they were interchangeable.
Involved in Emotion Regulation (Fear and Anxiety)
The amygdala, a key structure in the brain’s limbic system, is involved in processing fear and emotional salience. It interacts closely with noradrenergic pathways from the locus coeruleus.
Abnormal increases in norepinephrine activity are associated with heightened emotional reactivity and may contribute to panic attacks and anxiety disorders.
Certain medications that target this system can either provoke or reduce panic symptoms.
Helps Form Vivid Memories during Emotional Events
Emotionally intense experiences activate both the amygdala and stress hormone systems, including the release of norepinephrine and peripheral adrenaline.
These signals enhance the encoding of emotionally significant memories.
Although adrenaline itself doesn’t enter the brain, it influences memory indirectly by stimulating vagal nerve pathways and promoting norepinephrine release in the amygdala.
This interaction helps explain “flashbulb memories”—vivid, detailed recollections of emotionally charged events.
The clearest evidence that this system is doing real work comes from a classic experiment using a drug that blocks it.
- Aim: To test whether activating the beta-adrenergic system, the receptors adrenaline and noradrenaline act on, is necessary for emotional arousal’s memory-boosting effect.
- Method: Participants viewed either a neutral or an emotionally arousing slide-show story after taking the beta-blocker propranolol or a placebo. Their memory for story details was tested a week later.
- Results: The placebo group remembered the arousing story far better than the neutral one, as expected. The propranolol group showed no such advantage, even though they still felt just as aroused.
- Conclusion: Blocking the beta-adrenergic system removes the memory boost that emotional arousal normally provides, showing adrenaline and noradrenaline play a necessary role in it.
This finding, from Cahill, Prins, Weber and McGaugh (1994), is the reason researchers now describe emotional memory as chemically dependent on adrenaline and noradrenaline, not just psychologically vivid.

Adrenaline and the Theories of Emotion
Adrenaline is more than a stress hormone. Because researchers can inject it and precisely control a person’s arousal, it became the key tool for testing one of psychology’s oldest questions. Does a racing heart cause fear, or does fear cause a racing heart?
The James-Lange theory proposed a bold answer. People do not tremble because they are afraid; they feel afraid because they tremble (James, 1884).
Emotion, on this view, is simply the mind’s perception of the body’s own changes. If this is correct, injecting adrenaline to recreate those bodily changes should be enough, on its own, to produce a real emotion.
Cannon disagreed. Walter Cannon soon challenged James’s claim, aided by an adrenaline experiment the Spanish physician Gregorio Marañón had conducted decades earlier.
Marañón’s Adrenaline Experiment (1924)
Marañón’s experiment is the clearest test of James’s claim.
- Aim: To test whether injecting adrenaline to artificially produce bodily arousal was, on its own, enough to create a genuine emotion.
- Method: Marañón injected adrenaline into 210 participants and simply asked them to describe what they felt.
- Results: About 71% reported only physical symptoms with no emotion at all. Most others felt a cold “as if” state; only those prompted to recall an emotional memory felt a real emotion.
- Conclusion: Bodily arousal alone does not create emotion. It must be combined with an appropriate thought or context first.
Marañón’s finding, that arousal alone leaves most people emotionally flat unless paired with a meaningful thought, set the stage for the more famous experiment that followed decades later. It made the same point on a far larger scale.
Schachter and Singer’s Two-Factor Experiment (1962)
Schachter and Singer went further. Marañón’s insight was tested on a much larger scale by Stanley Schachter and Jerome Singer, in what became the Schachter-Singer two-factor theory of emotion.
- Aim: To test whether emotion needs both arousal and a cognitive label, and whether the same arousal, labelled differently, produces different emotions.
- Method: 185 male undergraduates were given adrenaline (told it was a “vitamin”) and assigned to be informed, misinformed, or told nothing about its real effects. Each then waited with a confederate acting either euphoric or angry.
- Results: Participants with no explanation for their arousal caught the confederate’s mood, reporting euphoria or anger depending only on who they were paired with. Informed participants, who understood their arousal, were unaffected.
- Conclusion: The same arousal was experienced as two different emotions depending on the surrounding social cues, supporting the idea that emotion needs both arousal and interpretation.
Cannon and Bard later argued, partly from this same evidence, that bodily arousal and conscious feeling are separate, parallel outputs rather than one causing the other. Schachter and Singer’s version won out because it explained something Cannon-Bard could not.
Why did the identical arousal feel like joy in one situation and anger in another? Interpretation was the missing piece.
Together, these experiments trace an escalating argument about how much thinking is needed to turn a hormone into a feeling. James and Lange treated the bodily state as if it already was the emotion. Cannon and Bard showed that the same generic arousal fits many different emotions, or none.
Schachter and Singer supplied the missing piece: a cognitive label.
Critical Evaluation of Adrenaline Research
Adrenaline-injection studies changed psychology, but they come with real limits.
- Powerful but Constrained: A known dose of adrenaline gave researchers rare experimental control, but it meant deceiving participants about what they were actually given.
- No Single Winner: James-Lange, Cannon-Bard and Schachter-Singer each explain something the others miss, and no one theory has full consensus today.
- Animal-to-Human Gap: The memory mechanism was first shown in rats before being confirmed in humans, though moving from lab mechanism to real treatment remains a harder step.
Contemporary Research
A 2018 meta-analysis tested this assumption directly. Siegel and colleagues (2018) pooled 202 published studies that measured heart rate, skin conductance and similar autonomic responses during laboratory-induced emotions.
They then used pattern-classification analysis to test whether each emotion has its own reliable physiological “fingerprint.” The results were clear.
Most measures rose slightly across every emotion, but the exact pattern of change did not reliably tell one emotion apart from another. Variation within a single emotion category was often just as large as the variation between categories.
The finding does not overturn adrenaline’s basic role in arousal.
It does suggest that a racing heart carries less information about which emotion someone feels than classic theories assumed.
A second, cautionary example comes from work testing whether the same adrenaline-memory mechanism could treat trauma. A 2022 meta-analysis by Pigeon and colleagues pooled 26 studies and reported that propranolol, given while a traumatic memory was being recalled, reduced later emotional reactivity to it.
The result looked promising.
A follow-up correction later that year restricted the analysis to the highest-quality trials and added previously unpublished data. It found propranolol was not actually better than a placebo for trauma symptoms once these adjustments were made. The optimism did not last.
Because arousal varies so much between people, promising future work looks at individual differences in body awareness. People who are especially good at noticing their own bodily signals may show a tighter link between adrenaline and the emotion they end up feeling.
The underlying biology remains well supported. Whether that mechanism can reliably be turned into a treatment is still an open question.

