Neurotransmitters are chemical messengers that play a vital role in how your brain and body communicate.
They affect everything from your mood and memory to your heartbeat and breathing.

What Are Neurotransmitters?
Neurotransmitters are chemicals that carry messages between nerve cells, also called neurons.
When a signal travels through one neuron, it reaches the end of the cell and triggers the release of neurotransmitters.
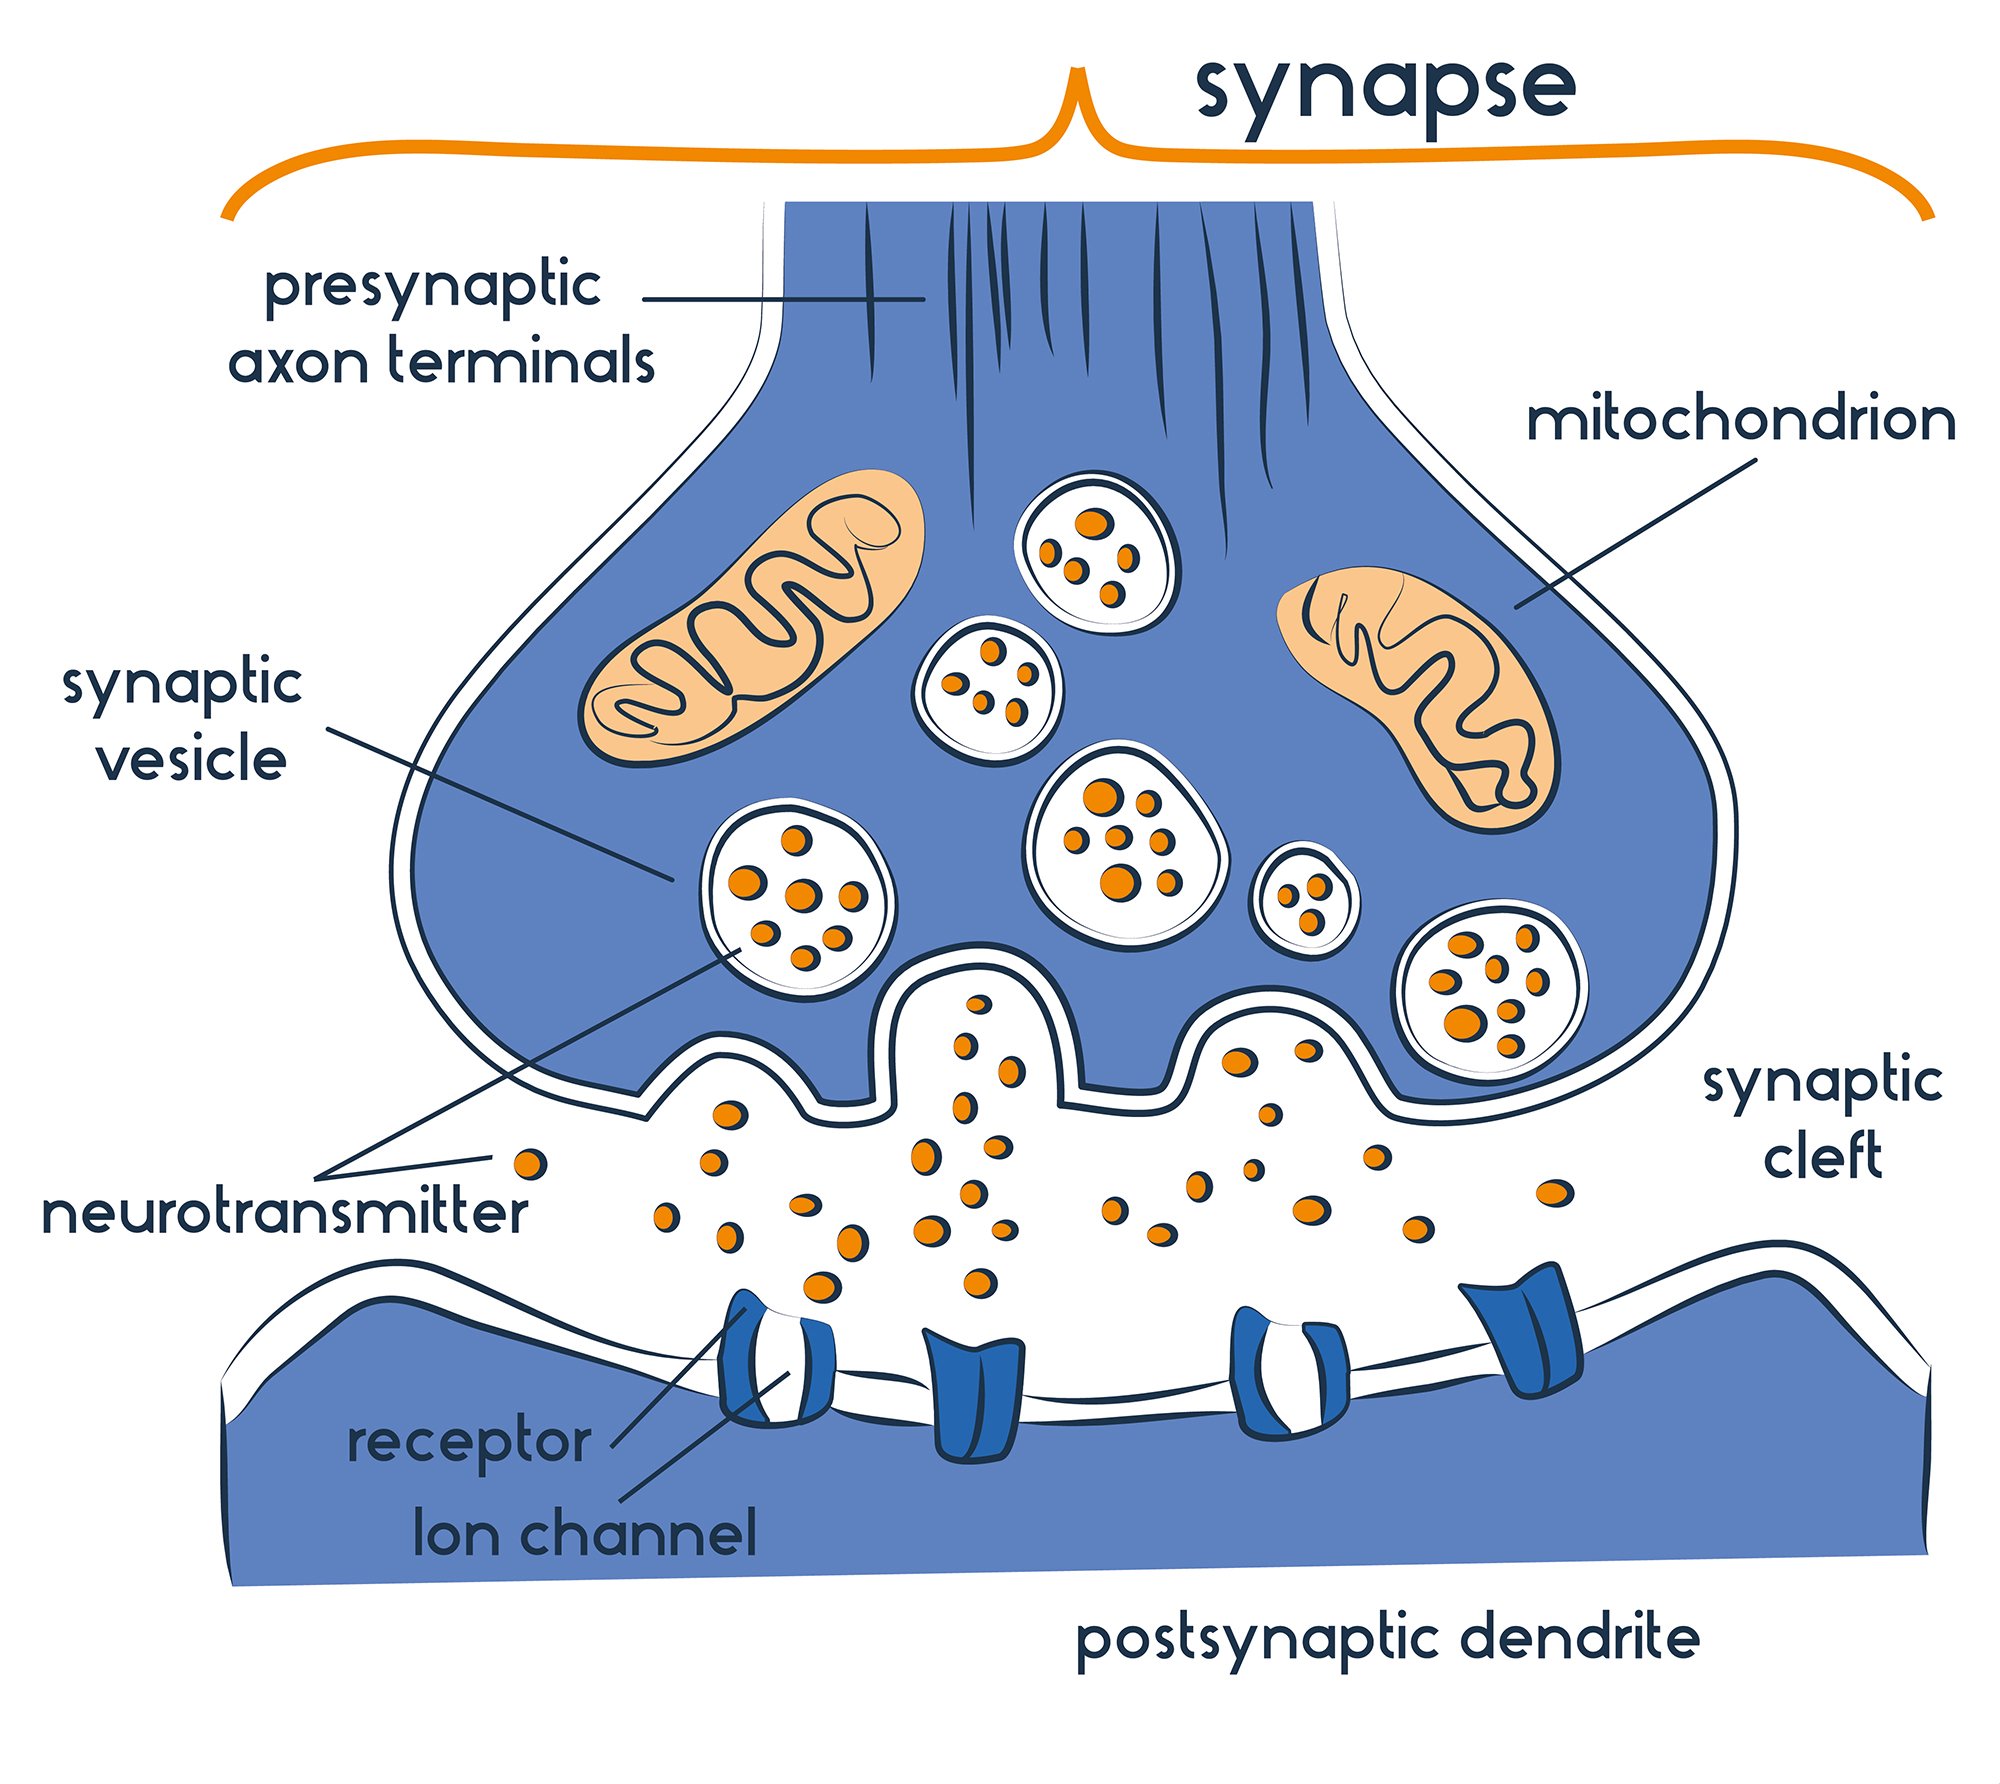
These chemicals cross a tiny gap called the synapse and bind to receptors on the next neuron, passing the message along.
This process, called neurotransmission, helps control countless functions in your brain and body, including:
- Emotions and mood
- Sleep and alertness
- Learning and memory
- Pain and pleasure
- Breathing and heart rate
How Neurotransmitters Work
Neurotransmitters function through a highly coordinated, multi-step process known as synaptic transmission.
Synaptic transmission is how an electrical impulse (action potential) passes from one neuron to another using chemical messengers (neurotransmitters). It crosses the synaptic cleft, the tiny gap between the two neurons, to do so.
This step is essential.
The mechanism by which neurotransmitters work can be broken down into five primary stages:
Below is a simple breakdown of how neurotransmitters work:
- Signal sent: An electrical impulse (called an action potential) travels down the presynaptic neuron until it reaches the end (the presynaptic knob).
- Vesicles move and release: The electrical signal causes synaptic vesicles to move toward the edge of the cell, where they undergo exocytosis: fusing with the presynaptic membrane and releasing the neurotransmitter chemicals into the gap.
- Diffusion across the cleft: The neurotransmitter molecules diffuse across the narrow synaptic cleft. This is the slow part of the process because chemical diffusion is much slower than an electrical impulse.
- Lock-and-key binding: The neurotransmitters attach to specific receptors on the postsynaptic membrane. Because proteins have unique shapes, the neurotransmitter fits into the receptor like a key into a lock (complementary shapes).
- New Signal is Triggered: This binding causes channels in the postsynaptic membrane to open, allowing charged particles (ions) to flow in. This creates an electrical change. If this change is big enough, it triggers a brand-new action potential in the postsynaptic neuron.
Recycling (The Clean-up)
To stop the signal from firing forever, enzymes in the gap quickly break down the neurotransmitter (a process called reuptake).
The broken-down pieces are taken back up into the presynaptic neuron to be remade and repackaged into vesicles for the next signal.
Types of Neurotransmitters
Neurophysiologists categorize neurotransmitters into three major functional types based on their specific postsynaptic actions.
- Excitatory Neurotransmitters: These depolarize the postsynaptic membrane, producing an excitatory postsynaptic potential (EPSP) that brings the receiving cell closer to firing.
- Inhibitory Neurotransmitters: These hyperpolarize the receiving cell, producing an inhibitory postsynaptic potential (IPSP) that acts as a functional brake on firing.
- Modulatory Neurotransmitters: Rather than acting on single synapses, these neuromodulators fine-tune the overall responsiveness of numerous surrounding neurons at once.
While excitatory signals are necessary for propagating information, thoughts, and motor commands throughout the brain and body, inhibitory neurotransmitters are equally vital for maintaining a healthy balance.
Inhibition controls the spread of excitation through the highly interconnected nervous system, ensuring that neural activity remains channeled in appropriate circuits.
If inhibitory functions are impaired or excitation becomes excessive, the brain can enter a turbulent, hyperexcitable state, which is the underlying cause of epileptic seizures.
Common Neurotransmitters
Below are some examples of common neurotransmitters and what they do:

Serotonin (Modulatory)
- Regulates mood, sleep, appetite, and digestion
- Low levels linked to depression, anxiety, and insomnia
- Found in the brain and gut
Serotonin regulates a diverse array of homeostatic functions, including mood, sleep architecture, and appetite. Sleep architecture refers to the structural pattern of sleep cycles.
Although active in the brain, ninety percent of this chemical resides in the gastrointestinal tract.
Gastrointestinal tract is the stomach and intestines.
The popular “chemical imbalance” idea, that low serotonin alone causes depression, has not held up under scrutiny. A major 2022 systematic review pooling the best available evidence found no consistent link between serotonin levels and depression (Moncrieff et al., 2022).
Dopamine (Modulatory)
- Involved in pleasure, motivation, movement, and learning
- High levels linked to addiction and impulsivity
- Low levels linked to depression and Parkinson’s disease
Dopamine drives the brain’s mesolimbic reward pathway, reinforcing pleasurable activities and motivation. Mesolimbic reward pathway is the brain circuit that controls responses to pleasure.
It also coordinates smooth voluntary motor movements through the basal ganglia. Basal ganglia are deep brain structures involved in motor control.
Degeneration of dopamine-producing cells causes Parkinson’s disease, while overactivity contributes to schizophrenia.
Glutamate (Excitatory)
- Main excitatory neurotransmitter in the brain
- Crucial for learning and memory
- Too much can lead to neuron damage (e.g., in stroke or Alzheimer’s)
Glutamate serves as the primary excitatory neurotransmitter within the mammalian central nervous system. It is absolutely crucial for neuroplasticity, learning, and memory formation.
Neuroplasticity is the brain’s ability to reorganize its structure and connections. Excessive glutamate accumulation causes excitotoxicity, which destroys healthy brain cells.
Excitotoxicity is the pathological process where overstimulated nerve cells suffer damage or death. This destructive process occurs during acute strokes and neurodegenerative diseases.
GABA (Gamma-Aminobutyric Acid) (Inhibitory)
- Main calming neurotransmitter
- Helps regulate anxiety, motor control, and sleep
- Low levels linked to anxiety, seizures, and mood disorders
Gamma-aminobutyric acid operates as the principal inhibitory neurotransmitter in the brain.
It dampens central nervous system activity, effectively inducing relaxation and reducing anxiety.
Abnormally low levels of this chemical correlate with epilepsy, insomnia, and chronic mood disorders.
GABA has several other effects too.
Many sedative and anti-anxiety medications, including benzodiazepines and barbiturates, work by boosting GABA’s calming effect. A related inhibitory chemical, glycine, performs the same braking role in the spinal cord and brainstem.
Degeneration of GABA-releasing cells in the brain’s striatum also contributes to the involuntary movements seen in Huntington’s disease.
Norepinephrine (Noradrenaline) (Excitatory)
- Triggers alertness, focus, and stress response
- Involved in the “fight-or-flight” reaction
- Imbalances linked to depression, anxiety, and attention difficulties
Epinephrine (Adrenaline) (Excitatory)
- Similar to norepinephrine, but more hormone-like
- Heightens alertness and prepares the body for action
- Associated with high blood pressure and stress
Epinephrine, better known as adrenaline, functions primarily as a hormone: a chemical messenger released into the bloodstream that acts throughout the body. It also acts as a neurotransmitter in limited pathways.
Adrenal glands release this chemical during high-stress scenarios to maximize physical exertion. Adrenal glands are endocrine organs situated on top of the kidneys.
It rapidly dilates airways and redirects blood flow to major skeletal muscle groups.
Acetylcholine
- Helps control muscles, memory, and attention
- Low levels linked to Alzheimer’s disease
Acetylcholine governs neuromuscular interactions, triggering voluntary and involuntary muscle contractions.
Neuromuscular interactions are the points of communication between nerves and muscles. Within the central nervous system, it critically supports selective attention and memory consolidation.
Severe loss of cholinergic neurons serves as a pathological hallmark of Alzheimer’s disease. Cholinergic neurons are nerve cells that use acetylcholine to send messages.
Endorphins (Inhibitory)
- Natural painkillers that create feelings of pleasure or euphoria
- Released during exercise, excitement, or injury
Endorphins are the brain’s own opioid peptides, natural chemicals that dampen pain signals and produce feelings of pleasure. They are released during exercise, excitement, pain and stress. This is the biological basis of the “runner’s high”.
Endorphins act on the same receptors as opiate drugs like heroin and morphine. This shared target explains why those drugs so effectively relieve pain and generate reward.
Adenosine (Modulatory)
- Promotes sleep and relaxation
- Blocked by caffeine, which explains why coffee keeps you awake
Adenosine builds up progressively in the brain during waking hours to promote sleep pressure. Sleep pressure is the body’s internal drive to sleep.
It binds to specific receptors to slow down neural activity, preparing the body for rest.
Caffeine effectively blocks these receptor sites, temporarily preventing drowsiness.

Neurotransmitters and Mental Health
Neurochemical imbalances directly influence the etiology of diverse psychiatric disorders.
Etiology means the cause or origin of a disease. A malfunction in synthesis, transmission, or reuptake can alter thought, mood, and behavior.
- Depression: Often associated with low serotonin, dopamine, or norepinephrine
- Anxiety: Linked to reduced GABA and imbalanced serotonin
- Schizophrenia: Involves overactive dopamine signaling
- ADHD: Often tied to low dopamine and norepinephrine levels
Understanding these links helps explain why medications target specific neurotransmitters to ease symptoms.
Critical Evaluation
Neurotransmitter research explains a huge amount about the brain, but the story often gets oversimplified by the time it reaches the public.
Three problems recur whenever a claim jumps from “a drug changes this chemical” to “this chemical causes that behaviour”.
- The Chemical Imbalance Myth: The popular claim that depression is caused by low serotonin has not survived scrutiny; the best pooled evidence finds no consistent link.
- Correlation Is Not Causation: A drug relieving a symptom does not prove a chemical deficiency caused it, any more than aspirin curing a headache proves headaches are an aspirin deficiency.
- One Molecule Rarely Explains Behaviour: Transmitter levels interact with dozens of other systems, so isolating a single “cause” of a complex behaviour is rarely possible.
The Chemical Imbalance Myth
Since the 1990s marketing campaigns for early SSRIs, the idea that depression comes from a serotonin deficiency has become one of the most widely repeated claims in psychology.
It is often presented to patients as an established biological fact.
The reasoning behind it is a shortcut, not a demonstration.
A drug that raises serotonin sometimes eases depression, so it is assumed that a deficiency of serotonin must have caused the depression in the first place.
That inference was never directly tested at scale until recently.
The Contemporary Research below sets out what happened when it finally was tested.
It was a systematic review of the entire evidence base, and a landmark reappraisal of one of modern psychology’s most confidently stated “facts”.
Correlation Is Not Causation
Much of the evidence linking neurotransmitters to disorders runs in one direction only, not both.
A drug that raises or lowers a chemical changes symptoms, so the disorder is assumed to be caused by that chemical being too high or too low.
This reasoning contains a logical gap.
Aspirin relieves a headache, but nobody concludes that headaches are caused by an aspirin deficiency.
In the same way, an SSRI easing depression does not, by itself, prove that low serotonin caused the depression in the first place.
Timing matters too.
Drugs change transmitter levels within minutes, yet the benefits of antidepressants can take weeks to appear.
This points to a slow, downstream process rather than the transmitter level itself doing the work.
One Molecule Rarely Explains Behaviour
A transmitter’s effect always depends on which receptor it binds, which pathway it travels, and how it combines with input from thousands of other synapses firing simultaneously.
Even the excitatory or inhibitory identity of a molecule is set by the receptor, not the chemical itself.
Context matters most.
A neurotransmitter is almost never the only factor shaping a behaviour.
Changing its level artificially never changes just one thing; it produces side effects and knock-on changes throughout an interconnected system.
Much of the human evidence is also correlational. A difference between patients and a control group cannot show which factor caused the other.
Whether a neuron fires at all depends on the summation of everything arriving at once: thousands of excitatory and inhibitory signals added together in real time.
The more defensible reading is a simple one: neurotransmitter systems bias and shape behaviour within networks, rather than dictating it molecule by molecule.
Contemporary Research
Moncrieff et al. (2022) put the chemical-imbalance claim to its most rigorous test yet.
- Aim: To systematically evaluate the whole body of evidence for the claim that depression is caused by lowered serotonin activity or concentration.
- Method: A systematic umbrella review pooling the highest tier of existing evidence, including serotonin metabolite studies, brain-imaging and post-mortem receptor studies, tryptophan-depletion experiments, and large genetic studies of the serotonin-transporter gene.
- Results: No area of research showed a consistent link between low serotonin and depression, and the largest genetic studies found no association between the serotonin-transporter gene and depression.
- Conclusion: The main strands of serotonin research provide no support for the hypothesis that depression is caused by lowered serotonin.
How Medications and Drugs Affect Neurotransmitters
Psychotropic medications and illicit drugs alter human behavior by artificially manipulating synaptic transmission. Psychotropic medications are drugs designed to alter mood, thoughts, or behavior.
These external substances generally operate as either chemical agonists or antagonists.
Agonists mimic or enhance the natural effects of a specific neurotransmitter.
Antagonists bind to receptors to block or impede normal neurochemical signaling.
Medications:
- SSRIs (like Prozac) block the reuptake of serotonin, keeping more in the brain
- Benzodiazepines (like Valium) enhance the calming effect of GABA
- Antipsychotics block dopamine receptors to reduce symptoms of schizophrenia
Illicit drugs:
- Cocaine and ecstasy increase dopamine and serotonin, causing temporary euphoria
- Heroin boosts dopamine but suppresses natural production, leading to addiction
- Marijuana affects dopamine and cannabinoid systems, altering mood and perception
How do common clinical prescriptions exploit these cellular pathways?
Selective Serotonin Reuptake Inhibitors treat depression by explicitly blocking presynaptic reuptake transporters.
This targeted blockade forces serotonin to linger inside the synaptic cleft, amplifying its mood-stabilizing effects. Benzodiazepines treat acute anxiety by enhancing the inhibitory efficiency of GABA receptors.
Conversely, antipsychotic medications function as dopamine antagonists to reduce hallucinations.
Recreational substances manipulate these identical pathways with greater, often destructive, intensity. Cocaine blocks dopamine reuptake completely, producing an immediate rush of artificial euphoria.
Heroin stimulates endogenous opioid receptors directly, suppressing natural endorphin production and driving severe addiction.
Marijuana binds to cannabinoid receptors, subtly altering dopamine release to distort sensory perception.
Can You Boost Neurotransmitters Naturally?
Individuals can support healthy neurotransmitter baseline levels naturally through targeted behavioral habits.
While severe clinical imbalances require medical intervention, daily choices heavily influence neurochemical synthesis.
Regular cardiovascular exercise dramatically boosts the production of dopamine and endorphins.
The effect is modest but real.
Consuming a nutrient-dense, balanced diet provides the essential amino acid precursors required for transmitter synthesis.
For instance, tryptophan from proteins serves as the foundational building block for serotonin production.
Sleep counts too.
Consistent, high-quality sleep regulates the precise daily cycles of serotonin and adenosine.
Meaningful social connection triggers oxytocin and dopamine release, actively dampening biological stress responses.
Finally, deliberate stress-reduction techniques like mindfulness lower elevated cortisol levels.
Cortisol is the primary stress hormone in the human body. Protecting these chemical systems stabilizes long-term cognitive endurance and emotional resilience.
- Exercise regularly (increases dopamine and endorphins)
- Eat a balanced diet (provides building blocks for neurotransmitters)
- Sleep well (regulates serotonin and adenosine)
- Connect socially (boosts oxytocin and dopamine)
- Reduce stress (helps balance cortisol and other chemicals)
Key Takeaways
- Chemical Messengers: Neurotransmitters are chemicals that let neurons communicate, shaping everything from mood to muscle movement.
- Three Types: They act as excitatory, inhibitory, or modulatory depending on how they affect brain activity.
- Key Players: Serotonin, dopamine, and GABA are among the most studied neurotransmitters, shaping mental health and emotional balance.
- Medications & Drugs: Many psychiatric medications and recreational drugs work by altering neurotransmitter activity.
- Healthy Habits Help: Exercise, sleep, and social connection can support neurotransmitter function, though the effect is modest.
- Serotonin Caveat: The idea that low serotonin alone causes depression has not held up under review of the best evidence (Moncrieff et al., 2022).
References
Boto, T., & Tomchik, S. M. (2019). The excitatory, the inhibitory, and the modulatory: mapping chemical neurotransmission in the brain. Neuron, 101 (5), 763-765.
Martin, E. I., Ressler, K. J., Binder, E., & Nemeroff, C. B. (2009). The neurobiology of anxiety disorders: brain imaging, genetics, and psychoneuroendocrinology. The Psychiatric Clinics of North America, 32 (3), 549–575. https://doi.org/10.1016/j.psc.2009.05.004
Moncrieff, J., Cooper, R. E., Stockmann, T., Amendola, S., Hengartner, M. P., & Horowitz, M. A. (2022). The serotonin theory of depression: a systematic umbrella review of the evidence. Molecular Psychiatry, 28 (8), 3243–3256. https://doi.org/10.1038/s41380-022-01661-0
Haam, J., & Yakel, J. L. (2017). Cholinergic modulation of the hippocampal region and memory function. Journal of Neurochemistry, 142, 111-121.
Tabet, N. (2006). Acetylcholinesterase inhibitors for Alzheimer’s disease: anti-inflammatories in acetylcholine clothing! Age and Ageing, 35 (4), 336-338.

