Fear is a natural and primitive emotion that can be experienced by everyone to some degree.
Fear is a basic, emotional response to a perceived threat or danger. It triggers the body’s ‘fight-or-flight‘ response. Heart rate and adrenaline levels rise.
Fear is an essential survival mechanism, helping individuals react to potentially life-threatening situations. It can respond to immediate, tangible threats and more abstract or future concerns. Fear can also be learned through past experiences or observations.
People may experience fear when in situations such as walking home alone at night, facing animals they perceive as dangerous, or when about to skydive out of a plane.
Fear often goes hand in hand with stress and anxiety. Anxiety is the uneasy anticipation of a threat that may or may not arrive.
Fear can overlap with disgust too. In a study of 330 people rating snake pictures, those not afraid of snakes gave high fear scores only to fear-evoking snakes and high disgust scores only to disgust-evoking ones.
For snake-fearful people, the border dissolved. Both kinds of snake scored high on fear and on disgust (Rádlová et al., 2020).

Fear is a normal part of life. However, when it becomes extreme in social situations or towards a particular object, it may indicate a more significant issue.
Professional help and support can make extreme fear easier to manage and overcome.
Key Takeaways
- Definition: Fear is the emotion triggered by a perceived threat. It prepares the body to defend itself and focuses attention on the danger.
- Fear vs Anxiety: Fear responds to a present danger. Anxiety anticipates a possible one, although the two overlap.
- Brain Circuits: The amygdala helps detect threat and trigger the body’s response. Other regions take part too, so it is not the whole story.
- Causes: Fears can be learned through experience, observation, or instruction. Evolution makes some fears, such as fear of snakes, easier to learn.
- Disorders: Fear becomes a disorder when it is persistent, disrupts daily life, and has no better explanation.
- Treatment: Graded exposure and cognitive behavioral therapy are the main treatments. Fear can return afterwards, so treatment aims to build lasting safety learning.
- Verdict: Supported with qualifications – the evidence is solid, but treatment effects are moderate and the causal direction is unproven.
Biochemical Reaction
Fear is a normal response to many situations and comprises two primary reactions: biochemical and emotional.
The biochemical reaction to fear causes our bodies to respond to perceived threats in the environment.
This produces automatic physical reactions such as sweating, increased heart rate, breathlessness, and dilated pupils. These bodily reactions prepare the body to combat the threat or run away from it. Together they form the ‘fight or flight’ response.
In response to a threat, the sympathetic nervous system, part of the autonomic nervous system, is activated by the sudden release of hormones.
The sympathetic nervous system then stimulates the adrenal glands to trigger the release of hormones, resulting in physical reactions. These hormones are:
- Epinephrine (adrenaline): Provides energy to the major muscles so they can respond to a perceived threat.
- Norepinephrine (noradrenaline): Increases alertness, arousal, and attention. Constricts blood vessels to help maintain blood pressure during times of stress.
Fear also produces a behavioral reaction, and fight or flight is only its first step. A review of the defense literature describes a defense cascade of innate responses that unfold as a threat grows (Kozlowska et al., 2015).
Arousal comes first. Fight or flight follows when escape is possible. Freezing is fight or flight put on hold, a state of braced stillness and heightened attention.
When escape fails, the body may fall into tonic or collapsed immobility as a last resort. Humans, unlike animals, often fail to return to their standard mode after the danger has passed, remaining locked into a trauma response (Kozlowska et al., 2015).
Emotional Response
The emotional response to fear, however, is personal. The biology of fear shares some chemical responses with pleasant emotions, such as excitement and happiness. As a result, people can experience fear as either pleasant or unpleasant.
For instance, some people may enjoy riding extreme roller coasters, while others may have a negative reaction and will avoid these at all costs.
A haunted house shows this at work. In a field study of 110 visitors, enjoyment peaked at moderate levels of self-reported fear. It was lower at both low and very high levels (Andersen et al., 2020).
The study was observational. It cannot show that moderate fear causes enjoyment. It does suggest that the same bodily arousal can feel thrilling or dreadful, depending on context and sense of control.
Although the biochemical reaction for fear may be the same, some people will experience the intensity of fearful situations differently than others.
Fear vs Anxiety: A Continuum of Defensive States
Fear and anxiety overlap, but psychologists usually separate them by the nature of the threat. Fear responds to a present, identifiable danger. Anxiety is the anticipatory state that goes with a possible or uncertain threat.
Brain research suggests a continuum of defensive states rather than two sealed boxes. The brain shifts between defensive modes as a threat moves closer (Mobbs et al., 2007).
- Aim: To test whether the human brain shifts between defensive circuits as a threat moves from distant to imminent, as animal models predict.
- Method: Fourteen volunteers played a maze game in a brain scanner while a virtual predator chased them. If it caught them, they received a painful electric shock.
- Results: When the predator was far away, activity was greatest in the ventromedial prefrontal cortex. As it came closer, activity shifted to the periaqueductal gray, a midbrain region that controls reflexive defensive behavior.
- Conclusion: Humans appear to switch from a planning-based defensive mode when danger is distant to a reflexive, bodily mode when it is close.
Distant threat is the territory of worry and planning, which is how anxiety is usually described. Close threat is fear’s territory. It is automatic and bodily.
With only 14 participants and a mild shock, the study cannot show that the same circuits drive terror in real life or in phobias. It nevertheless gave the first direct human support for a continuum model.
Symptoms and diagnosis

People can experience fear differently, but some of the common physical and emotional symptoms are:
- Sweating
- Rapid heart rate
- Nausea
- Dizziness
- Chest pain
- Dry mouth
- Upset stomach
- Chills
- Shortness of breath
- Trembling
- Feeling overwhelmed
- Feeling out of control
- A sense of impending death
- Dread
A diagnosis needs more than a passing scare. The symptoms must be persistent and interfere with some part of normal functioning. They also cannot be better explained by another condition.
If feelings of fear become persistent and excessive, this could be diagnosed as a type of anxiety disorder, depending on the symptoms being experienced.
Common disorders associated with fear include phobias, generalized anxiety disorder, social anxiety disorder, illness anxiety disorder, panic disorder, and post-traumatic stress disorder (PTSD). Illness anxiety disorder is a persistent, excessive fear of having a serious illness.
Is fear useful?
In many situations, fear is normal and healthy. It keeps us from entering harmful situations and helps us decide when to get out of them.
How Fear Protects Us
The immediate threat of danger focuses our attention. The physical responses that come with it mobilize us to cope, either by fighting the danger (fight) or by running away from it (flight).
Fear may also help us to react to danger without having to think about it consciously.
For example, if a car is coming towards us, fear can make us jump out of the way and save our lives.
Fear also works as a social signal. Because we recognize fear in ourselves, we can notice it in others and offer compassion and reassurance to help them cope.
The brain’s alarm is deliberately oversensitive, like a smoke alarm.
A system that errs towards false alarms beats one that errs towards misses. Ignoring a real predator costs a life. Fleeing a harmless shadow costs a little energy.
Evolutionary accounts argue that this built-in bias is one reason anxiety disorders exist at all (Öhman & Mineka, 2001). A system that defends too readily will sometimes defend against harmless things.
When Fear Becomes a Problem
In contrast, extreme levels of fear can lead to phobias or other anxiety conditions. A phobia is an intense, persistent, and disproportionate fear of an object, an event, or a situation.
Phobias twist the normal fear response into something difficult or impossible to control. They can be detrimental to people’s lives.
Other anxiety conditions, such as generalized anxiety disorder and social anxiety disorder, involve intense worry or fear of many things and social situations respectively.
The biochemical and emotional response to fear can be so extreme that it harms people’s lives. In anxiety disorders, fear can keep us trapped and prevent us from doing things we want.
Avoidance brings short-term relief. It also locks the fear in place, because the person never gets the chance to learn that the situation is safe.
Disorders That Involve Fear
Phobias
Phobias may be diagnosed when certain situations, events, or objects create a strong, irrational fear. Some symptoms of phobias include:
-
A sensation of uncontrollable anxiety when exposed to the source of the fear.
-
The feeling that the source of the fear needs to be avoided at all costs.
-
Not being able to function properly when exposed to fear.
-
They may acknowledge that the fear is irrational and exaggerated, combined with the inability to control feelings of fear.
- Feeling incapable of coping with the fear.
Different types of phobias can be diagnosed: specific phobias, social phobias, and agoraphobia. Specific phobias are intense, irrational fears of a specific trigger.
Some common specific phobias are spiders and snakes. Social phobia is a profound fear of public humiliation or being judged negatively by others in social situations.
Agoraphobia is an intense fear of situations from which escape might be difficult (or embarrassing). It also covers situations where help may not be available if an unexpected panic episode occurs. This could mean enclosed, open, or crowded spaces.
Specific phobias can usually be linked to an identifiable cause. The person can often avoid the trigger, so they are commonly treated as minor. Older texts call them ‘simple’ phobias, but clinicians no longer use that label as a diagnostic category.
For instance, if someone has a phobia of heights, they are not likely to experience this fear day-to-day, only in situations where they may have to face their fear.
Even so, specific phobias are not trivial. A review of the epidemiology found the following (Eaton et al., 2018).
- Prevalence: Lifetime prevalence ranges from about 3% to 15% worldwide, and fears of heights and animals are the commonest.
- Onset: Often in childhood, although incidence peaks in midlife and old age.
- Persistence: Phobias persist for several years or decades in 10–30% of cases.
- Outcomes: They strongly predict later anxiety, mood and substance-use disorders.
Avoidance reduces day-to-day distress, but it locks the fear in.
Social phobia (also known as social anxiety disorder) and agoraphobia are different. Their triggers are less easy to recognize or avoid, so the fear tends to arise more often than with a specific phobia. Older texts call these ‘complex’ phobias, a label that is also no longer used for diagnosis.
Posttraumatic stress disorder (PTSD)
PTSD is a mental health disorder that can develop after a traumatic event.
The person may have experienced or witnessed a serious accident, military combat, physical or sexual assault, or natural disaster.
Intense fear is a core symptom. Reminders of the trauma can trigger fear or distress. This can happen even when the present situation is not actually dangerous or threatening (Maren et al., 2013).
This fear response is thought to be related to the way the brain processes and encodes memories of the traumatic event. During the event, the brain’s fear response is activated. Stress hormones like cortisol and adrenaline are released.
However, in people with PTSD, the brain’s fear response can become overactive and hyper-vigilant. They may perceive even minor cues in their environment as potential threats.
A veteran who experienced combat trauma might feel intense fear or panic at a car backfiring or fireworks. These sounds can trigger memories of gunfire or explosions. They are reminders, not present dangers.
In essence, the fear response in people with PTSD is triggered by associations between present experiences and past traumatic events, rather than by a real and present danger.
These associations can be so strong that even subtle reminders of the trauma can trigger a full-blown fear response, leading to symptoms like panic attacks, hypervigilance, and avoidance behaviors.
Generalized anxiety disorder (GAD)
Those who experience GAD typically have persistent and excessive worries about everyday life and worry about multiple things. They may be fearful about their health, finances, safety, and relationships, etc. to the point where it can become exhausting.
People with GAD tend to experience the physical symptoms associated with fear but more often and for more reasons.
GAD is not tied to a single cue. Unlike a phobia, it involves worry that recruits the fear response again and again, across many areas of daily life.
Panic disorder
Panic disorder is characterized as fear and worries of the panic attacks experienced recurrently, which are sudden and intense feelings of terror.
These feelings could sometimes occur without warning and are associated with physical symptoms such as chest pain, shortness of breath, fast heart rate, and trembling.
Panic attacks could become very intense that impairs the individual functioning during the episode.
What Causes fear?
Specific phobias usually develop in childhood and, in some cases, can be pinpointed to an exact moment.
An early traumatic experience is one route. A specific phobia can follow a frightening encounter with the feared object, event, or situation. A childhood bike fall can cause a phobia of bicycles.
Phobias that start in childhood could also be caused by witnessing the phobia of a family member and developing the same phobia. For instance, if a parent has a phobia of spiders, the child may also learn to have a phobia of spiders.
Fears can also arise without direct experience. Research points to several other routes.
- Information: Negative or positive information about novel animals had dramatic, opposite effects on children’s self-reported fear and avoidance (Field & Lawson, 2003).
- Genes: Close relatives of people with panic disorder, generalized anxiety disorder, phobias, or obsessive-compulsive disorder have four to six times the odds of the same disorder (Hettema et al., 2001).
- Temperament: Behavioral inhibition, a tendency to withdraw from the unfamiliar, is partly inherited. Most restrained 2-year-olds were still socially avoidant at age 7 (Kagan et al., 1988).
- No learning event: Fears of heights and water can arise in normal development without a frightening experience (Poulton & Menzies, 2002).
The Kagan groups were chosen for extremes, so this shows continuity of temperament, not that every shy child develops an anxiety disorder. Heritability was about 0.43 for panic disorder and 0.32 for generalized anxiety disorder (Hettema et al., 2001).
Evolutionary theory of fear
Seligman (1971) applied his preparedness hypothesis theory to explain why humans fear. The preparedness hypothesis is the belief that humans tend to fear things that were a source of danger to our ancestors.
Seligman proposed that the fears of individuals diagnosed with phobias reflect the evolutionary prepared learning to fear events and situations that have provided survival threats.
He argued these threats would be from an evolutionary rather than a contemporary perspective.
This can explain why phobias such as threatening animals, heights, closed spaces, and social evaluations are very common and appear to be innate fears.
Contemporary fears such as bicycles, broken electrical equipment, and guns are less common as these would not have been survival threats to our ancestors.
The preparedness hypothesis suggests that humans are biologically predisposed to learn certain fears. It does not claim they are present at birth.
Experiments support this. Scientists found it easier to train humans to fear snakes and spiders than friendly dogs or pillows, for instance. Such learned fears also persist longer (Öhman & Mineka, 2001).
Infant research adds an important qualification. Babies do not appear to be born afraid of snakes, but they learn the association quickly (DeLoache & LoBue, 2009).
- Aim: To test whether infants fear snakes spontaneously, as innate fear predicts, or learn to associate snakes with fear, as preparedness predicts.
- Method: Infants watched films or photographs of snakes and other animals. Some also heard a frightened or a happy human voice, and researchers measured looking time.
- Results: Nine- to 10-month-olds showed no special reaction to snake films. Infants aged 7 to 18 months looked longer at snakes accompanied by a frightened voice than a happy one.
- Conclusion: Infants are not born afraid of snakes, but they quickly and selectively associate snakes with fear.
The result is more modest than the popular claim that infants fear snakes. Looking time shows attention and association, not felt fear. It supports a learning bias, not ready-made fear.
Fear conditioning
Pavlovian fear conditioning is a state of fear or anxiety demonstrated in animals using classical conditioning. A threatening stimulus is repeatedly paired with a neutral one.
In experiments, the researchers would pair a neutral stimulus with an unpleasant stimulus – such as a loud noise or shock. After repeated pairing of these two stimuli, the neutral stimulus on its own would eventually elicit a state of fear.
This is another way intense fear can arise. In animals, such learned fear is essential for survival.
This fear conditioning could be learned in humans who suffer from posttraumatic stress disorder (PTSD).
Post-traumatic stress disorder (PTSD) is an anxiety disorder caused by very distressing, frightening, or traumatic events. When triggered, people relive them through intense or prolonged distress.
This includes marked physiological reactions such as exaggerated and unrelenting unconditioned responses to stimuli (e.g., crowds, flashes of light, or sounds) associated with trauma (e.g., death or injury).
PTSD can bring about feelings of intense fear when something specifically triggers it. Most of the time, the trigger will not be an actual threat to survival but is a conditioned stimulus for the individual.
This means they can experience intense feelings of fear at times when it is not appropriate.
A conditioned fear is not permanent. If the cue is presented repeatedly without the unpleasant event, the fear response weakens. This is called extinction, and exposure therapy is built on it.
Extinction does not erase the original learning. It creates a new, inhibitory memory that the cue is now safe, and that new memory depends heavily on context (Bouton, 2004).
Because the original fear memory survives, fear can return. It can come back with the passage of time (spontaneous recovery), a change of context (renewal), or a fresh unpleasant event (reinstatement).
Fear can also spread. Fear generalization is the spread of fear from a feared stimulus to similar ones. It is adaptive up to a point, since a bite from one dog should make a child wary of similar dogs.
A systematic review concluded that excessive generalization is a defining feature of anxiety disorders (Dymond et al., 2015).
The brain’s fear response
The amygdala is central to fear. It is a collection of nuclei in the limbic system that detects threat and triggers the body’s response.
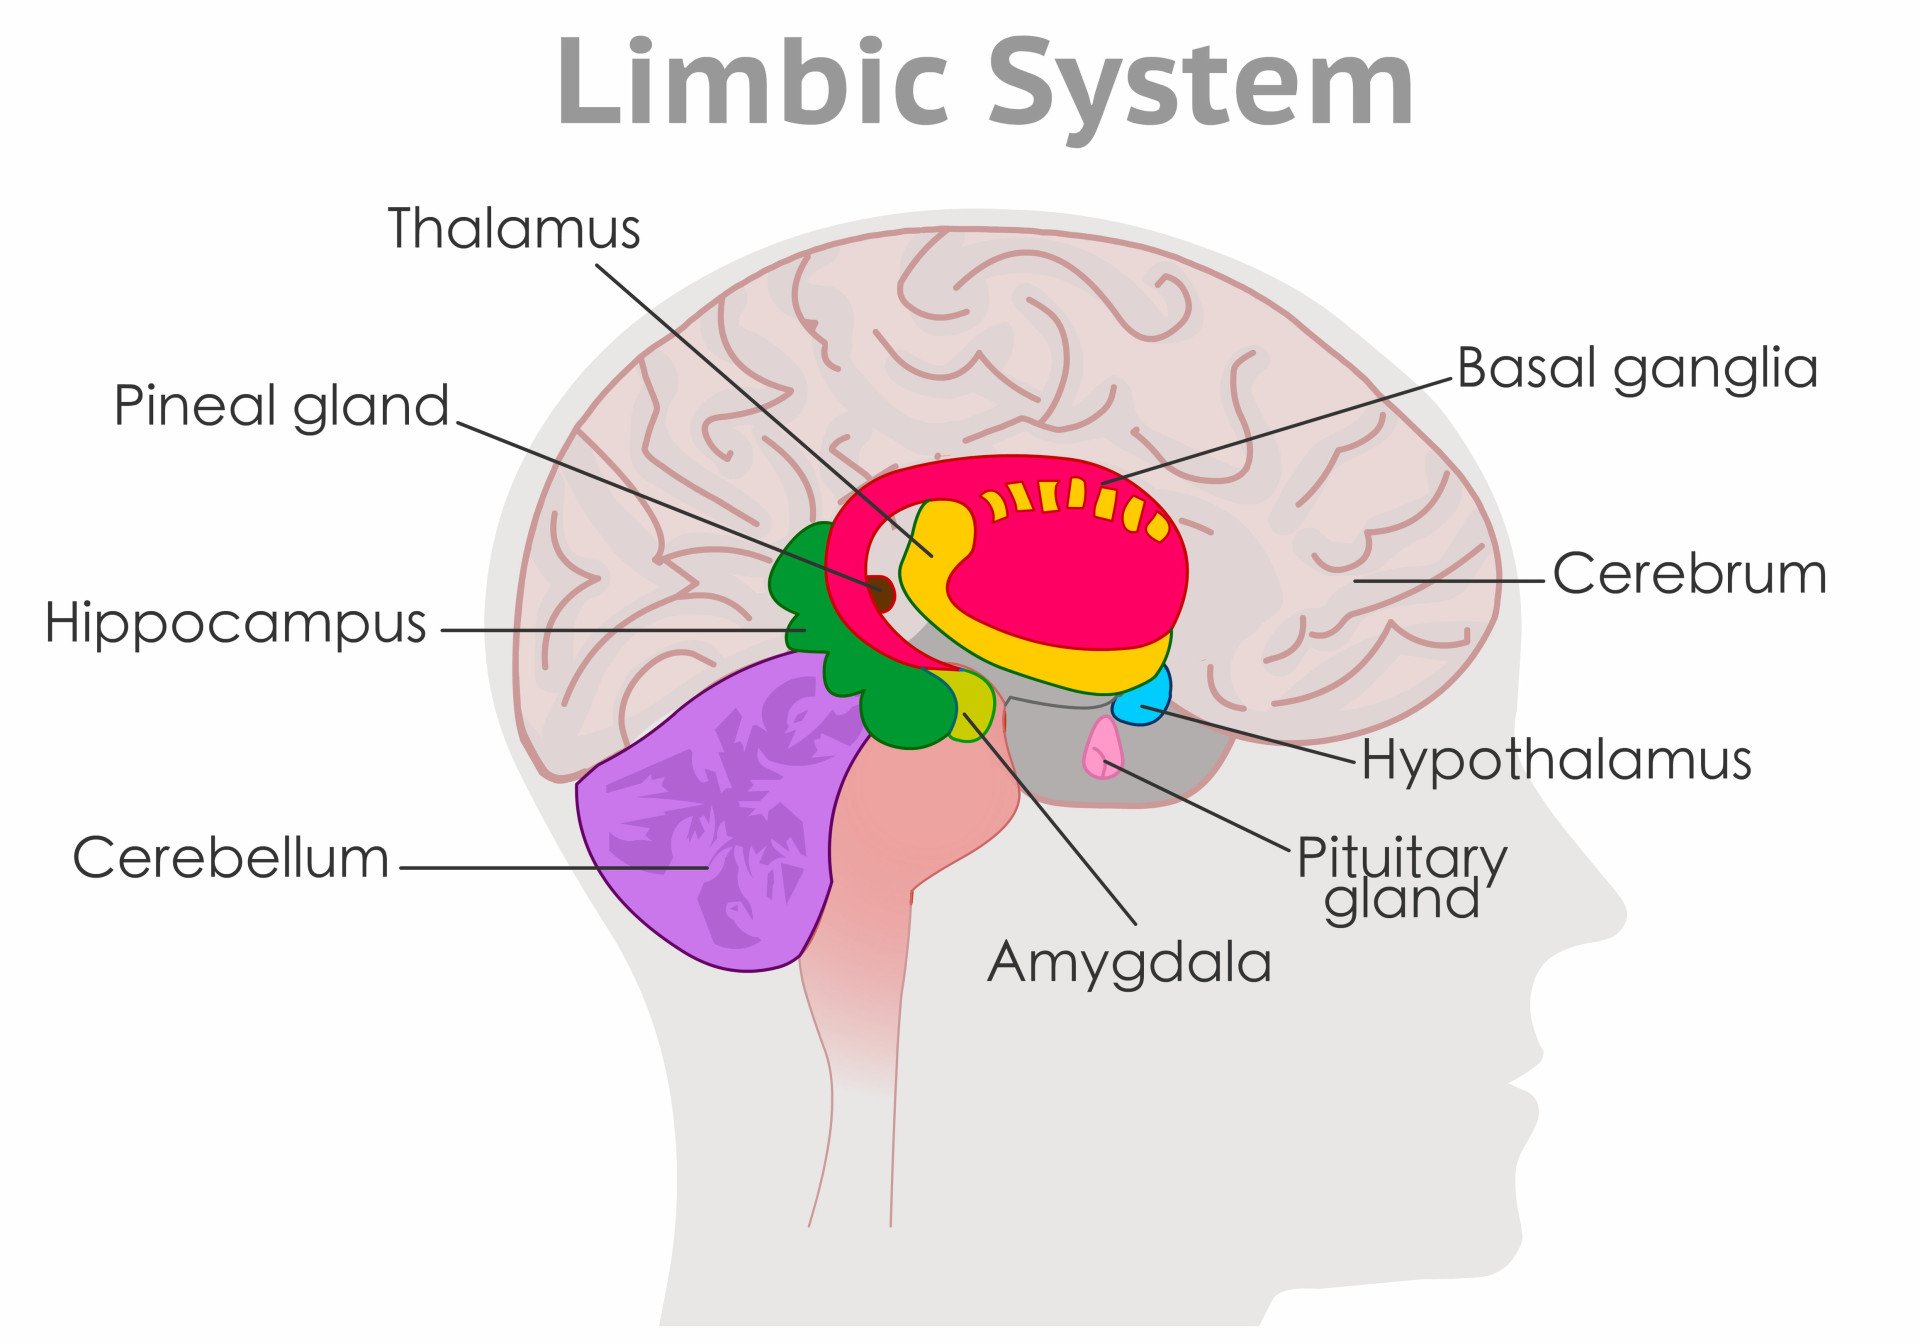
Some main nuclei in the amygdala are the lateral, basal, central lateral, and central medial nuclei. The lateral nucleus is the main input. It receives sensory information from the thalamus and the brain’s cortex.
The central medial nucleus is the main output. It projects to the paraventricular nucleus of the hypothalamus, which triggers the release of the stress hormone cortisol.
It also projects to the lateral hypothalamus to stimulate the autonomic nervous system, which results in the physiological symptoms associated with the fight or flight, or fear, response.
The amygdala is also central to fear conditioning.
In rats, an unconditioned stimulus, such as a shock, is picked up by the spinal cord. The spinal cord signals the thalamus and the cortex, and both project to the lateral nucleus of the amygdala.
The synaptic inputs from the unconditioned stimulus are strong enough to excite the lateral amygdala neurons. They activate the neurons in the central medial nucleus. A fear response follows.
Music, a neutral stimulus, also reaches the thalamus and cortex.
Still, its inputs are not strong enough on their own to excite the lateral amygdala neurons, so the central amygdala neurons remain unstimulated. There is no fear response.
However, if the neutral stimulus (music) is paired with the unconditioned stimulus (shock), neurons can encode both simultaneously.
This can strengthen the synapse between incoming neurons carrying information about the neutral stimulus and the lateral amygdala neurons.
Eventually, this synapse is strengthened enough to allow them to stimulate the lateral amygdala neurons on their own without the unconditioned stimulus. The lateral nucleus then excites the central medial nucleus. The fear response follows.
The hippocampus, which plays a role in storing episodic memories, can also interact with the amygdala and be involved in fear.
The neurons from the hippocampus can project to the basal nucleus of the amygdala, which can then stimulate the central medial nucleus.
The hippocampus therefore lets contextual memories respond to fear. This could be why fearful memories are so strong.
Is the Amygdala Necessary for Fear?
The idea that the amygdala is the brain’s fear center is a simplification. The best-known patient, S.M., whose amygdalae were destroyed by Urbach-Wiethe disease, shows little fear of dangers that frighten most people. Yet fear is not a single thing.
A 2013 study asked what happens when the threat comes from inside the body (Feinstein et al., 2013).
- Aim: To test whether people without a functioning amygdala still feel fear when the threat is bodily, using inhaled carbon dioxide to provoke panic.
- Method: Three patients with bilateral amygdala damage, including twin sisters, inhaled air containing 35% carbon dioxide. Twelve matched comparison adults did the same.
- Results: All three patients reported fear, and all had a panic attack on the first trial. Only 3 of the 12 comparison participants panicked.
- Conclusion: The amygdala is not required for fear and panic triggered by internal bodily signals. Different kinds of fear may rely on different routes.
Three patients, two of them twins, is a very small sample, and carbon dioxide is a bodily stimulus.
The results do not show that the amygdala is unnecessary for fear of a snake or a social threat. They do show that fear is not one structure’s job.
Two systems may be at work. LeDoux’s research on conditioned fear in rats proposed a quick, crude route to the amygdala direct from the thalamus.
A slower, detailed route runs via the sensory cortex.
In the two-system view, one system controls the behavioral and physiological responses to threat and is shared across mammals. A second involves cortical circuits that give rise to the conscious feelings of fear that humans report (LeDoux, 2014; LeDoux & Pine, 2016).
Another review agrees that there is no consensus on what fear is (Adolphs, 2013).
What does the research say?
There are suggested to be sex differences in amygdala activation.
One fMRI study compared the sexes. Functional magnetic resonance imaging (fMRI) is a brain imaging technique. Happy facial expressions produced greater activation in the right amygdala for males but not for females.
Both males and females showed greater left amygdala activation for fearful faces (Killgore & Yurgelun-Todd, 2001). This supports a greater left-sided role in negative affect.
Trauma may also reshape fear circuits. Other researchers have found that the volumes of brain regions involved in fear may differ for those who have experienced more trauma.
Using MRI on children who experienced trauma, research found reduced hippocampal and increased amygdala volume with increasing levels of trauma exposure. Higher exposure to violence also increased amygdala activation.
Finally, increased functional connectivity between the amygdala and the brain stem was associated with higher levels of exposure to violence (van Rooij et al., 2020).
The findings are correlational. The study scanned 69 children aged 8 to 14 once, so it cannot show whether trauma changed the brain or whether pre-existing differences raised the risk of exposure.
Fear also captures attention (Öhman, 2009). In a 2025 online experiment, 30 participants who were highly fearful of spiders searched for a target shape. They were slower when a spider appeared as a distractor than when a leaf or butterfly did (Theeuwes & van Moorselaar, 2025).
They could still learn to suppress spiders. A comparison group of 24 participants who were not afraid of spiders showed no capture.
The study was online, unregistered and small. It is a suggestive demonstration, not a proven treatment.
Treatment for Fear: How to Overcome and Manage It
Treatment for disorders associated with fear varies depending on the type of disorder and the symptoms experienced.
Often, phobias treatments can be used for disorders associated with extreme fear. Some of these treatment options will be explained below:
Graded Exposure Therapy
A common therapy for people with extreme fears is graded exposure therapy. This involves gradually leading the individual through exposure situations commonly used for those with specific phobias.
The aim is to expose the individual to the feared object or situation in small steps. They move up a level once they feel comfortable. Eventually, they can face their fear.
For instance, if someone has a phobia of spiders, the steps may go as follows:
-
Talking to the therapist about spiders
-
See pictures of spiders – this could start off as drawings and gradually get more realistic until the patient can manage to view a photo of one.
-
The patient may be encouraged to watch video footage of a spider
-
The patient could handle a toy spider
-
Eventually, the patient should get to a stage where they can face a real spider.
The steps taken to complete the therapy may take a long time, depending on how strong the fear is and the individual’s capability to cope.
Once the individual feels like they can manage their fear at each step, they can move on to the next step until they gradually become desensitized to their fear.
Why does exposure therapy work? The leading explanation is inhibitory learning.
Exposure builds a new, competing memory that the feared cue is now safe, rather than erasing the old fear memory (Craske et al., 2014).
Treatment should therefore aim to maximize that new learning. Strategies include showing clearly that the feared outcome does not happen, practicing in several contexts, varying the exercises, and removing safety signals (Craske et al., 2014).
Exposure can feel intensely physical. As one participant in a qualitative study of 30 veterans recalled, in the first exposures “my body reacted quite powerfully”, with shaking legs and a feeling of suffocation. As therapy progressed, the exposures became easier. The shaking stopped (Harwood-Gross et al., 2025).
Others described an emotional rollercoaster, with days of feeling crushed after sessions. This is one study of one clinical group, so it illustrates experience rather than showing what works.
Cognitive behavioral therapy (CBT)
CBT can help tackle negative and unrealistic thoughts regarding intense fear.
The individual can work with the therapist to work through their fears, form more realistic thoughts, challenge their fearful thoughts, and learn coping strategies.
CBT allows people to learn different ways of understanding and reacting to the source of their fear and can help teach a person to manage their feelings and thoughts.
Medication
Some medications can be useful to aid with the symptoms of extreme fear.
Medication should only be used as a short-term treatment for phobias because the medication can become part of safety behaviors for the individual to rely on when facing fearful situations.
This can stop the person from fully exposing themselves to the fear and learning that the situation is safe. The research is mixed, however. The idea that safety behaviors are always harmful has recently been challenged (Blakey & Abramowitz, 2016).
Below are some medications that can be used for phobias:
Beta-blockers – these reduce the physical symptoms of fear by lowering stress on the heart and blood vessels. They block the receptors on which epinephrine and norepinephrine act, rather than stopping the release of those hormones. Routine use for anxiety disorders is not well supported.
However, these can come with some side effects: insomnia, fatigue, and upset stomach.
Benzodiazepines – tranquilizers are a type of this medication. This helps reduce anxiety symptoms and has a sedative effect on the individual, meaning they slow down the body and brain function.
These medications can be taken when required. They have been known to cause a dependency. Withdrawal effects could be life-threatening.
Selective serotonin reuptake inhibitors (SSRIs) – these medications are a type of antidepressant and are commonly prescribed for phobias.
SSRIs affect serotonin levels in the brain and so can produce better moods in individuals. Side effects of these medications include nausea, sleep problems, and headaches.
A different approach targets learning itself. D-cycloserine, a drug that acts on the receptors involved in new learning, was tested as an add-on to exposure therapy.
A meta-analysis of individual participant data from 21 randomized trials found only a small improvement by the end of treatment. It was not significant at follow-up (Mataix-Cols et al., 2017).
Other coping methods
Relaxation techniques can be used to help people calm down. These can include meditation and breath retraining exercises to help treat the symptoms of fear, especially when faced with a fearful situation.
Progressive muscle relaxation works by tensing a muscle group for a few seconds, then releasing it. The release should decrease any built-up tension.
Working through all the muscle groups this way can encourage the whole body to feel relaxed and reduce the fear response. Likewise, yoga can reduce the fear response too.
Combining physical postures, breathing exercises, and meditation in yoga can all help people improve their management of anxiety disorders and fear.
Aerobic exercise helps too. A meta-analysis of six randomized controlled trials with 262 adults who had anxiety or stress-related disorders found a moderate benefit of exercise over control conditions. With so few and small trials, the estimate is imprecise (Stubbs et al., 2017).
Relaxation is a coping aid, not a substitute for exposure. Used to avoid the feared situation, it risks becoming a safety behavior.
Helping Children Manage Fear
Parents are often the main route by which children learn to approach or avoid something frightening. Parenting is also changeable. A laboratory trial tested this directly (Ewing et al., 2020).
- Aim: To test whether a short video could change how parents help a fearful child approach a feared animal.
- Method: Seventy-two parents helped a child aged 5 to 9 approach a feared animal in 13 steps. They were then randomly assigned to watch a 10-minute “Managing Fear” video or a control video, and repeated the task.
- Results: After the video, avoidance parenting fell and children took more steps towards the second animal. The fall in avoidance parenting helped explain this effect.
- Conclusion: A brief video can shift how parents behave around a child’s fear. Reducing avoidance-encouraging behavior appears to matter more than increasing encouragement.
The effect was small. Children’s mean steps rose from about 11.8 to 12.0 on a 13-step scale. It was only a proof of principle, tested in a single laboratory session.
Participants were mostly mothers. Almost all were White British or White other.
Evidence-informed advice is to give confident, accurate information, model approach, and avoid reinforcing avoidance (Ewing et al., 2020; Field & Lawson, 2003).
Evidence Check: Does Fear Learning Research Hold Up?
Verdict: Supported with qualifications.
Two claims carry much of the weight in this article. Fear learning works differently in anxiety-related disorders, and exposure-based therapy reduces fear-related symptoms. The best evidence supports both, with caveats.
Both rest on comparisons of patients with healthy controls and on moderate effects against placebo. The proposed brain-level “two-system” account of fear has not been tested in humans in a way that would settle it.
In short, a current account should say the following.
- Altered Learning: On average, people with anxiety-related disorders respond more strongly to safety signals and extinguish fear more slowly, while still telling danger from safety. Whether this precedes or follows the disorder is not yet established.
- Exposure-Based CBT: It is moderately effective against placebo, with smaller benefits in PTSD, social anxiety and panic. Fear may return, so treatment aims to build durable, varied safety learning.
Anxiety-Related Disorders Involve Altered Fear and Safety Learning
Level of evidence: Meta-analysis or systematic review; partly replicated.
The claim is simple to state. People with anxiety-related disorders respond more strongly to safety signals, and extinguish conditioned fear more slowly, than healthy people.
Duits et al. (2015) pooled 44 studies (963 patients, 1,222 controls). Patients showed stronger responses to conditioned safety cues during acquisition. During extinction, they responded more strongly to the danger cue, which indicates delayed or reduced extinction.
Kausche et al. (2025) updated the analysis to 77 studies (2,052 patients and 3,258 controls). They found the same direction: amplified responses to safety cues and heightened threat expectancy through extinction and recall. Discrimination between danger and safety cues stayed intact.
A third meta-analysis, restricted to generalization measured by risk ratings, found a small association with pathological anxiety (g = 0.44). Results were inconsistent across disorders (Fraunfelter et al., 2022).
What does this mean? The pattern of fear and safety learning does differ in patients, so the learning account of anxiety is not merely a theory about how phobias begin.
The findings also qualify the older view that patients simply learn fear faster. They respond more to safety cues and extinguish more slowly, while still telling danger from safety.
The effect is real. Whether it is causal is untested.
How far can this be trusted? The 2025 meta-analysis is the most trustworthy piece. It is the largest and the most recent, and it is consistent with an independent 2015 analysis.
Every study, however, compares patients with healthy controls at one point in time, so it cannot say whether altered learning precedes the disorder. The studies also use varied stimuli and measures (Lonsdorf et al., 2017).
Exposure-Based CBT Reduces Fear-Related Symptoms, With Modest Effects
Level of evidence: Meta-analysis or systematic review; partly replicated.
The claim is that cognitive behavioral therapy, with exposure as a central component, reduces fear-related symptoms compared with placebo. The effect is moderate rather than large. Exposure’s gains can also be reversed.
Carpenter et al. (2018) pooled 41 randomized placebo-controlled trials with 2,843 patients across six disorders. They found a moderate effect on the target disorder (Hedges’ g = 0.56). The response-rate odds ratio was 2.97.
Effects were larger for obsessive-compulsive disorder, generalized anxiety disorder and acute stress disorder. They were smaller for PTSD, social anxiety disorder and panic disorder.
Dropout was greater from CBT in PTSD studies.
A review of specific phobias reports that exposure remains the treatment of choice but may be less effective in the long term than previously believed (Eaton et al., 2018).
A narrative review of 39 studies concluded that extinction learning generalizes poorly from similar stimuli to the original feared stimulus (Wong, 2025). That offers a mechanism for the return of fear.
A meta-analysis of individual participant data from 21 randomized trials found that D-cycloserine added only a small improvement after treatment, not significant at follow-up (Mataix-Cols et al., 2017).
What does this mean? Exposure-based CBT is effective but imperfect. It is effective because the effect against placebo is moderate and consistent across disorders.
It is imperfect because many patients do not remit. Effects differ by disorder, and the extinction mechanism it relies on is fragile and context-specific.
The most trustworthy piece is the placebo-controlled CBT meta-analysis, because it uses randomized data from a large pooled sample. Its patients enrolled in trials and completed treatment.
The outcome is symptom change soon after treatment, not remission. The generalization evidence is lower in quality: it is a narrative synthesis of laboratory experiments, so its link to clinical relapse is a hypothesis.
References
Adolphs, R. (2013). The biology of fear. Current Biology, 23(2), R79–R93. https://doi.org/10.1016/j.cub.2012.11.055
Andersen, M. M., Schjoedt, U., Price, H., Rosas, F. E., Scrivner, C., & Clasen, M. (2020). Playing with fear: A field study in recreational horror. Psychological Science, 31(12), 1497–1510. https://doi.org/10.1177/0956797620972116
Blakey, S. M., & Abramowitz, J. S. (2016). The effects of safety behaviors during exposure therapy for anxiety: Critical analysis from an inhibitory learning perspective. Clinical Psychology Review, 49, 1–15. https://doi.org/10.1016/j.cpr.2016.07.002
Bouton, M. E. (2004). Context and behavioral processes in extinction. Learning & Memory, 11(5), 485–494. https://doi.org/10.1101/lm.78804
Carpenter, J. K., Andrews, L. A., Witcraft, S. M., Powers, M. B., Smits, J. A. J., & Hofmann, S. G. (2018). Cognitive behavioral therapy for anxiety and related disorders: A meta-analysis of randomized placebo-controlled trials. Depression and Anxiety, 35(6), 502–514. https://doi.org/10.1002/da.22728
Craske, M. G., Treanor, M., Conway, C. C., Zbozinek, T., & Vervliet, B. (2014). Maximizing exposure therapy: An inhibitory learning approach. Behaviour Research and Therapy, 58, 10–23. https://doi.org/10.1016/j.brat.2014.04.006
DeLoache, J. S., & LoBue, V. (2009). The narrow fellow in the grass: Human infants associate snakes and fear. Developmental Science, 12(1), 201–207. https://doi.org/10.1111/j.1467-7687.2008.00753.x
Duits, P., Cath, D. C., Lissek, S., Hox, J. J., Hamm, A. O., Engelhard, I. M., van den Hout, M. A., & Baas, J. M. P. (2015). Updated meta-analysis of classical fear conditioning in the anxiety disorders. Depression and Anxiety, 32(4), 239–253. https://doi.org/10.1002/da.22353
Dymond, S., Dunsmoor, J. E., Vervliet, B., Roche, B., & Hermans, D. (2015). Fear generalization in humans: Systematic review and implications for anxiety disorder research. Behavior Therapy, 46(5), 561–582. https://doi.org/10.1016/j.beth.2014.10.001
Eaton, W. W., Bienvenu, O. J., & Miloyan, B. (2018). Specific phobias. The Lancet Psychiatry, 5(8), 678–686. https://doi.org/10.1016/S2215-0366(18)30169-X
Ewing, D., Pike, A., Dash, S., Hughes, Z., Thompson, E. J., Hazell, C., Ang, C. M., Kucuk, N., Laine, A., & Cartwright-Hatton, S. (2020). Helping parents to help children overcome fear: The influence of a short video tutorial. British Journal of Clinical Psychology, 59(1), 80–95. https://doi.org/10.1111/bjc.12233
Feinstein, J. S., Buzza, C., Hurlemann, R., Follmer, R. L., Dahdaleh, N. S., Coryell, W. H., Welsh, M. J., Tranel, D., & Wemmie, J. A. (2013). Fear and panic in humans with bilateral amygdala damage. Nature Neuroscience, 16(3), 270–272. https://doi.org/10.1038/nn.3323
Field, A. P., & Lawson, J. (2003). Fear information and the development of fears during childhood: Effects on implicit fear responses and behavioural avoidance. Behaviour Research and Therapy, 41(11), 1277–1293. https://doi.org/10.1016/S0005-7967(03)00034-2
Fraunfelter, L., Gerdes, A. B. M., & Alpers, G. W. (2022). Fear one, fear them all: A systematic review and meta-analysis of fear generalization in pathological anxiety. Neuroscience & Biobehavioral Reviews, 139, 104707. https://doi.org/10.1016/j.neubiorev.2022.104707
Harwood-Gross, A., Elias, S., Lerner, K., Nacasch, N., Lawi, C., Brom, D., & Barak, A. (2025). Veterans’ experiences of somatic experiencing and prolonged exposure therapies for post-traumatic stress disorder: A qualitative analysis. Psychology and Psychotherapy: Theory, Research and Practice, 98(1), 175–192. https://doi.org/10.1111/papt.12570
Hettema, J. M., Neale, M. C., & Kendler, K. S. (2001). A review and meta-analysis of the genetic epidemiology of anxiety disorders. American Journal of Psychiatry, 158(10), 1568–1578. https://doi.org/10.1176/appi.ajp.158.10.1568
Kagan, J., Reznick, J. S., & Snidman, N. (1988). Biological bases of childhood shyness. Science, 240(4849), 167–171. https://doi.org/10.1126/science.3353713
Kausche, F. M., Carsten, H. P., Sobania, K. M., & Riesel, A. (2025). Fear and safety learning in anxiety- and stress-related disorders: An updated meta-analysis. Neuroscience & Biobehavioral Reviews, 169, 105983. https://doi.org/10.1016/j.neubiorev.2024.105983
Killgore, W. D. S., & Yurgelun-Todd, D. A. (2001). Sex differences in amygdala activation during the perception of facial affect. NeuroReport, 12(11), 2543–2547. https://doi.org/10.1097/00001756-200108080-00050
Kozlowska, K., Walker, P., McLean, L., & Carrive, P. (2015). Fear and the defense cascade: Clinical implications and management. Harvard Review of Psychiatry, 23(4), 263–287. https://doi.org/10.1097/HRP.0000000000000065
LeDoux, J. E. (2014). Coming to terms with fear. Proceedings of the National Academy of Sciences, 111(8), 2871–2878. https://doi.org/10.1073/pnas.1400335111
LeDoux, J. E., & Pine, D. S. (2016). Using neuroscience to help understand fear and anxiety: A two-system framework. American Journal of Psychiatry, 173(11), 1083–1093. https://doi.org/10.1176/appi.ajp.2016.16030353
Lonsdorf, T. B., Menz, M. M., Andreatta, M., Fullana, M. A., Golkar, A., Haaker, J., Heitland, I., Hermann, A., Kuhn, M., Kruse, O., Meir Drexler, S., Meulders, A., Nees, F., Pittig, A., Richter, J., Römer, S., Shiban, Y., Schmitz, A., Straube, B., … Merz, C. J. (2017). Don’t fear ‘fear conditioning’: Methodological considerations for the design and analysis of studies on human fear acquisition, extinction, and return of fear. Neuroscience & Biobehavioral Reviews, 77, 247–285. https://doi.org/10.1016/j.neubiorev.2017.02.026
Maren, S., Phan, K. L., & Liberzon, I. (2013). The contextual brain: Implications for fear conditioning, extinction and psychopathology. Nature Reviews Neuroscience, 14(6), 417–428. https://doi.org/10.1038/nrn3492
Mataix-Cols, D., Fernández de la Cruz, L., Monzani, B., Rosenfield, D., Andersson, E., Pérez-Vigil, A., Frumento, P., de Kleine, R. A., Difede, J., Dunlop, B. W., Farrell, L. J., Geller, D., Gerardi, M., Guastella, A. J., Hofmann, S. G., Hendriks, G.-J., Kushner, M. G., Lee, F. S., Lenze, E. J., … Rück, C. (2017). D-cycloserine augmentation of exposure-based cognitive behavior therapy for anxiety, obsessive-compulsive, and posttraumatic stress disorders: A systematic review and meta-analysis of individual participant data. JAMA Psychiatry, 74(5), 501–510. https://doi.org/10.1001/jamapsychiatry.2016.3955
Mobbs, D., Petrovic, P., Marchant, J. L., Hassabis, D., Weiskopf, N., Seymour, B., Dolan, R. J., & Frith, C. D. (2007). When fear is near: Threat imminence elicits prefrontal-periaqueductal gray shifts in humans. Science, 317(5841), 1079–1083. https://doi.org/10.1126/science.1144298
Öhman, A. (2009). Of snakes and faces: An evolutionary perspective on the psychology of fear. Scandinavian Journal of Psychology, 50(6), 543–552. https://doi.org/10.1111/j.1467-9450.2009.00784.x
Öhman, A., & Mineka, S. (2001). Fears, phobias, and preparedness: Toward an evolved module of fear and fear learning. Psychological Review, 108(3), 483–522. https://doi.org/10.1037/0033-295X.108.3.483
Poulton, R., & Menzies, R. G. (2002). Non-associative fear acquisition: A review of the evidence from retrospective and longitudinal research. Behaviour Research and Therapy, 40(2), 127–149. https://doi.org/10.1016/S0005-7967(01)00045-6
Rádlová, S., Polák, J., Janovcová, M., Sedláčková, K., Peléšková, Š., Landová, E., & Frynta, D. (2020). Emotional reaction to fear- and disgust-evoking snakes: Sensitivity and propensity in snake-fearful respondents. Frontiers in Psychology, 11, Article 31. https://doi.org/10.3389/fpsyg.2020.00031
Seligman, M. E. P. (1971). Phobias and preparedness. Behavior Therapy, 2(3), 307–320. https://doi.org/10.1016/S0005-7894(71)80064-3
Steimer, T. (2002). The biology of fear- and anxiety-related behaviors. Dialogues in Clinical Neuroscience, 4(3), 231–249. https://doi.org/10.31887/DCNS.2002.4.3/tsteimer
Stubbs, B., Vancampfort, D., Rosenbaum, S., Firth, J., Cosco, T., Veronese, N., Salum, G. A., & Schuch, F. B. (2017). An examination of the anxiolytic effects of exercise for people with anxiety and stress-related disorders: A meta-analysis. Psychiatry Research, 249, 102–108. https://doi.org/10.1016/j.psychres.2016.12.020
Theeuwes, J., & van Moorselaar, D. (2025). Learning to suppress what I fear. Emotion, 25(3), 782–786. https://doi.org/10.1037/emo0001433
van Rooij, S. J. H., Smith, R. D., Stenson, A. F., Ely, T. D., Yang, X., Tottenham, N., Stevens, J. S., & Jovanovic, T. (2020). Increased activation of the fear neurocircuitry in children exposed to violence. Depression and Anxiety, 37(4), 303–312. https://doi.org/10.1002/da.22994
Wong, A. H. K. (2025). Spreading the reduction of fear: A narrative review of generalization of extinction learning in human fear conditioning. Clinical Psychology Review, 118, Article 102580. https://doi.org/10.1016/j.cpr.2025.102580
Further Reading
- Kozlowska, K., Walker, P., McLean, L., & Carrive, P. (2015). Fear and the defense cascade: clinical implications and management. Harvard review of psychiatry.
- Adolphs, R. (2013). The biology of fear. Current biology, 23(2), R79-R93.
- LeDoux, J. E. (2014). Coming to terms with fear. Proceedings of the National Academy of Sciences, 111(8), 2871-2878.
- LeDoux, J. E., & Pine, D. S. (2016). Using neuroscience to help understand fear and anxiety: a two-system framework. American journal of psychiatry.
Is fear an emotion?
Yes, fear is a basic emotion that is triggered as a response to perceived threats. It is a survival mechanism that prompts action to protect oneself from danger. Fear can cause physiological changes like increased heart rate, and it can also influence thoughts and behaviors.
How do people perceive fear differently?
People perceive fear differently due to personal experiences, genetic predispositions, cultural norms, and mental health conditions. For some, a situation may trigger intense fear, while others may feel excitement or curiosity in the same situation. People’s coping strategies and resilience significantly influence their responses to fear-inducing situations.
What causes fear?
A perceived threat or danger causes fear. This can be a response to something immediate and obvious, such as coming face-to-face with a dangerous animal, or something more abstract, like a fear of losing one’s job. The brain’s amygdala plays a key role in processing fear by sending signals that trigger the fight-or-flight response. Fear can also be learned through personal experiences or by observing others.


