
Psychopathology Exam
Test your knowledge of AQA A-level Psychology Paper 1, Section D: Psychopathology. Covers definitions of abnormality, phobias, depression, OCD, and their explanations and treatments.
Question 1 of 1
1. Which definition of abnormality proposes that a behaviour is abnormal if it is rare or uncommon in the population? [1 mark]
Question 1 of 1
2. According to the deviation from ideal mental health definition, which of the following is a criterion for psychological normality proposed by Jahoda (1958)? [1 mark]
Question 1 of 1
3. Which of the following best describes a cognitive characteristic of depression? [1 mark]
Question 1 of 1
4. In the two-process model of phobias, what role does operant conditioning play? [1 mark]
Question 1 of 1
5. Which of the following is a behavioural characteristic of OCD? [1 mark]
Question 1 of 1
6. What does Beck's negative triad consist of? [1 mark]
Question 1 of 1
7. SSRIs are used to treat OCD. What is the primary mechanism by which SSRIs work? [1 mark]
Question 1 of 1
8. In Ellis's ABC model, what does the 'B' stand for? [1 mark]
Question 1 of 1
9. Which of the following is NOT a stage in systematic desensitisation? [1 mark]
Question 1 of 1
10. Which definition of abnormality could be criticised for potentially being used as a tool of social control? [1 mark]
Question 1 of 1
11. What does the term "aetiological heterogeneity" mean in relation to the genetic explanation of OCD? [1 mark]
Question 1 of 1
12. Which of the following best describes "flooding" as a treatment for phobias? [1 mark]
Question 1 of 1
13. Which two of the following are emotional characteristics of phobias? [2 marks]
(Select all that apply)
Question 1 of 1
14. Which two of the following are valid criticisms of the statistical infrequency definition of abnormality? [2 marks]
(Select all that apply)
Question 1 of 1
15. Which two of the following are criteria from Jahoda's (1958) concept of ideal mental health? [2 marks]
(Select all that apply)
Question 1 of 1
16. Which two of the following correctly describe features of the biological approach to treating OCD? [2 marks]
(Select all that apply)
Question 1 of 1
17. Outline and evaluate the cognitive approach to treating depression. [6 marks]
Model Answer
The cognitive approach to treating depression includes Cognitive Behavioural Therapy (CBT), based on Beck’s cognitive theory, and Rational Emotive Behaviour Therapy (REBT), based on Ellis’s ABC model.
Beck’s CBT aims to identify and challenge negative automatic thoughts that arise from faulty information processing and the negative triad (negative views about the self, the world, and the future). The therapist helps the patient to identify these thoughts, test them against reality, and replace them with more constructive ones. Patients are encouraged to become ‘scientists’ who gather evidence to test the validity of their negative beliefs. Homework tasks, such as keeping a thought diary, are used to reinforce new thinking patterns between sessions.
Ellis’s REBT uses the ABCDE model to treat depression. The therapist challenges (D = Dispute) the patient’s irrational beliefs identified at stage B, using logical argument and empirical evidence. The goal is to produce a new Effect (E), replacing irrational beliefs with rational ones. Techniques include vigorous debate and shame-attacking exercises designed to help the patient become more comfortable with potential failure.
One strength is research support. March et al. (2007) found that CBT was as effective as antidepressant medication for treating adolescent depression, and the combination of CBT and medication was more effective than either alone. This suggests CBT is a valid treatment for depression.
Another strength is that CBT empowers patients. Unlike drug therapy, which only treats symptoms, CBT equips patients with skills to identify and challenge their own negative thinking, potentially reducing the risk of relapse. This also gives patients a sense of control over their recovery.
However, CBT may not be suitable for all patients. Those with severe depression may lack the motivation and concentration needed to engage with the cognitive work required. In such cases, drug therapy may be needed first to lift mood before CBT can be effective.
Additionally, it is unclear whether negative thinking is the cause or a symptom of depression. The cognitive approach assumes irrational thoughts cause depression, but it may be that depression causes negative thinking. This raises questions about whether CBT addresses the root cause or merely a symptom.
Mark Scheme
AO1 (3 marks): Outline of CBT and/or REBT, including key features such as challenging negative thoughts, the ABCDE model, Beck’s negative triad, thought diaries, homework tasks, or the role of the therapist.
AO3 (3 marks): Evaluation points such as research support (e.g., March et al.), empowerment of patients, suitability issues for severe depression, or the causation debate (correlation vs cause).
Question 1 of 1
18. Outline and evaluate the two-process model as an explanation of phobias. [6 marks]
Model Answer
Mowrer (1947) proposed the two-process model, which explains phobias through a combination of classical and operant conditioning.
The first process is classical conditioning, which explains how phobias are acquired. A neutral stimulus (e.g., a dog) becomes associated with a traumatic experience (e.g., being bitten), which naturally produces a fear response. Through this pairing, the previously neutral stimulus becomes a conditioned stimulus that triggers a conditioned fear response. For example, Little Albert (Watson and Rayner, 1920) developed a phobia of white rats after a loud noise was repeatedly paired with the presence of a rat.
The second process is operant conditioning, which explains how phobias are maintained. When a person avoids the feared stimulus, their anxiety is reduced. This reduction in anxiety is negatively reinforcing (it removes something unpleasant), so the avoidance behaviour is likely to be repeated. The person never learns that the feared stimulus is not actually dangerous, so the phobia persists.
One strength is supporting evidence from Watson and Rayner’s (1920) Little Albert study, which demonstrated that a fear response could be acquired through classical conditioning in a human infant. This provides experimental support for the first process.
However, not everyone who has a traumatic experience goes on to develop a phobia. Di Nardo et al. (1988) found that not all people with dog phobias could recall a traumatic experience with dogs, and many people who had been bitten by dogs did not develop phobias. This suggests classical conditioning alone cannot fully explain how phobias develop.
Another weakness is that the two-process model cannot explain why humans are more likely to develop phobias of certain stimuli (e.g., snakes, heights) than others (e.g., cars, electrical sockets). Seligman’s (1971) concept of biological preparedness suggests we have an innate predisposition to fear stimuli that posed a threat to our ancestors, which the purely behavioural two-process model does not account for.
Additionally, the model is reductionist because it ignores the cognitive aspects of phobias, such as the irrational thinking patterns that accompany the fear response.
Mark Scheme
AO1 (3 marks): Description of the two-process model including classical conditioning (acquisition) and operant conditioning (maintenance through negative reinforcement/avoidance).
AO3 (3 marks): Evaluation may include supporting evidence (e.g., Little Albert), contradictory evidence (e.g., Di Nardo), biological preparedness, the cognitive dimension of phobias, or issues of reductionism.
Question 1 of 1
19. Explain the difference between the failure to function adequately and deviation from social norms definitions of abnormality. Give an example of each. [4 marks]
Model Answer
Failure to function adequately (FFA) defines abnormality as the inability to cope with the demands of everyday life. A person is considered abnormal when their behaviour causes them personal distress or prevents them from meeting the ordinary demands of living, such as maintaining personal hygiene, holding down a job, or sustaining relationships. For example, a person with severe depression who is unable to get out of bed, go to work, or care for themselves would be considered abnormal under this definition because their mental state is preventing them from functioning in daily life.
Deviation from social norms defines abnormality as behaviour that violates the unwritten rules and expectations of a society. When someone behaves in a way that the majority of people would consider unacceptable or incomprehensible, they may be judged as abnormal. For example, a person who talks loudly to themselves in a public place and behaves aggressively towards strangers would be considered abnormal because they are violating the social norms of acceptable public behaviour.
The key difference is that FFA focuses on the individual’s ability to cope and their personal distress, whereas deviation from social norms focuses on how the person’s behaviour compares to what society considers acceptable. A person could deviate from social norms without failing to function (e.g., eccentric behaviour), and someone could fail to function while appearing outwardly normal to others (e.g., concealed depression).
Mark Scheme
AO1 (2 marks): Clear description distinguishing failure to function adequately (inability to cope with everyday demands, personal distress) from deviation from social norms (behaviour violating society’s unwritten rules/expectations).
AO2 (2 marks): Appropriate examples that clearly illustrate the difference between the two definitions.
Question 1 of 1
20. Outline the role of neural mechanisms in OCD and give one limitation of this explanation. [4 marks]
Model Answer
The neural explanation of OCD proposes that the disorder is caused by abnormal levels of neurotransmitters and/or structural abnormalities in the brain.
At a neurochemical level, OCD is associated with low levels of serotonin. Serotonin plays a key role in transmitting mood-related information, and reduced serotonin activity may contribute to the obsessive thoughts and compulsive behaviours characteristic of OCD. There is also evidence that abnormal dopamine levels may be involved.
At a structural level, research has identified the “worry circuit” involving the orbitofrontal cortex and the caudate nucleus. Normally, the caudate nucleus acts as a filter, suppressing minor worrying thoughts before they reach conscious awareness. In people with OCD, the caudate nucleus is thought to malfunction, meaning trivial worries are not filtered out and instead loop repeatedly between the orbitofrontal cortex and the thalamus. Hyperactivity in the basal ganglia has also been linked to the repetitive motor actions seen in compulsions.
One limitation is the problem of causation. It is unclear whether the neurochemical imbalances and structural abnormalities identified in OCD patients are the cause of the disorder or a consequence of it. For example, low serotonin levels may be a symptom of having OCD rather than its underlying cause. The success of SSRIs in some patients suggests low serotonin plays some role, but the fact that not all patients respond to drug treatment casts doubt on whether neural mechanisms are the sole or primary cause.
Mark Scheme
AO1 (3 marks): Outline of neural mechanisms, which may include the role of serotonin, dopamine, the orbitofrontal cortex, caudate nucleus, thalamus (the worry circuit), or basal ganglia.
AO3 (1 mark): One developed limitation such as the causation issue, the fact that not all patients respond to drug treatment, or the failure to replicate some structural findings.
Scoring your answers…
Psychopathology refers to the study of mental disorders in terms of their causes, development, course, classification, and treatment.
Key Takeaways
- New Name: AQA renamed this topic “Clinical Psychology and Mental Health” in 2025 — same content, new name.
- Four Definitions: Abnormality is defined four ways: statistical infrequency, deviation from social norms, failure to function adequately, and deviation from ideal mental health.
- Three Disorders: The spec covers the behavioural, emotional and cognitive characteristics of phobias, depression and OCD.
- One Explanation Each: Phobias use the behavioural approach (two-process model), depression uses the cognitive approach (Beck and Ellis), and OCD uses the biological approach (genetics and neural circuits).
- Matched Treatments: Phobias are treated with systematic desensitisation or flooding, depression with CBT, and OCD with drug therapy (SSRIs).
- 24 Marks: This topic is Section D of Paper 1, assessed with a mix of AO1, AO2 and AO3 questions.
Definitions in the field of mental health
Definitions in the field of mental health: deviation from ideal mental health, deviation from social/cultural norms, failure to function adequately, and statistical infrequency. Failure to function adequately means being unable to cope with ordinary daily demands. Statistical infrequency means having a trait or behaviour that is rare, statistically speaking.
Deviation from Ideal Mental Health
This definition suggests that a person is considered abnormal if they lack certain characteristics associated with psychological well-being.
Instead of focusing on what makes someone abnormal, this approach defines what “ideal” psychological health looks like. Physical illness works the same way, defined by deviations from ideal physical health, such as correct temperature or blood pressure.
Jahoda suggested six criteria necessary for ideal mental health. An absence of any of these characteristics indicates individuals as being abnormal, in other words displaying deviation from ideal mental health.
Marie Jahoda (1958) proposed six criteria for ideal mental health:
- Accurate perception of reality: Having an objective and realistic view of the world. For example, a person with manic depression might believe they have superhuman powers in their manic phase.
- Self-actualisation: Fulfilling one’s potential and becoming everything one is capable of becoming.
- Positive attitudes towards the self: Having high self-esteem and a strong sense of identity.
- Environmental mastery: The ability to adapt and thrive in new situations, including being successful in love, work, and leisure.
- Autonomy: Being independent, self-reliant, and able to make personal decisions.
- Resistance to stress: Having effective coping strategies and being able to cope with everyday anxiety-provoking situations. Individuals experiencing anxiety, like Dave in one example, might not easily cope with stress, suggesting a deviation from this ideal.
When individuals fail to meet these criteria, they are seen as deviating from what is considered mentally healthy.
For instance, people with depression often struggle with low self-esteem, difficulty coping with stress, and a lack of motivation or inability to self-actualize.
Strengths:
- Comprehensive and positive focus: This definition outlines a wide range of criteria that help identify mental health issues, set treatment goals, and provide tailored support. It takes into account all facets and behaviours of a person, including their place in the world, lifestyle, and individuality, making it a holistic measure. It is a positive approach that suggests how problems can be overcome, not just what is wrong.
- Real-life application: It can be used as a basis for therapy and treatments, emphasizing positive mental health and well-being.
Limitations:
- Unrealistically high standard: Jahoda’s criteria are almost impossible for most people to meet all at once or maintain for long periods. For example, constantly self-actualizing could be exhausting, and being completely free of stress is not always desirable as stress can be a motivator. This means the majority of the population might be considered abnormal.
- Cultural relativism/Ethnocentrism: The criteria reflect Western individualistic values (like personal growth and autonomy). This makes it less applicable to collectivist cultures (e.g., China, India, Japan) that prioritize community and group well-being over individual achievement. Therefore, it is argued that this definition should only be used in the culture in which it was developed.
Deviation from Social/Cultural Norms
This definition states that a person’s thinking or behavior is classified as abnormal if it violates the unwritten rules, accepted standards, values, or expectations of a particular society or culture.
These social norms are passed on through socialization. Behaviour that breaks these rules is seen as improper or indecent.
It’s crucial to consider the degree and importance of the norm violation. What is considered socially acceptable is constantly changing and varies significantly across cultures and time periods.
For instance, homosexuality was considered abnormal and criminal in the UK until recently, and women having careers was once seen as abnormal.
Strengths:
- Flexibility: This definition is more flexible than statistical infrequency because it adapts to societal standards rather than rigid numerical cut-offs. It allows for desirable traits like high intelligence to be excluded from being classified as abnormal, unlike statistical infrequency.
- Social dimension: It provides a social dimension to the idea of abnormality, offering an alternative to the “sick in the head” individual. It can be a useful tool for assessing behaviour, like identifying antisocial behaviour that might be a symptom of schizophrenia, leading to appropriate treatment. It also helps protect members of society from distressing or harmful acts.
Limitations:
- Cultural relativism/Ethnocentrism: What is considered abnormal varies across cultures, leading to ethnocentrism, where one culture’s standards are used to judge another. For example, hearing voices is perceived as normal spiritual practice in some Afro-Caribbean cultures but misinterpreted as a hallucination (a sign of mental illness) in the West. Context shapes the diagnosis. Fernando (1998) describes this kind of mistake as a “category failure,” where a Western diagnostic framework misclassifies culturally normal behaviour as pathological. This can lead to misdiagnosis and inadequate treatment, especially for individuals from non-Western backgrounds living in Western societies.
- Subjectivity and lack of objectivity: Deciding exactly when behaviour deviates enough to be considered abnormal is subjective and open to opinion and interpretation. This contrasts with the objectivity of statistical infrequency.
- Ethical issues/Human Rights Abuse: This definition can be used as a mechanism for social control, persecuting groups that do not adhere to social norms. Historically, conditions like “nymphomania” were fabricated diagnoses to control women.
Failure to Function Adequately
Failure to function adequately (FFA) refers to an abnormality that prevents the person from carrying out the range of behaviours society would expect. Examples include getting out of bed each day, holding down a job, and conducting successful relationships.
Rosenhan and Seligman (1989) identified several characteristics of those failing to function adequately:
- Personal distress: The amount of distress a person experiences in response to their behaviour, thoughts, or situation (e.g., severe anxiety in OCD, or profound sadness in depression). Someone may want to interact with the world but struggles to even get out of bed.
- Irrationality: When a person’s behaviour becomes irrational, unpredictable, or dangerous to themselves or others.
- Observer discomfort: When an individual’s behaviour causes distress to those around them (e.g., poor personal hygiene or not respecting others’ personal space).
- Maladaptive behavior: Where an individual’s behaviour goes against their long-term best interests, such as neglecting personal appearance, losing appetite, or disturbed sleep patterns.
Examples include someone struggling to hold down a job due to severe anxiety, or being unable to maintain basic hygiene due to depression.
The more features of personal dysfunction a person has, the more they are considered abnormal.
To assess how well individuals cope with everyday life, clinicians use the Global Assessment of Functioning Scale (GAF), which rates their level of social, occupational, and psychological functioning.
Strengths:
- Considers subjective experience: This definition respects the individual and their own personal experience, emotions, and feelings about their behaviour. This is something that other definitions like statistical infrequency often fail to do.
- Practical checklist: It provides a practical checklist of criteria that individuals and clinicians can use to assess the level of abnormality, focusing on observable signs.
Limitations:
- Misses some abnormal behaviors: It fails to identify abnormal behaviours that do not cause personal distress or impairment, such as psychopathic criminal behaviour, where individuals may function normally despite engaging in acts that are clearly abnormal and have negative implications for others.
- Context dependency: What is considered “failing to function adequately” can depend on the context. For instance, not eating is generally failing to function, but prisoners on hunger strike are making a protest and would be seen differently.
- Subjectivity and reliability issues: The decision about whether someone is coping can be subjective and based on the opinion of observers. This means different observers might not agree, making it less reliable.
- Overlap with other definitions: Some behaviours, such as failing to follow interpersonal rules, might also be considered deviation from social norms, leading to overlap between definitions.
Statistical Infrequency
This definition classifies a person’s trait, thinking, or behavior as abnormal if it is rare, uncommon, or statistically unusual within a population.
It uses numerical data and statistics to determine abnormality.
For example, in a normal distribution (a bell-shaped curve), most scores fall around the middle, or mean. Extreme scores at the edges, typically two standard deviations from the mean, are considered statistically abnormal because they are rare.

Conditions like schizophrenia, affecting around 1% of the world population, are considered abnormal due to their rarity.
Strengths:
- Objectivity: This definition is praised for being objective because it relies on clear numerical cut-off points and statistics, not personal feelings or opinions. This means different mental health professionals can use the same standardized measurements, reducing subjectivity and increasing accuracy. It also provides clear points of comparison between people.
- Real-life application: It is almost always used in clinical diagnoses for mental health disorders as a comparison with a baseline or ‘normal’ value, helping to assess the severity of a disorder.
Limitations:
- Does not consider desirability: This definition fails to distinguish between desirable and undesirable behaviours. For example, having a very high IQ (like Albert Einstein) is statistically rare but highly desirable, and would not be considered a problem requiring treatment.
- Common disorders are missed: It implies that abnormal behaviour should be rare, but many serious mental health disorders are relatively common and would not be classified as statistically infrequent. For instance, depression affects about 10% of the UK population (rising to nearly 20% during the COVID-19 pandemic), and anxiety is also quite common.
- Arbitrary cut-off points: The psychological community subjectively decides where the cut-off point is between statistically normal and abnormal, which can have significant real-world implications, as someone just above the cut-off might be denied treatment.
AO2 Scenario Question
Diane is a 30-year-old businesswoman, and if she does not get her own way, she sometimes has a temper tantrum. Recently, she attended her grandmother’s funeral and laughed during the prayers. When she talks to people, she often stands very close to them, making them feel uncomfortable.
Identify one definition of abnormality that could describe Diane’s behaviour. Explain your choice.
(4 marks)
Answer
“Diana’s behaviour could be defined as deviating from social norms.
Although she is 30 she still has childish temper tantrums. She acted in a socially abnormal way at her grandmother’s funeral, and she disobeys social norms about how close it is appropriate to stand to people.
She is deviating from what is regarded as socially normal, thus according to this definition she would be defined as psychologically abnormal.”
AO2 Scenario Question
The following article appeared in a magazine: ‘Hoarding disorder – A ‘new’ mental illness.’
Most of us are able to throw away the things we don’t need on a daily basis. Approximately 1 in 1000 people, however, suffer from hoarding disorder.
It is defined as ‘a difficulty parting with items and possessions, which leads to severe anxiety and extreme clutter that affects living or work spaces.’
Apart from ‘deviation from ideal mental health,’ outline three definitions of abnormality. Refer to the article above in your answer. (6 marks)
OCD Characteristics
The behavioural, emotional and cognitive characteristics of obsessive-compulsive disorder (OCD).
Obsessive Compulsive Disorder (OCD) is an anxiety disorder characterised by intrusive and uncontrollable thoughts (i.e., obsessions) coupled with a need to perform specific acts repeatedly (i.e., compulsions).
Common clinical obsessions are fear of contamination (esp., being infected by germs), repetitive thoughts of violence (killing or harming someone), sexual obsessions, and obsessive doubt. Compulsions are the behavioural responses intended to neutralise these obsessions.
The most common compulsions are cleaning, washing, checking, counting, and touching. To the compulsive, these behaviours often seem to have magical qualities. If they are not performed exactly, “something bad” will happen.
Some O.C.D. sufferers will meticulously perform their rituals hundreds of times and experience extreme anxiety if prevented from carrying them out. Cleaning/washing rituals are more common in women; checking rituals are more common in men.
Behavioural Characteristics:
- Compulsions/Repetitive Behaviours: These are repetitive actions that an individual with OCD feels driven to perform to alleviate the anxiety caused by obsessions. These actions are often rigidly applied and may seem to have “magical qualities” to the sufferer. Common compulsions include checking (e.g., lights, locks), cleaning (e.g., excessive handwashing), counting, and touching. The anxiety reduction is typically only temporary.
- Avoidance: Individuals with OCD may avoid situations or places that trigger their obsessive thoughts or compulsive behaviours. This avoidance is negatively reinforced as it helps them avoid anxiety.
- Reduced Social Activity/Social Impairment: Due to the anxiety and the time-consuming nature of compulsions, individuals with OCD can struggle with normal relationships and social engagement, leading to social withdrawal.
Emotional Characteristics:
- Anxiety and Distress: Obsessive thoughts cause intense anxiety and distress. The individual may feel overwhelmed by the need to perform compulsions to reduce this anxiety. This is an uncomfortably high and persistent state of arousal, making relaxation difficult.
- Depression: The constant need to perform compulsive behaviours, which often interfere with daily functioning and relationships, can lead to a low mood and a loss of pleasure in everyday activities.
- Guilt and Disgust: These emotions can be associated with OCD.
- Shame/Embarrassment: Sufferers often experience a sense of shame or embarrassment about their compulsions or thoughts, especially because they recognise their behaviour is not rational or socially acceptable.
Cognitive Characteristics:
- Obsessive Thoughts: These are unwanted, intrusive, persistent, and recurrent thoughts, images, or urges that repeatedly enter the mind and cause anxiety. They can be irrational and embarrassing. Common themes include fear of contamination (germs), repetitive thoughts of violence, sexual obsessions, and obsessive doubt. These can also include catastrophic thoughts.
- Understanding Irrationality/Insight: A hallmark of OCD is the patient’s acknowledgement that their anxiety, obsessions, and compulsions are excessive and irrational, even though they are unable to control them.
- Cognitive Strategies: Patients may develop cognitive strategies to deal with their obsessions, such as always carrying multiple bottles of hand sanitiser.
- Hypervigilance/Selective Attention: This involves an increased awareness of the source of the obsession in new situations or a permanent state of alertness looking for the source of obsessive thoughts. There can also be an attentional bias.
A02 Exam Style Question
Steven describes how he feels when he is in a public place.
I always have to look out for people who might be ill. If I come into contact with people who look ill, I think I might catch it. I could die. If someone starts to cough or sneeze, then I have to get away and clean myself quickly.
Outline one cognitive characteristic of OCD and one behavioural characteristic of OCD that can be identified from the description provided by Steven. (2 marks)
Biological Approach to OCD
The biological approach to explaining and treating OCD: genetic and neural explanations; drug therapy.
The biological (medical) model of abnormality posits that psychological and behavioural abnormalities stem from biological causes, suggesting that issues with behaviour and experience arise from problems within the brain.
For Obsessive-Compulsive Disorder (OCD), the biological approach explains its origins through genetic and neural factors, and offers drug therapy as a primary treatment.
Genetic Explanations of OCD
The genetic explanation proposes that OCD is transmitted through genes, meaning individuals can inherit a vulnerability or predisposition to the disorder.
This implies that some people may possess specific genes making them more susceptible to developing OCD. No single gene causes it alone.
Evidence for a genetic basis comes from family and twin studies. For instance, Lewis (1936) found that 37% of patients with OCD had parents with the disorder, and 21% had siblings with it.
The pattern held up in later research.
More recent reviews, such as Nestadt et al. (2010), supported these findings. They reported the concordance rate (the percentage of twin pairs who both have the disorder) for OCD. The gap is not huge.
It was 68% in identical (monozygotic or MZ) twins, compared with 31% in non-identical (dizygotic or DZ) twins.
If OCD were purely genetic, identical twins, who share 100% of their DNA, would be expected to have a 100% concordance rate. The fact that it’s not 100% suggests that environmental factors also play a role. This is expected.
OCD is considered a polygenic condition, meaning that multiple genes are involved in its development. Some sources suggest perhaps as many as 230 different genes could be involved. The exact number is debated.
This also means OCD is aetiologically heterogeneous, implying that different combinations of genes can lead to different types of OCD in different individuals.
Two specific “candidate genes” have been identified that are thought to increase a person’s vulnerability to OCD.
- The COMT gene (catechol-O-methyltransferase) is believed to regulate the production of the neurotransmitter dopamine. A mutated variation of this gene, more common in OCD sufferers, leads to a decrease in COMT activity and, consequently, higher levels of dopamine.
- The SERT gene (serotonin transporter gene) affects the transport of serotonin, potentially lowering its levels. A mutation in this gene has been found in families where a majority of members had OCD.
The diathesis-stress model is often used to explain how these genetic vulnerabilities interact with environmental factors.
This model suggests that genetics may create a predisposition, or diathesis, for OCD. Stress alone is not enough. The disorder may only manifest if there is an environmental “stressor” or trigger, such as a traumatic life event.
For example, Cromer et al. (2007) found that over 50% of OCD patients had experienced a traumatic event in their past. Greater OCD severity was linked to a greater number of traumatic events.
Neural Explanations of OCD
Neural explanations focus on specific brain regions, structures (like neurons), and neurotransmitters involved in the nervous system.
They suggest that abnormalities in these neural mechanisms contribute to OCD symptoms.
Neurotransmitter Levels:
- Serotonin: Low levels of serotonin, a neurotransmitter involved in mood regulation, are strongly associated with OCD and obsessive thoughts. It’s thought that serotonin may be removed too quickly from the synapse before it can effectively transmit its signal.
- Dopamine: High levels of dopamine have also been implicated in OCD, particularly linked to compulsive behaviours. Animal studies where drugs enhancing dopamine levels induced stereotyped movements resembling compulsions support this.
Abnormal Brain Circuits/Structures:
Several areas in the frontal lobes of the brain are thought to function abnormally or be overactive in people with OCD.
This is sometimes referred to as the “worry circuit”.
- The Orbitofrontal Cortex (OFC): This area is crucial in OCD, as primitive urges related to sex, aggression, danger, and hygiene are thought to originate here. Overactivity in the OFC is linked to a higher frequency of obsessions.
- The Caudate Nucleus: Normally, the caudate nucleus suppresses signals from the OFC to the thalamus about worrying things. However, in OCD, it is believed to be faulty or damaged, failing to suppress these signals, leading to an overactive worry circuit.
- The Thalamus: When the caudate nucleus fails to suppress signals, the thalamus is alerted, which in turn sends signals back to the OFC, reinforcing the worry circuit.
- The Left Parahippocampal Gyrus: Abnormal functioning in this area, located on the underside of the brain near the hippocampus, is linked to increased processing of unpleasant emotions, a feature of OCD.
A limitation of neural explanations is that the relationship observed between neural mechanisms and OCD symptoms is often correlational, making it difficult to establish a clear cause-and-effect relationship.
It is unclear whether the brain changes or neurochemical imbalances cause OCD, are a result of the disorder, or are merely associated.
Drug Therapy for OCD
The biological approach to treating OCD primarily involves drug therapy. It aims to change neurotransmitter activity at synapses, the gaps between neurons.
The most commonly prescribed drugs for OCD are SSRIs (Selective Serotonin Reuptake Inhibitors). This is the default choice.
These drugs work by blocking the transporter mechanism that re-absorbs serotonin into the presynaptic neuron after it has fired.
More serotonin then remains in the synapse. This prolongs stimulation of the postsynaptic neuron, helping to regulate mood and anxiety and so reduce obsessive thoughts and compulsive behaviours.
Dosages vary, and it typically takes 3-4 months for the full benefits to show.
Other drugs may be prescribed if a patient does not respond well to SSRIs. These include:
- Tricyclics, such as Clomipramine, which work similarly to SSRIs but block the reuptake of both serotonin and noradrenaline. They tend to have more side effects.
- SNRIs (Serotonin-Noradrenaline Reuptake Inhibitors), which work on both noradrenaline and serotonin.
- Benzodiazepines (BZs), which are anti-anxiety drugs that enhance the activity of GABA (gamma-aminobutyric acid), slowing down the central nervous system and causing relaxation.
Evaluation of Drug Therapy:
- Effectiveness: Studies, such as a meta-analysis by Soomro et al. (2009), have shown that SSRIs are significantly more effective than placebos in reducing OCD symptoms, at least in the short term (within 6 to 13 weeks).
- Ease and Non-Disruptiveness: Compared to psychological treatments, drug therapy is often considered easier and less disruptive, as patients simply take a pill rather than attending lengthy therapy sessions. This can make treatment more accessible for people regardless of their lifestyle. They are also generally cost-effective compared to psychological treatments.
- Side Effects: A significant weakness is the potential for side effects, including indigestion, loss of sex drive, blurred vision, weight gain, aggression, nausea, headaches, and insomnia. These can make patients less willing to continue treatment, leading to symptom recurrence.
- Symptom vs. Cause: Drug therapies often treat the symptoms of OCD rather than addressing the underlying cause. This is known as the “treatment etiology fallacy” – just because a drug reduces symptoms doesn’t mean the lack of that chemical was the cause in the first place, similar to how aspirin treats a headache but a headache isn’t caused by a lack of aspirin. If the true cause is, for example, psychological trauma, drug therapy might only offer temporary relief.
- Partial Improvement: Some studies indicate that 40-60% of patients show no or only partial symptom improvement, suggesting that low serotonin is not the sole cause.
- Comparison with CBT: While drug therapy can be faster and requires less motivation than Cognitive Behavioural Therapy (CBT), CBT is often considered more empowering as it actively involves patients in challenging their thoughts, giving them a greater sense of control. However, drug therapy might be the only option for those with severe depression or low motivation.
Overall Evaluation: Issues and Debates
The biological approach to OCD, and psychology in general, frequently engages with several key debates:
- Nature vs. Nurture: The biological approach strongly supports the “nature” side, emphasizing the role of genes, biological structures, and neurochemistry. However, the concept of genotype and phenotype acknowledges the interaction between an individual’s genetic code and environmental influences on observable characteristics. Furthermore, the diathesis-stress model explicitly highlights that both inherited vulnerability (nature) and environmental stressors (nurture) are necessary for the disorder to develop.
- Determinism: The biological approach is largely biologically deterministic, proposing that human behaviour is governed by internal biological causes over which individuals have no control, such as genes and brain chemistry. This can have implications for moral responsibility and may be perceived as pessimistic for sufferers.
- Reductionism: The biological approach is considered reductionist because it explains complex human behaviour by breaking it down into simpler, more fundamental biological components, such as genes, neurons, and neurotransmitters. While this allows for scientific study and the development of drug treatments, critics argue it may oversimplify and overlook the complex interaction of many factors or the holistic experience of an individual.
- Nomothetic Approach: The biological approach generally adopts a nomothetic approach, aiming to establish general laws about behaviour from the study of large groups of people using quantitative and scientific methods, such as scanning techniques, twin studies, and drug trials. This approach is seen as highly scientific due to its objectivity, control, and reliability.
Depression Characteristics
The behavioural, emotional and cognitive characteristics of depression.
Depression is classified as a mood or affective disorder, characterised by a continuous state of sadness and low mood.
It involves a collection of physical, emotional, mental, and behavioural experiences that are severe, prolonged, and damaging to everyday functioning.
A diagnosis often requires at least five or more symptoms, with low mood or loss of pleasure being essential for diagnosis in some systems.
Behavioural Characteristics:
- Changed Activity Levels: Depression can lead to increased lethargy and a lack of energy, causing withdrawal from previously enjoyable activities (anhedonia). It may also result in psychomotor agitation or, conversely, an inability to get out of bed. Poor hygiene can also be notable.
- Changes in Sleep Patterns: Sufferers may experience insomnia (reduced sleep) or hypersomnia (increased sleep).
- Changes in Eating Patterns: Appetite can be disrupted, leading to significant weight gain or loss.
- Aggression: This can be directed towards others or manifest as self-harm.
Emotional Characteristics:
- Depressed Lowered Mood: A continuous state of sadness that differs from temporary low moods.
- Lowered Self-Esteem/Self-Worth: Individuals often express feelings of having a low view of themselves, sometimes to the point of self-hatred. They may experience guilt linked to helplessness and feelings of worthlessness.
- Loss of Pleasure (Anhedonia): A significant reduction or complete loss of interest and enjoyment in activities that were once pleasurable.
- Anger: High levels of anger can be present, directed both towards oneself and others.
Cognitive Characteristics:
- Difficulty Concentrating: Poor concentration levels are common, affecting decision-making and the ability to focus on tasks, even simple ones.
- Negative Thinking: Sufferers tend to dwell on negativity, overlooking positive aspects of situations. This includes irrational thoughts.
- Beck’s Cognitive Triad: This theory explains depression through three key elements: negative self-schemas (negative views of themselves), cognitive distortions (distorted negative interpretations of life events like overgeneralization or catastrophizing), and the negative triad (a pessimistic view of themselves, the world, and the future).
- Absolutist Thinking: Jumping to irrational conclusions, such as believing they are a “failure of a son” for missing an event.
- Selective Attention to Negative Events: Patients often recall only negative events, ignoring positive ones.
- Recurrent Thoughts of Death: This is another cognitive symptom.
- Low Confidence: A common cognitive characteristic.
AO2 Scenario Question
Ben recently moved away from home to go to university. He loved his new life of going out, meeting new friends, and his new university course.
Life felt good at first. However, after a while, he struggled to get out of bed and started to become very tired.
His eating patterns changed, and he lost a lot of weight. He grew irritable too, snapping at friends over little things.
When he sat in lectures, he found it hard to concentrate for long periods of time.
Identify the behavioural, emotional, and cognitive aspects of Ben’s state. (3 marks)
Cognitive Approach to Depression
The cognitive approach to understanding and treating depression focuses on one idea: dysfunctional or irrational thinking is the primary cause of emotional and behavioural problems like depression.
This approach contrasts with others by making inferences about mental processes that cannot be directly observed.
Here’s how the cognitive approach explains and treats depression:
Beck’s Negative Triad
According to Beck, depressed individuals have distorted and unrealistically negative ways of thinking about themselves, their experiences, and their future.
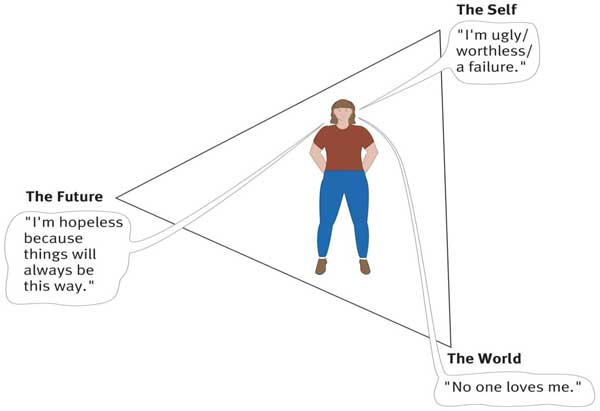
- Self: For example, depressed individuals tend to view themselves as helpless, worthless, and inadequate.
- World Experiences: They interpret events in the world in an unrealistically negative and defeatist way, and they see the world as posing obstacles that can’t be handled.
- Future: Finally, they see the future as totally hopeless because their worthlessness will prevent their situation from improving.
These negative thinking patterns are influenced by:
- Negative self-schemas: These are deeply held, negative, and pessimistic beliefs and expectations about oneself, often developing in childhood due to criticism or rejection from significant others. These schemas bias how a person interprets events in their life.
- Cognitive biases: These are exaggerated or irrational thought patterns that arise from negative self-schemas, causing distorted interpretations of life events. Examples include:
- Overgeneralising: Making sweeping conclusions based on a single incident.
- Catastrophising: Exaggerating a minor incident and believing it to be a major disaster.
- Selective abstraction: Focusing only on negative details while ignoring positive ones.
- Absolutist thinking: Thinking in ‘black and white’ terms, such as “I am a failure if I can’t do X”.
These factors collectively reinforce the negative triad. The result is a pessimistic view of the self, the world (seen as hostile and full of insurmountable obstacles), and the future (assumed to always turn out badly).
This theory suggests that secondary symptoms of depression, such as a lack of motivation, can be understood as a result of this core of negative beliefs.
Ellis’ ABC Model
Albert Ellis’s ABC model explains depression by focusing on how irrational thoughts influence emotions and behaviour.
According to Ellis, depression arises not directly from an activating event, but from a person’s irrational beliefs about that event.
The model consists of three components:
- A – Activating Event: This is a situation or event that occurs in someone’s life, which can be minor or major.
- B – Beliefs: This refers to the thoughts a person has about the activating event. These beliefs can be either rational or irrational. Irrational beliefs, such as “musturbatory thinking” (the idea that certain things must be true for happiness, like “I must be valued by others”), lead to unhealthy emotional responses.
- C – Consequences: These are the negative feelings and behaviours that result from the irrational beliefs. If beliefs are rational, the consequences are healthy emotions and better mental well-being.
According to Ellis, depression does not occur as a direct result of a negative event but rather is produced by irrational thoughts (i.e., beliefs) triggered by negative events.
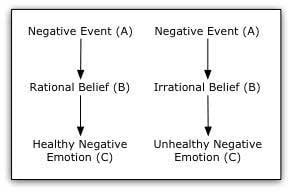
Ellis believes it is not the activating event (A) that causes depression. Instead, a person interprets events unrealistically. This creates an irrational belief system (B), which produces the unhelpful consequences (C) that follow.
Consider an example. Some people irrationally assume they are failures if they are not loved by everyone they know. This belief (B) leads them to constantly seek approval, and the consequence (C) is that they repeatedly feel rejected.
All their social interactions (A) are affected by this assumption, so a great party can leave them dissatisfied because they do not get enough compliments.
Cognitive Behaviour Therapy (CBT)
Cognitive Behaviour Therapy (CBT) is the main cognitive treatment for depression.
It is a structured talking therapy that aims to help individuals manage their problems by changing their thought patterns and resulting behaviours.
CBT operates on the assumption that irrational or faulty thinking patterns lead to emotional and behavioural problems.
CBT builds on both Beck’s and Ellis’s models:
Based on Beck’s Model: Beck’s cognitive therapy involves techniques to identify and challenge the patient’s negative triad and cognitive biases.
- Thought Catching/Diary Records: Patients identify and record their irrational thoughts and negative views of themselves, the world, and the future. This is often done by keeping a thought diary.
- Patient as Scientist / Reality Testing: The therapist encourages the patient to generate and test hypotheses about the validity of their irrational thoughts. They collect evidence for and against their thoughts in real-life situations to see if their beliefs match reality.
- Behavioural Activation: Patients are encouraged to engage in enjoyable activities that they used to participate in, to help improve their mood and provide counter-evidence to negative beliefs.
Based on Ellis’s REBT (Rational Emotive Behaviour Therapy):
Ellis’s version of CBT extends his ABC model to include D for Disputing and E for Effects.
The therapist actively challenges the client’s irrational beliefs through “vigorous argument”. Types of disputing include:
- Logical Disputing: Questioning whether the irrational thoughts make sense or logically follow from the facts.
- Empirical Disputing: Challenging the client to provide evidence for their irrational beliefs, showing they are not consistent with reality.
- Pragmatic Disputing: Asking how practical and helpful believing those thoughts actually are.
The effect (E) of disputing these irrational thoughts is to help the person think more rationally. This changes how they feel about the situation, improving their emotional well-being and behaviour.
CBT sessions typically involve regular meetings (e.g., 5-20 sessions) and often include “homework” assignments for the patient to practice identifying and challenging irrational thoughts in everyday life.
AO2 Scenario Question
Jack suffers from depression. His symptoms include loss of concentration, lack of sleep, and struggles to sleep at night. He finds himself having absolutist thoughts that everything is negative and bad all the time.
How might a cognitive behaviour therapist tackle Jack’s depression? (4 marks)
Evaluation of CBT for Depression:
- Effectiveness: CBT has shown to be very effective in treating depression. A study by March et al. (2007) found that CBT, drug treatment, and a combination of both all improved depression symptoms in adolescents. The combined treatment was found to be the most effective after 36 weeks (86% improvement), with CBT alone showing 81% effectiveness, similar to drug therapy (81%).
- Comparison with Drug Therapy:
- CBT avoids the negative side effects and withdrawal symptoms associated with biological treatments like antidepressant drugs.
- Drug treatments can work faster and require less motivation and commitment compared to the demanding nature of CBT.
- CBT is often seen as more empowering because it actively involves the patient in challenging and changing their thoughts, giving them a greater sense of control over their condition, unlike the passive role with medication.
- Commitment and Motivation: CBT requires real commitment and motivation from the patient. Motivation often dips. Patients with severe depression may struggle to engage consistently due to low energy, poor concentration, or feelings of hopelessness.
- Focus on Present vs. Past: CBT primarily focuses on present problems and current circumstances, often not exploring past traumatic events that might contribute to depression. Some do, though. This can frustrate patients who believe their past is relevant to their condition.
- Blaming the Patient: A criticism is that the cognitive approach may “blame the patient” by focusing solely on thoughts as the cause of depression. That misses the bigger picture. External factors, like domestic abuse or financial hardship, often need practical solutions too.
- Correlational Nature: It is not always clear whether faulty cognitions are a cause or a consequence of depression, as the relationship can be correlational. Both readings are plausible.
- Scope of Explanation: Cognitive explanations may not fully account for all aspects of depression, such as physical symptoms, extreme anger, or manic phases seen in bipolar disorder.
CBT is also adapted and used to treat other conditions, such as schizophrenia (CBTp). There, it helps patients identify and correct distorted beliefs, such as delusions and hallucinations, through reality testing.
Phobia Characteristics
The behavioural, emotional and cognitive characteristics of phobias.
Phobias are a type of anxiety disorder characterised by an extreme and irrational fear of a specific object or situation.
This fear is excessive or unreasonable, and it significantly interferes with an individual’s daily life, distinguishing it from normal fears.
The symptoms of phobias can be placed into one of three categories:
Behavioural Characteristics:
- Panic: Individuals with phobias often experience panic when encountering their feared object or situation. This can manifest as crying, screaming, freezing, sweating, running away, fainting, or even vomiting. This panic is a result of heightened physiological arousal, triggered by the hypothalamus activating the sympathetic nervous system.
- Avoidance: A defining characteristic is the strong urge to avoid the phobic stimulus. People will go to great lengths to steer clear of anything that triggers their anxiety. This avoidance behaviour is negatively reinforced because it reduces the unpleasant feeling of anxiety, thereby maintaining the phobia. This often leads to significant disruptions in their normal daily routine and ability to function.
- Endurance: In some cases, a person might remain exposed to the phobic stimulus for an extended period, but they will still experience heightened levels of anxiety throughout this time. This could involve remaining frozen still, such as not leaving a meeting.
Emotional Characteristics:
- Anxiety: This is the primary emotion associated with phobias. It presents as an intense, persistent dread and worry about the feared object or situation. This leads to an uncomfortably high and persistent state of arousal, making it difficult for the person to relax or experience positive emotions.
- Fear: Coupled with anxiety, there is an intense experience of fear, which is linked to the body’s fight-or-flight response, leading to an increased heart rate and breathing rate. This intense emotional sensation of extreme and unpleasant alertness only subsides once the phobic object is removed.
- Irrationality of Fear/Anxiety: Individuals are often aware that their fear is excessive or unreasonable, and that the level of anxiety caused is disproportionate to the actual threat posed by the stimulus.
Cognitive Characteristics:
- Irrational Beliefs: People with phobias frequently hold irrational beliefs, thinking the feared object or situation is far more dangerous than it actually is. These beliefs contribute to unreasonable anxiety responses and are not easily reduced by reasoning.
- Selective Attention: Sufferers tend to focus disproportionately on the feared object or situation, even when it causes severe anxiety, ignoring other less threatening stimuli. This can impair their ability to concentrate on other tasks.
- Cognitive Distortions: The patient’s perception of the phobic stimulus may be inaccurate, appearing grossly distorted or irrational.
Behavioural Approach to Phobias
The behavioural approach in psychology focuses on observable and measurable behaviour, arguing that all behaviour is learned from our environment.
Behaviourists believe that humans and animals learn in similar ways, meaning that findings from animal studies can often be extrapolated to human behaviour.
This approach emphasizes scientific methodology, using laboratory experiments to ensure objectivity, control over variables, and precise measurement, which contributes to psychology’s scientific credibility.
The Two-Process Model
The behavioural approach explains the development and maintenance of phobia, mainly using the theories of classical conditioning and operant conditioning.
These were first combined as a single explanation for phobia by Mowrer in the two-process model of phobia. This idea was influential.
According to behaviourists, phobias are the result of a classically conditioned association between an anxiety-provoking unconditioned stimulus (UCS) and a previously neutral stimulus.
For example, a child with no previous fear of dogs gets bitten by a dog and, from this moment onwards, associates the dog with fear and pain.
Due to the process of generalization, the child is not just afraid of the dog who bit them but shows a fear of all dogs. Fear generalises fast.
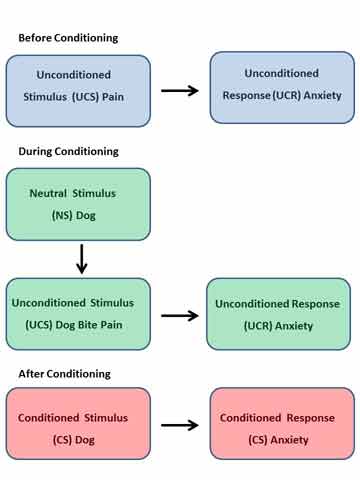
Operant conditioning can help to explain how the phobia is maintained. This is the second stage.
When an individual avoids the feared object or situation (phobic stimulus), they experience a reduction in anxiety and distress.
This relief acts as a negative reinforcement, strengthening the avoidance behaviour. It makes the person more likely to keep avoiding the phobic object or situation, which maintains the phobia.
Not all phobias fit this trauma-based story, though. DiNardo et al. (1988) found a frightening dog encounter was almost as common among people with no dog phobia (66%) as among those who had one (56%). This challenges the assumption that trauma alone reliably produces a phobia.
A02 Questions
Kirsty is in her twenties and has had a phobia of balloons since one burst near her face when she was a little girl. Loud noises such as ‘banging’ and ‘popping’ cause Kirsty extreme anxiety, and she avoids situations such as birthday parties and weddings, where there might be balloons.
Suggest how the behavioural approach might be used to explain Kirsty’s phobia of balloons. (4 marks)
There is empirical support to show how classical conditioning leads to the development of phobias.
Aim: Watson and Rayner (1920) aimed to show that a fear response could be learned through classical conditioning.
Method: A young infant, Little Albert, was shown a white rat, which caused him no fear. Fear was absent at first. The researchers then repeatedly paired the rat with a loud, frightening noise.
Results: Albert developed a fear response to the rat alone, and this fear generalised to similar white, furry objects.
Conclusion: A phobia can be acquired through classical conditioning, supporting the acquisition stage of the two-process model. This matters for exam answers.
The behaviourist approach takes a limited view of a phobia’s origins, since it overlooks cognition. This matters, because irrational thinking is a key feature of phobias. This gap matters.
Tomarken et al. (1989) presented a series of slides of snake and neutral images (e.g., trees) to phobic and non-phobic participants. The phobics tended to overestimate the number of snake images presented. Bias was clear.
In theory, anyone could develop a phobia of a potentially harmful object, although this does not always happen. Cars are one example. Most adults have experienced, witnessed, or heard about car accidents, yet a phobia of cars is almost unheard of.
Seligman (1970) suggests that humans have a biological preparedness to develop certain phobias rather than others because they were adaptive (i.e., helpful) in our evolutionary past.
For example, individuals that avoided snakes and high places would be more likely to survive long enough and pass on their genes than those who did not.
Ost and Hugdahl (1981) support this idea of biological preparedness. They found that nearly half of people with phobias have never had a frightening experience with the feared object, and some have had none at all.
Some snake phobics have never even seen one.
The cognitive approach criticises the behavioural model as it does not take mental processes into account.
They argue that the thinking processes that occur between a stimulus and a response are responsible for the feeling component of the response.
16-Mark Exam Question: The Two-Process Model
Max has a phobia of the sea. On a family holiday as a child, he was carried away by the tide and had to be rescued by a lifeguard. Now he has a family of his own, Max refuses to go on beach holidays.
Discuss the two-process model of phobias, referring to Max’s phobia of the sea. This question is worth 16 marks.
It is a real past AQA question, marked on a 4-band scale, with 6 marks for AO1, 4 for AO2, and 6 for AO3.
AO1: Describe how classical conditioning develops a phobia, and operant conditioning maintains it. A neutral stimulus becomes linked with a frightening event, producing a conditioned fear response that can generalise to similar objects.
AO2: Apply this to Max. The sea, a previously neutral stimulus, became associated with being carried away by the tide, a frightening event. The story fits Max well.
His fear has generalised from that one beach to all beach holidays. It persists because avoiding the sea removes his anxiety, reinforcing the avoidance. This is the maintenance stage.
AO3: Support the model with Watson and Rayner’s Little Albert study, but also challenge it. DiNardo et al. (1988) found a traumatic conditioning event was not always present in phobia sufferers. Not every case fits.
AO3 (continued): Seligman’s biological preparedness explains why some phobias, like a fear of the sea, are commoner than others. A further criticism is that the model largely ignores cognitive factors.
Behavioural Treatments for Phobias
Behavioural therapies for phobias aim to replace the learned fear association with a new, more positive association, typically relaxation.
This process is known as counter-conditioning. It relies on the principle of reciprocal inhibition, which states that two opposite emotional states, such as fear and relaxation, cannot coexist simultaneously.
Systematic Desensitisation (SD)
Systematic desensitisation is a gradual behavioural therapy designed to reduce phobic anxiety through step-by-step exposure to the phobic stimulus. The process typically involves three key components:
- Relaxation: The patient is first taught deep muscle relaxation techniques, such as breathing exercises or progressive muscle relaxation. The goal is to reduce the activity of the sympathetic nervous system (fight-or-flight response) and activate the parasympathetic nervous system.
- Anxiety Hierarchy: The patient and therapist collaboratively create a step-by-step list of situations involving the phobic stimulus, ordered from the least anxiety-provoking to the most terrifying.
- Gradual Exposure: The patient then gradually works their way up the anxiety hierarchy over several sessions, applying the learned relaxation techniques at each stage. They only progress to the next level when they can remain completely calm and relaxed at the current one. Exposure can be “in vitro” (imagining the phobic stimulus) or “in vivo” (actual exposure), and virtual reality exposure therapy (VRET) can also be used as an “in vitro” form of SD. The phobia is considered cured when the patient can remain calm at the highest level of the hierarchy.
Strengths and Evidence for SD:
- Effectiveness: Research by Gilroy et al. (2003) showed that 42 patients treated for spider phobia in three SD sessions reported reduced fear at 3 and 33 months compared to a control group, supporting its long-term effectiveness. Rothbaum et al. (2000) also found significant improvement in individuals with a fear of flying using VRET, comparable to traditional exposure therapy.
- Suitability for Diverse Patients: SD is suitable for a wide range of patients, including those with learning difficulties, as it does not require complex cognitive engagement or evaluation of thoughts, making it a viable alternative to cognitive behavioural therapy (CBT).
- Acceptability: Patients tend to find SD more acceptable due to its gradual nature and sense of control, leading to lower refusal and attrition (dropout) rates compared to more intense therapies like flooding. It is generally less traumatic than flooding.
Limitations of SD:
- Time-Consuming: SD can be a slow process, often requiring multiple sessions (e.g., 6-8 sessions on average).
- Limited Generalisability: The effectiveness of SD may sometimes be limited to the controlled environment of the therapist’s office and may not fully translate to real-world experiences, where phobias might resurface.
- Effectiveness for Complex Phobias: SD may be less effective for more complex phobias, such as social phobias, which involve significant cognitive aspects like irrational thoughts, where cognitive therapy might be more appropriate.
Flooding
Flooding is a behavioural therapy that contrasts sharply with systematic desensitisation.
It involves exposing the patient to their most feared phobic stimulus immediately and intensely, without any gradual build-up or avoidance options.
The exposure occurs in a safe and controlled environment from which the patient cannot escape.
The underlying principle of flooding is that fear is a time-limited response.
Initially, the patient experiences extreme anxiety and panic.
However, since the phobic object or situation is not actually harmful, and escape or avoidance is prevented, the patient’s anxiety cannot be maintained indefinitely. It will eventually subside due to exhaustion.
This prolonged, intense exposure creates a new, positive association (e.g., a sense of calm) with the feared object, leading to the extinction of the fear response.
Strengths of Flooding:
- Cost-Effective and Quicker: Flooding is generally considered more cost-effective and quicker than systematic desensitisation or cognitive therapies because phobias can often be cured in a single, immersive session lasting 2-3 hours.
- Effectiveness: For those who can complete the session, flooding can be a highly effective form of treatment, sometimes more effective than SD. Its success supports the hypothesis that phobias persist due to avoidance, which prevents extinction.
Limitations of Flooding:
- Highly Traumatic and Distressful: Flooding is a highly traumatic experience that can cause significant emotional distress and even emotional harm to the patient.
- Risk of Reinforcing Phobia: If flooding is not conducted properly, or if the patient exits the therapy session before their anxiety subsides, it can actually reinforce the phobia, making it worse. Wolpe (1969) reported a case where flooding led to a client’s hospitalisation.
- Not Suitable for All: Flooding is not appropriate for all patients, especially those with underlying medical conditions (e.g., heart conditions) or young children, due to the extreme anxiety it induces. It is also less effective for complex phobias like social phobias that have a strong cognitive component.

