Grandiosity is a psychological term that refers to an exaggerated sense of one’s importance, abilities, or status. While anyone might occasionally feel unusually confident, grandiosity is more intense and persistent. It often appears disconnected from external reality.
In mental health contexts, grandiosity is most commonly recognized as a symptom of manic or hypomanic episodes in bipolar disorder. It can shape thoughts, mood, and behavior in significant ways.

This article is for informational and educational purposes only and is not intended to be a substitute for professional medical advice, diagnosis, or treatment.
Always seek the advice of your physician, therapist, or other qualified health provider with any questions you may have regarding a medical or mental health condition. Never disregard professional advice or delay in seeking it because of something you have read on this site.
Signs of grandiosity in bipolar disorder
The symptoms of grandiosity can vary widely from person to person and often depend on the intensity of the manic or hypomanic episode. Some individuals may show several signs, while others display only one or two.
⚠️ Important: Experiencing one or two of these behaviors does not mean someone has bipolar disorder. A proper diagnosis must be made by a qualified mental health professional following a full clinical assessment.
Common Signs of Grandiosity
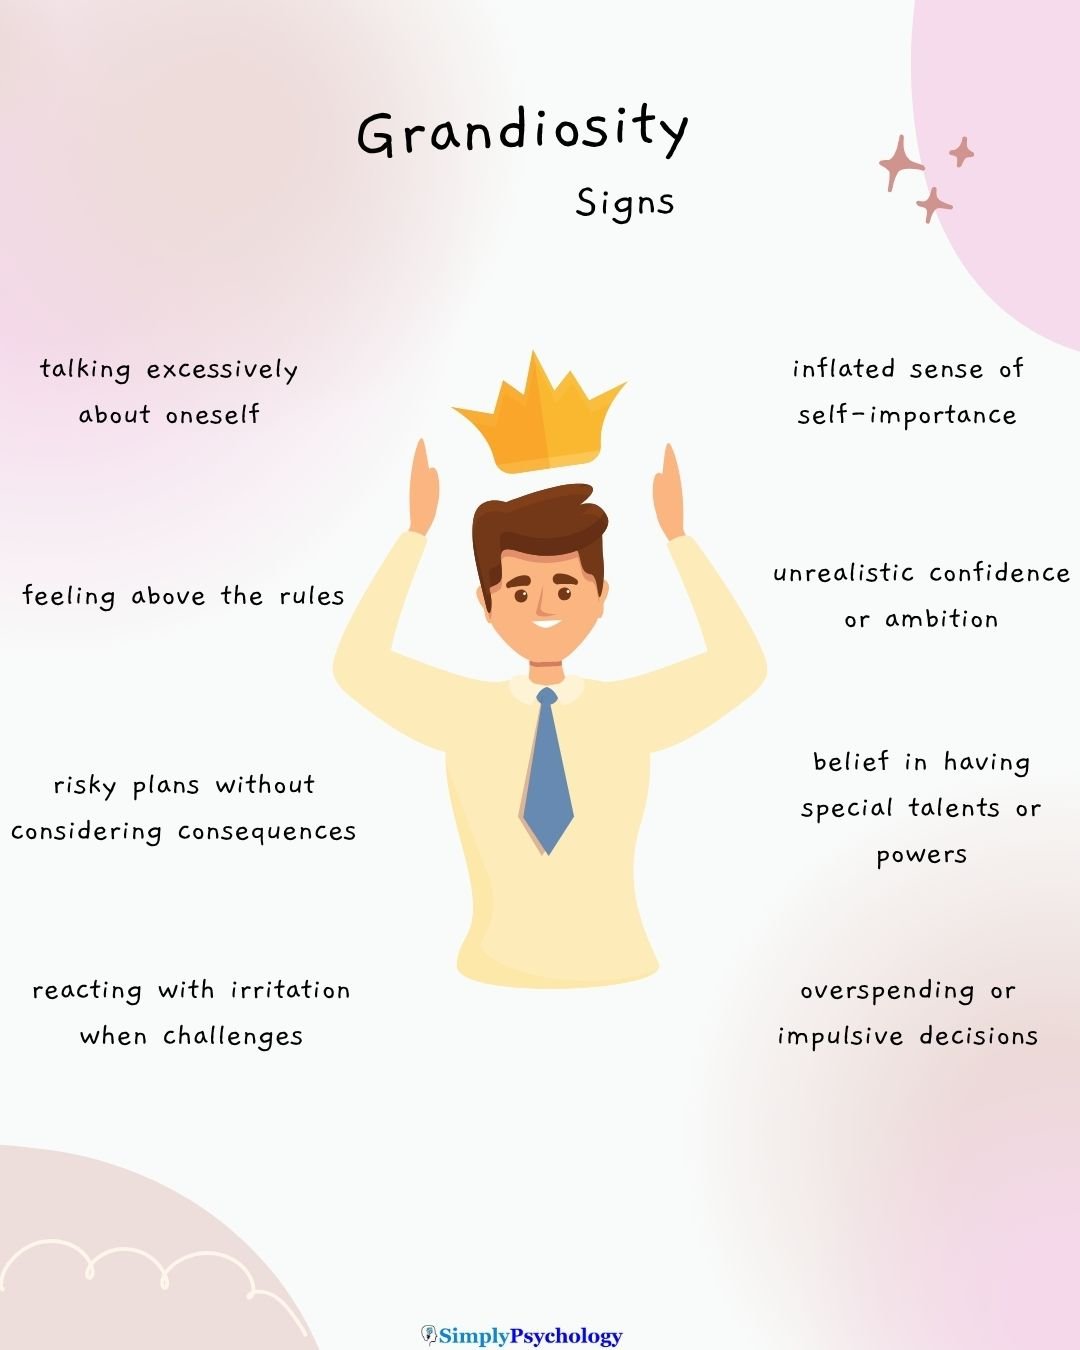
- Inflated self-importance or superiority
- Belief in special powers, talents, or a unique destiny
- Unrealistic confidence in one’s potential or goals
- Acting above rules, norms, or advice
- Risky behaviors, such as overspending or impulsive decisions
- Excessive self-focus in conversation
- Irritability when challenged or contradicted
Grandiosity is often more visible during manic episodes, periods of abnormally high mood and energy. These last at least a week, or any length if hospital care is needed.
It can also occur subtly during hypomania. This milder form of mania lasts at least four days, without severe impairment or hospitalization. In some cases, it becomes extreme enough to develop into delusions of grandeur. Once the episode ends, grandiose thoughts typically fade.
Example:

You’re scrolling through job listings when you see a senior leadership role that requires 10+ years of experience and an advanced degree.

You’ve just started your first job, but you’re certain you’d be perfect for it. After all, you’ve always known you were meant for big things.

You skim the qualifications—none of them worry you. In your mind, this is your next step. Why wouldn’t they hire you?
How Clinicians Identify Grandiosity
The DSM-5-TR, the US diagnostic manual, lists “inflated self-esteem or grandiosity” first among seven symptoms of a manic episode (American Psychiatric Association, 2022). Three are needed, or four if mood is only irritable.
They must appear during a distinct period of elevated, expansive or irritable mood with increased energy. The manual treats grandiosity as a spectrum. It runs from uncritical self-confidence, through marked grandiosity, to fixed delusional belief.
Four points help separate grandiosity from ordinary confidence:
- One belief is not enough: Diagnosis rests on a cluster of symptoms lasting days, not a single boastful idea.
- Change from baseline: Each symptom must be a noticeable shift from the person’s usual behavior.
- Ambitious plans: A typical sign is starting several projects at once with little knowledge or talent to match.
- Reduced need for sleep: This is one of the most common features and often signals that an episode is starting.
- Age matters: Children often overestimate their abilities normally, so the criterion applies only if beliefs persist despite clear contrary evidence.
Noticing Grandiosity in Others
People experiencing grandiosity may not recognize changes in their thinking or behavior. Signs may become apparent to those close to them, especially if they:
- Seem unusually self-focused or dismissive of others
- Pursue unrealistic plans with intense energy
- React strongly when their ideas are questioned
- Show sudden changes in confidence or risk-taking
Noticing a shift from someone’s typical behavior, rather than judging based on a single trait, can help determine whether grandiosity might be a symptom of a larger mood episode.
Why Does Grandiosity Happen in Bipolar Disorder?
Grandiosity typically arises during manic or hypomanic episodes. They are driven by complex changes in brain chemistry, sleep, and stress.
During these periods, raised levels of monoamines, brain chemical messengers including dopamine and noradrenaline, are thought to fuel intense energy, impulsivity, and inflated self-esteem (Price & Drevets, 2010). This monoamine hypothesis rests largely on indirect evidence.
Drugs that raise monoamine levels can trigger manic symptoms in vulnerable people. From the inside, the resulting thoughts can feel completely logical and true.
Factors like genetics, trauma, and disrupted sleep can increase a person’s vulnerability to these mood shifts. Genetics matter. Bipolar disorder is among the most heritable psychiatric conditions (McGuffin et al., 2003).
Disrupted sleep and routine can tip someone into an episode (Ehlers et al., 1988). So can goal-related successes, like a promotion (Johnson, 2005).
While not everyone with bipolar disorder experiences grandiosity, it’s a common feature when manic thinking escalates beyond confidence into distortion.
Why Grandiose Thoughts Persist
Brain chemistry does not explain why the content of manic thinking turns self-inflating. Researchers have proposed several complementary routes:
- Positive mood: In the emotion-consistent view, elated mood itself drives grandiose content (Knowles et al., 2011).
- Reward sensitivity: An overreactive reward system may drive excess goal-directed behavior, reduced sleep need, elevated confidence and euphoria (Johnson, 2005).
- Dwelling on good moments: Repeatedly thinking about times of feeling special may keep grandiose ideas going (Bortolon et al., 2023).
The rumination idea has been tested directly. In one online experiment, 219 adults without marked depressive symptoms recalled a time they felt special. They were then randomly assigned to ruminate on the memory or to think about unrelated scenes.
After seven minutes, the distraction group had returned to baseline. The rumination group stayed about 14 points higher on a 0 to 100 grandiose-ideas scale (Bortolon et al., 2023).
This was a laboratory study of non-clinical adults, using four ad hoc questions. It shows that rumination prolongs a temporary self-enhancing state. It does not show how grandiosity is maintained during mania, and the authors caution that the causes may differ in bipolar disorder.
An earlier laboratory study compared 27 people with bipolar disorder with 27 healthy controls. Ruminating on a happy memory boosted positive mood more than reflecting on it (Gruber et al., 2009). That study measured mood, not grandiosity.
Grandiosity Examples: What It Feels Like
Below are some individual accounts of grandiosity during mania, a period of abnormally high mood and energy. They show how varied it can feel from the inside:
“My grandiose thoughts were really focused on making things perfect. Like Stepford wife level, cooking, cleaning and errand runner. I could also go to school, teach my kid and earn money, while being a ‘good’ wife. I often got really aggressive when things didn’t come out. Followed by tears and exhaustion.”
‘Mina’
“I think often it’s just that you see things from an altered perspective. Often, that perspective will be hard to understand if you haven’t thought of it that way before and because the way your mind might try to interpret it, it might either sound/be grand. On the other hand, however, because of the new perspective sometimes you might just be able to understand something which is already there in an extremely insightful way if your mind thinks about in the right way.”
‘David’
“I would also have quite grandiose career ideas. I almost applied to be a nanny during one mania despite having almost zero childcare experience.”
‘Elle’
“I feel godlike almost. Incapable of being harmed. I often go to bars and pick fights… I deeply struggle with this sense of being untouchable when manic, not only in being a bully but also in terms of doing extremely dangerous things.”
‘Sam’
Many people describe the high as appealing as well as risky. Kay Redfield Jamison is a Johns Hopkins psychiatrist who has lived with bipolar disorder herself. As Jamison explains in her memoir An Unquiet Mind, the manic pole can feel seductive as well as destructive.
Research points the same way. A 2026 systematic review of mostly qualitative studies asked what people with bipolar disorder see as positive about mania and hypomania. It found five themes, including advanced ability and achievement, and an enhanced relationship with self and others (Luksaite et al., 2026).
For some people, an inflated self-view is part of what the state offers. That may help explain why some feel ambivalent about treatment.
Grandiosity in Bipolar Disorder vs. Narcissistic Personality Disorder
Grandiosity can appear in both bipolar disorder and narcissistic personality disorder (NPD), but the underlying causes, timing, and patterns are quite different.
In bipolar disorder, grandiosity typically shows up during manic or hypomanic episodes and fades when mood stabilizes.
It’s often driven by elevated energy, impulsivity, and distorted thinking. Outside of these episodes, the person may feel regret or confusion about their behavior.
In contrast, NPD grandiosity is chronic and ingrained, not tied to mood swings. It reflects a stable pattern of viewing oneself as superior, needing admiration, and often lacking empathy. It doesn’t come and go with emotional states.
The diagnostic criteria set the two apart in four ways (American Psychiatric Association, 2022):
| Feature | Grandiosity in mania or hypomania | Narcissistic personality disorder |
|---|---|---|
| Course | A distinct period that ends: mania lasts at least a week, hypomania at least four days | A pervasive pattern that begins by early adulthood and appears across settings |
| Mood and energy | Comes with abnormally elevated, expansive or irritable mood and increased energy, often with little sleep | No change in mood or energy is required |
| Other features | Three of seven symptoms (four if mood is only irritable); grandiosity is one option | Five of nine criteria, including need for admiration, entitlement, exploitativeness and lack of empathy |
| Between episodes | Self-view returns to the person’s usual baseline | The pattern persists |
The two diagnoses can still co-occur. In a US survey of 34,653 adults, lifetime narcissistic personality disorder was significantly linked to bipolar I disorder (Stinson et al., 2008).
The link held after controlling for other conditions, though it weakened. Association is not causation.
If grandiosity persists once mood has settled, it is worth assessing for personality difficulties. It is not proof of them. Kernberg and Yeomans (2013), writing as clinicians, advise judging symptoms against a patient’s sense of self, relationships and functioning over time.
Example:

During a manic episode, someone with bipolar disorder might suddenly believe they’re destined to become a famous tech founder. They may spend thousands launching a startup overnight, despite no prior interest in business. Weeks later, they may feel embarrassed or question their actions.


Someone with narcissistic personality disorder might consistently promote themselves as a visionary entrepreneur. They exaggerate achievements and dismiss criticism. None of this is due to a mood shift; it fits their ongoing self-image.
Grandiosity vs. Delusions of Grandeur in Bipolar Disorder
Grandiosity is not the same as grandiose delusions, also known as delusions of grandeur.
A delusion is a false belief held by a person, contradicting what is considered true. Grandiose delusions are one of the most common types of delusions people with bipolar disorder experience.
Delusions often have the following characteristics:
- The belief that the delusion is true, even when others know it to be untrue.
- The person will not listen to other viewpoints about the belief, despite contradictory evidence that challenges the delusion.
- The content of the delusion is impossible or implausible.
- The delusion impacts the person’s daily life.
People who experience delusions of grandeur may have beliefs such as the following:
- They have a unique talent, object, or ability unknown to others
- They are a famous person, and the real one is an impostor
- They have secret connections or work as a spy
- They’ve been chosen by a religious entity or that they are a spiritual leader
Where Grandiosity Becomes Delusion
The difference is one of degree and of responsiveness to evidence (American Psychiatric Association, 2022).
Take two illustrative examples. One person is certain they would run a company better than its chief executive and wants to be considered for the job.
That is an inflated appraisal, and feedback can in principle shift it.
Another person is convinced they have already been appointed chief executive and treats the lack of any record as part of a plot. That is a delusion.
Grandiose delusions are common in mania, though estimates vary with how they are rated. A review reported them in around two-thirds of people with bipolar disorder (Knowles et al., 2011).
In 830 adults with psychotic disorders, they were rated in 20% of people with bipolar mania and 7% of those with schizophrenia (Picardi et al., 2018).
The figures differ widely, but both show the same ordering.
Of 1,136 acutely hospitalized patients, 328 were rated definitely or possibly delusional. Grandiose and religious delusions were held with the greatest conviction (Appelbaum et al., 1999). Grandiose delusions are also considered relatively resistant to standard cognitive-behavioral techniques (Knowles et al., 2011).
Impact of Grandiosity in Bipolar Disorder
Grandiosity in bipolar disorder can become problematic in many different ways. It can affect a person’s ability to think rationally, preventing someone from considering more realistic perspectives.
Relationships with others
To those who do not fully understand the symptoms, grandiosity can make someone seem conceited and rude.
People may not want to spend time with someone showing grandiose patterns. This can break down relationships, especially those the person relies on for social support.
Grandiosity could result in people becoming or feeling isolated once their manic or hypomanic episode has ended.
Employment
Grandiosity could also affect the individual’s relationships with those at work. If the individual reacts with anger when criticized, dismisses others’ accomplishments, and believes they are above the rules, this can create a negative work environment.
Grandiosity could also make the individual want to impulsively quit their job or make elaborate switches in career plans, which can impact employment if carried out.
Interviews show how heavy these costs can be. Siegel-Ramsay et al. (2023) spoke with 24 adults with bipolar disorder and six family caregivers. Participants described unstable employment, relationship breakdown and a disrupted sense of identity.
As one participant put it, “I’ve literally been fired from every job that was fire-able.” These accounts cover the disorder as a whole. They do not show that grandiosity alone caused the losses.
Putting themselves at risk
Grandiosity could also create the potential for physical harm, such as getting into fights if they react angrily and then are confronted or criticized.
The person may believe they are above the rules and have impaired judgment about their vulnerability.
They could abuse substances if they believe that these substances cannot cause them harm or that they are protected by an outside force. They might also be more financially reckless.
How is grandiosity managed?
Grandiosity in bipolar disorder is typically addressed as part of managing manic or hypomanic episodes. While treatment needs vary from person to person, a combination of medication, therapy, and lifestyle support is often used to help regulate mood and reduce symptoms.
⚠️ This section is for informational purposes only and is not a substitute for professional medical advice. Always consult a qualified healthcare provider before making treatment decisions.
Medications
Certain medications are commonly used to help stabilize mood and manage symptoms like grandiosity:
- Mood stabilizers (such as lithium) are often used long-term to reduce the frequency and intensity of manic episodes.
- Antipsychotics may help manage elevated mood and distorted thinking by affecting dopamine pathways in the brain.
- Antidepressants might be prescribed to address depressive symptoms, but are usually combined with a mood stabilizer to reduce the risk of triggering mania.
Each medication comes with its own potential side effects, and treatment plans should be tailored by a healthcare professional.
Trial evidence supports these choices for mania as a whole. A meta-analysis of 68 randomized trials covered 16,073 participants. Ten drugs, including lithium, olanzapine and haloperidol, all beat placebo for acute mania (Cipriani et al., 2011).
Antipsychotics were overall more effective than mood stabilizers. The outcome was change on mania rating scales, so it does not show an effect on grandiosity alone. Long-term lithium remains a first-line choice for preventing relapse (Geddes et al., 2004).
Psychotherapy
Therapy can complement medication by helping individuals better understand and manage their symptoms. Common approaches include:
- Cognitive Behavioral Therapy (CBT): Helps individuals recognize unhelpful thoughts (cognitive distortions) and behaviors, identify triggers, and develop coping strategies for managing stress and mood shifts.
- Interpersonal and Social Rhythm Therapy (IPSRT): Focuses on stabilizing daily routines, like sleep, meals, and activity levels, to support mood regulation. It builds on social zeitgeber theory, which links disrupted routines to mood episodes (Ehlers et al., 1988).
- Family-Focused Therapy: Involves loved ones in treatment to improve communication, recognize early warning signs, and strengthen support systems.
Therapy may also help address any distress or confusion a person feels after experiencing grandiose episodes.
Lifestyle
Healthier lifestyle habits may also help manage the symptoms of bipolar disorder, alongside medication and therapy. They can include:
- Avoiding alcohol and recreational drugs: Quitting completely can limit the temptation to use substances during an episode, when risk-taking is a major concern.
- Building supportive relationships: Friends and family can spot warning signs.
- Creating a healthy routine: Regular sleep, meals, and exercise help balance moods.
- Keeping a mood chart: Recording daily moods, sleep, activities, and feelings helps identify triggers for an episode. Charts also show if treatment needs adjusting.
How To Support Someone With Bipolar Grandiosity
There are many ways in which you can support someone who is experiencing a manic episode:
- Build trust: Talk openly and listen to how mania affects them.
- Ask how you can help: They often know what helps and what does not.
- Offer help with self-management: Help complete a plan that names triggers and warning signs.
- Avoid assumptions: Good moods are not always mania, so look for consistent patterns.
- Be gentle: Voice concern calmly, without criticism or accusation.
- Discuss challenging behavior: Set calm, non-confrontational boundaries.
- Offer reassurance: Remind them you still care once the episode ends.
- Help them find support: Research options and attend appointments together.
- Plan for a crisis: Agree in advance who to contact and when hospital care is needed.
Build trust
Having an open and honest conversation with the person experiencing mania or hypomania and discussing how it affects them.
You can ask them questions about what they have experienced and engage well in what they are saying to feel heard. This can also help to improve their understanding of what things are like for them.
Ask how you can help
The person who experiences manic or hypomanic episodes often already knows what helps them and what does not.
If they are unsure of how to help themselves, then you can offer to help by exploring their options.
Offer to help with self-management
People who experience manic or hypomanic episodes may find it useful to develop a self-management plan to help them manage their symptoms better.
You can help them complete the plan by naming triggers or warning signs they may not have noticed. Make suggestions, but the final decision is theirs.
The self-management plan can also be useful to review together when the individual experiences another episode.
Don’t make assumptions
It is normal for people with bipolar disorder to have good and bad moods without it necessarily being a manic episode. The person may find it frustrating if they are questioned, or you start worrying about them whenever they are having a good day.
Instead, it may help to look for consistent signs and patterns that they are approaching an episode, and discuss what this episode presents.
Be gentle in your approach
If the person’s behavior is becoming worrying, it is important to gently let them know you are worried about them without criticizing or accusing them.
Staying calm and non-confrontational may make them more likely to discuss what they are experiencing.
You can gently explain that you have noticed changes in their behavior and why it concerns you. Often, people do not notice an episode is under way. Someone who knows their usual behavior may spot the change first.
Discuss challenging behavior
Being around someone in a manic or hypomanic episode can be a challenge, especially when grandiose signs appear. Selfishness or quick anger can make it harder.
The individual may not realize that their behavior is causing tension, so it is ok to set boundaries in a non-confrontational, calm manner.
For instance, you could say that you will end the conversation if they are rude. You could also say that you will not join their grand ideas if you feel these will have negative consequences.
Offer reassurance
When the manic or hypomanic episode is over, the person may feel ashamed or embarrassed about their behavior. They may feel like they want to isolate themselves from their loved ones if they do not like how they act in front of them.
They may really benefit from you reassuring them that you still care and understand that their behavior is a part of their condition.
Help them find the support they need
People may find it difficult to find the right care and support for themselves. If they agree, you can help in three ways.
- Research treatment options together.
- Attend appointments with them.
- Help them find suitable coping strategies.
Diagnosis can take time. People usually seek help while depressed, so bipolar disorder is often mistaken for unipolar depression or an anxiety disorder (American Psychiatric Association, 2022).
On average, it can take up to 10 years from first seeking help to a correct diagnosis (Gergel et al., 2024). Psychotic features can also be mistaken for schizophrenia. Delays can worsen outcomes (McIntyre et al., 2020).
A review found that people of African descent are disproportionately misdiagnosed with schizophrenia instead of bipolar disorder (Akinhanmi et al., 2018).
Plan for a crisis
In extreme cases, manic or hypomanic episodes can become so intense that the individual may need to be hospitalized. To account for this, it can be useful to devise a crisis plan with the individual.
A crisis plan can cover three things.
- Who to contact.
- What to do.
- When to consider hospital treatment.
Some people go further. They write a self-binding directive while well, which records in advance which treatments they consent to during a future severe episode.
Tania Gergel is Director of Research at Bipolar UK and has lived experience of the illness. As she explains, people who are severely unwell but calm and articulate are often judged lower-risk than they are (Gergel et al., 2024). A plan written in advance guards against that gap.
Key Takeaways
- Definition: Grandiosity is an exaggerated, persistent sense of one’s importance, abilities or status that often seems disconnected from reality.
- Mood Link: In bipolar disorder it typically appears during manic or hypomanic episodes and fades when mood stabilizes.
- Diagnosis: One boastful belief is not enough. Clinicians look for a cluster of manic symptoms that mark a clear change from the person’s usual self.
- Versus NPD: Grandiosity in narcissistic personality disorder is a lifelong pattern, with no change in mood or energy required.
- Versus Delusions: Delusions of grandeur are fixed beliefs held despite evidence. An inflated self-view can, in principle, shift with feedback.
- Treatment: Medication and therapy treat the manic episode as a whole. Trials have not tested grandiosity on its own.
- Support: Stay calm and non-confrontational, set boundaries, and agree a crisis plan in advance.
Do you need mental health help?
USA
Call or text 988 to reach the 988 Suicide & Crisis Lifeline, which offers free, confidential support from trained counselors 24 hours a day. In immediate danger, call 911. More information: https://988lifeline.org/
988
UK
Contact the Samaritans for support and assistance from a trained counselor: https://www.samaritans.org/; email jo@samaritans.org .
Available 24 hours a day, 365 days a year (this number is FREE to call):
116-123
Rethink Mental Illness: rethink.org
0300 5000 927
Further Information
Self Help Resources for Bipolar Disorder or Manic Depression
References
Akinhanmi, M. O., Biernacka, J. M., Strakowski, S. M., McElroy, S. L., Balls Berry, J. E., Merikangas, K. R., Assari, S., McInnis, M. G., Schulze, T. G., LeBoyer, M., Tamminga, C., Patten, C., & Frye, M. A. (2018). Racial disparities in bipolar disorder treatment and research: A call to action. Bipolar Disorders, 20(6), 506–514. https://doi.org/10.1111/bdi.12638
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). https://doi.org/10.1176/appi.books.9780890425787
Appelbaum, P. S., Robbins, P. C., & Roth, L. H. (1999). Dimensional approach to delusions: Comparison across types and diagnoses. American Journal of Psychiatry, 156(12), 1938–1943. https://doi.org/10.1176/ajp.156.12.1938
Bortolon, C., Baeyens, C., & Raffard, S. (2023). Hooked on a memory: How rumination about past positive events might contribute to grandiose ideas? British Journal of Clinical Psychology, 62(3), 556–572. https://doi.org/10.1111/bjc.12425
Cipriani, A., Barbui, C., Salanti, G., Rendell, J., Brown, R., Stockton, S., Purgato, M., Spineli, L. M., Goodwin, G. M., & Geddes, J. R. (2011). Comparative efficacy and acceptability of antimanic drugs in acute mania: A multiple-treatments meta-analysis. The Lancet, 378(9799), 1306–1315. https://doi.org/10.1016/S0140-6736(11)60873-8
Depression and Bipolar Support Alliance. (n.d.). Bipolar Disorder Statistics. https://www.dbsalliance.org/education/bipolar-disorder/bipolar-disorder-statistics/
Ehlers, C. L., Frank, E., & Kupfer, D. J. (1988). Social zeitgebers and biological rhythms: A unified approach to understanding the etiology of depression. Archives of General Psychiatry, 45(10), 948–952. https://doi.org/10.1001/archpsyc.1988.01800340076012
Geddes, J. R., Burgess, S., Hawton, K., Jamison, K., & Goodwin, G. M. (2004). Long-term lithium therapy for bipolar disorder: Systematic review and meta-analysis of randomized controlled trials. American Journal of Psychiatry, 161(2), 217–222. https://doi.org/10.1176/appi.ajp.161.2.217
Gergel, T., Adiukwu, F., & McInnis, M. (2024). Suicide and bipolar disorder: Opportunities to change the agenda. The Lancet Psychiatry, 11(10), 781–784. https://doi.org/10.1016/S2215-0366(24)00172-X
Gruber, J., Harvey, A. G., & Johnson, S. L. (2009). Reflective and ruminative processing of positive emotional memories in bipolar disorder and healthy controls. Behaviour Research and Therapy, 47(8), 697–704. https://doi.org/10.1016/j.brat.2009.05.005
Johnson, S. L. (2005). Mania and dysregulation in goal pursuit: A review. Clinical Psychology Review, 25(2), 241–262. https://doi.org/10.1016/j.cpr.2004.11.002
Kernberg, O. F., & Yeomans, F. E. (2013). Borderline personality disorder, bipolar disorder, depression, attention deficit/hyperactivity disorder, and narcissistic personality disorder: Practical differential diagnosis. Bulletin of the Menninger Clinic, 77(1), 1–22. https://doi.org/10.1521/bumc.2013.77.1.1
Knowles, R., McCarthy-Jones, S., & Rowse, G. (2011). Grandiose delusions: A review and theoretical integration of cognitive and affective perspectives. Clinical Psychology Review, 31(4), 684–696. https://doi.org/10.1016/j.cpr.2011.02.009
Luksaite, M., Maguire, T., Tarabay, J., & Richardson, T. (2026). Positive beliefs about mania held by individuals with bipolar disorder: A systematic review. Psychology and Psychotherapy: Theory, Research and Practice. Advance online publication. https://doi.org/10.1111/papt.70087
McGuffin, P., Rijsdijk, F., Andrew, M., Sham, P., Katz, R., & Cardno, A. (2003). The heritability of bipolar affective disorder and the genetic relationship to unipolar depression. Archives of General Psychiatry, 60(5), 497–502. https://doi.org/10.1001/archpsyc.60.5.497
McIntyre, R. S., Berk, M., Brietzke, E., Goldstein, B. I., López-Jaramillo, C., Kessing, L. V., Malhi, G. S., Nierenberg, A. A., Rosenblat, J. D., Majeed, A., Vieta, E., Vinberg, M., Young, A. H., & Mansur, R. B. (2020). Bipolar disorders. The Lancet, 396(10265), 1841–1856. https://doi.org/10.1016/S0140-6736(20)31544-0
Mind. (2020). Hypomania and mania. https://www.mind.org.uk/media-a/4123/hypomania-mania-2020-pdf-version.pdf
National Health Service. (2019). Causes – Bipolar disorder. https://www.nhs.uk/mental-health/conditions/bipolar-disorder/causes/
Parial, S. (2015). Bipolar disorder in women. Indian Journal of Psychiatry, 57(Suppl 2), S252.
Picardi, A., Fonzi, L., Pallagrosi, M., Gigantesco, A., & Biondi, M. (2018). Delusional themes across affective and non-affective psychoses. Frontiers in Psychiatry, 9, Article 132. https://doi.org/10.3389/fpsyt.2018.00132
Price, J. L., & Drevets, W. C. (2010). Neurocircuitry of mood disorders. Neuropsychopharmacology, 35(1), 192–216. https://doi.org/10.1038/npp.2009.104
Siegel-Ramsay, J. E., Sharp, S. J., Ulack, C. J., Chiang, K. S., Lanza di Scalea, T., O’Hara, S., Carberry, K., Strakowski, S. M., Suarez, J., Teisberg, E., Wallace, S., & Almeida, J. R. C. (2023). Experiences that matter in bipolar disorder: A qualitative study using the capability, comfort and calm framework. International Journal of Bipolar Disorders, 11, Article 13. https://doi.org/10.1186/s40345-023-00293-9
Stinson, F. S., Dawson, D. A., Goldstein, R. B., Chou, S. P., Huang, B., Smith, S. M., Ruan, W. J., Pulay, A. J., Saha, T. D., Pickering, R. P., & Grant, B. F. (2008). Prevalence, correlates, disability, and comorbidity of DSM-IV narcissistic personality disorder: Results from the Wave 2 National Epidemiologic Survey on Alcohol and Related Conditions. The Journal of Clinical Psychiatry, 69(7), 1033–1045. https://doi.org/10.4088/jcp.v69n0701


